- A prolonged QT is a measurement on an ECG, not a diagnosis on its own. What matters most is the reason behind it.
- Most cases are acquired rather than inherited. Common medicines and low levels of potassium or magnesium are the usual causes, and both can often be corrected.
- A smaller group of people have long QT syndrome, an inherited condition present from birth. It affects roughly 1 in 2,000 people and runs in families.
- In both forms, the concern is the same: a slower electrical reset gives a particular unstable heart rhythm a chance to start.
- Many people have no symptoms. When symptoms occur, fainting is the most common, often during exercise, a sudden fright, or strong emotion.
- Knowing which medicines can lengthen the QT is the most practical part of living with it, whatever the cause.
Seeing “prolonged QT” on an ECG report raises an immediate question, and it is a fair one: does this mean there is something wrong with my heart?
Often the answer is reassuring. A prolonged QT is a measurement, and the reason behind it varies a great deal. Many times it is linked to a recently started medicine, or a potassium level that has drifted low.
Less often, it reflects an inherited condition that runs in families. Both are worth understanding, and they lead to quite different conversations.
What the QT Interval Measures
Every heartbeat is driven by an electrical signal. The heart muscle switches on, squeezes, and then has to reset before it can beat again.
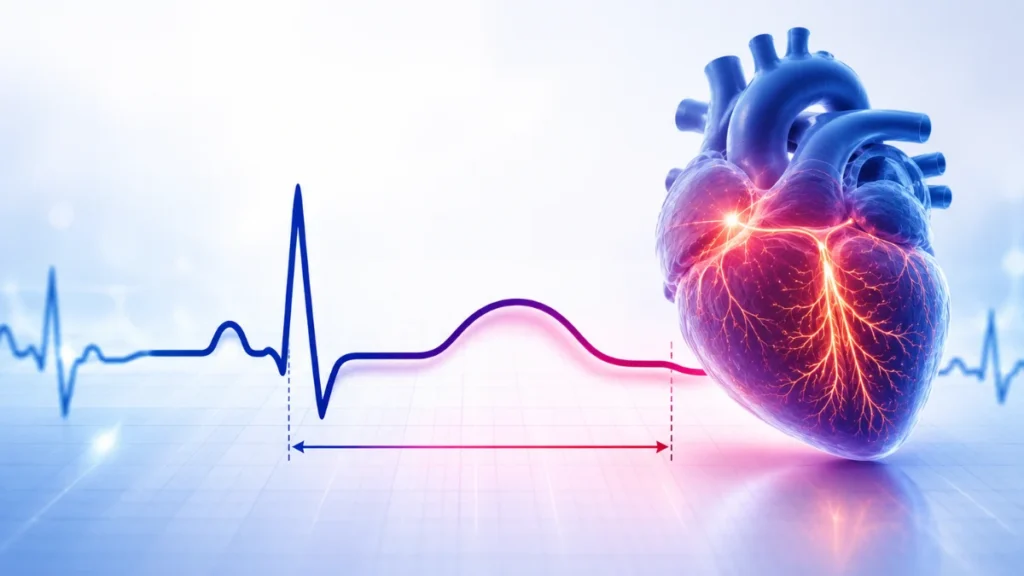
On an ECG, the QT interval covers that whole cycle in the lower pumping chambers, from the start of the squeeze to the end of the reset. It is, in effect, the heart’s reset time.
The reset naturally gets shorter when the heart beats faster, so the measurement is adjusted for heart rate. This adjusted figure is shown on the report as the QTc.
As a rough guide, a QTc below about 450 milliseconds in men and 460 in women is considered normal. Above 500 is the level that draws close attention. Values in between need interpreting in context rather than reading off a single cut-off.
Why a Longer Reset Matters
While the heart is resetting, it is briefly vulnerable. If the reset takes longer than it should, that vulnerable window stays open for longer.
An extra electrical impulse arriving during that window can set off a fast, unstable rhythm called torsades de pointes. The name is French for “twisting of the points” and describes how the rhythm looks on the tracing.
Torsades usually stops on its own, causing dizziness or a faint. Occasionally it does not, and it can turn into a life-threatening rhythm. That uncommon possibility is the reason a prolonged QT is taken seriously.
It helps to keep this in proportion. Many people live with a prolonged QT for years without ever having a rhythm problem. The measurement describes a risk, not an event.
Acquired or Inherited: Two Different Pictures
The single most important question about a prolonged QT is whether something has caused it, or whether the person was born with the tendency.
More common
Acquired long QT
Caused by something outside the heart’s wiring, most often a medicine or low potassium or magnesium. It often returns to normal once the cause is removed or corrected.
About 1 in 2,000 people
Inherited long QT syndrome
Present from birth and passed down in families. It is lifelong, but well managed with treatment, awareness of triggers, and screening of close relatives.
The Common Causes of Acquired Long QT
Medicines are the leading cause, and the list is longer than most people expect. It includes some antibiotics, antifungals, antidepressants, antipsychotics, and anti-nausea medicines, as well as some medicines used for other heart rhythm problems.
Many people take these without any difficulty. The risk rises when two are combined, or when one is taken alongside the other factors below.
Low potassium or magnesium reliably lengthens the QT. These blood salts can drop with fluid tablets (diuretics), with vomiting or diarrhoea, or with kidney problems. Bringing them back to normal often brings the QT back too.
A slow heart rate lengthens the QT naturally, which is why it sometimes appears alongside bradycardia or heart block.
Other contributors include an underactive thyroid, significant weight loss or eating disorders, and the period after a heart attack.
The encouraging part is that acquired long QT is frequently reversible. That is why finding the cause comes first.
The Inherited Form: Long QT Syndrome
Long QT syndrome affects the tiny channels in heart cells that let salts such as potassium and sodium move in and out. These channels control how quickly the heart resets after each beat.
It is usually found in one of two ways. Sometimes it shows up on an ECG done for another reason. Other times it is picked up through family screening after a relative has been diagnosed.
Finding it before any symptoms have occurred is the best outcome, because the whole approach to the inherited form is about prevention.
There are several types. The three most common behave differently enough that knowing which one is present shapes the advice given.
| Type | Typical trigger | Treatment notes |
|---|---|---|
| Type 1 | Exercise, especially swimming | Responds very well to beta-blockers |
| Type 2 | Sudden noise, startle, strong emotion | Beta-blockers work well |
| Type 3 | Rest or sleep | Approach may differ from types 1 and 2 |
A parent with the inherited form has a one in two chance of passing it to each child. Brothers, sisters, and parents of an affected person also have a one in two chance of carrying it.
This is why family screening is central to managing the condition. A diagnosis in one person often leads to a conversation involving several.
What It Might Feel Like
Many people feel nothing at all, whatever the cause, and only learn about it after a routine ECG.
When symptoms do occur, fainting is the most common. The circumstances are telling. Fainting during exercise, straight after a sudden fright, or during intense emotion is the pattern that most often leads to further tests.
In a young person, collapsing during sport is always a reason for an ECG.
Some people notice palpitations or a sudden lurch beforehand. Occasionally, a heart rhythm problem like this is mistaken for epilepsy, because the faint can look like a seizure.
How It Is Assessed
The ECG is the starting point, but a single tracing rarely settles the question. The QT changes through the day and with heart rate, so a borderline result on one ECG may look different on another.
A review of current medicines comes early. So do blood tests for potassium, magnesium, and thyroid function, because these are the causes that can be corrected.
An exercise test can help, because the QT responds to exertion differently depending on the cause. Longer heart monitoring over 24 hours or more gives a fuller picture than a 10-second ECG in the clinic.
Where the inherited form is suspected, a genetic test can identify the specific change in most confirmed cases. Relatives can then be tested for that exact change.
A normal ECG alone does not completely rule out the inherited form. That is why genetic testing carries so much weight within families.
Medicines That Can Lengthen the QT
This is the most practical piece of knowledge for anyone with a prolonged QT, whatever the cause.
Medication awareness
Examples include some antibiotics (azithromycin, clarithromycin, moxifloxacin), antifungals (fluconazole), antidepressants (citalopram, escitalopram), antipsychotics, and anti-nausea medicines (ondansetron, domperidone). Some medicines used for other heart rhythm problems also lengthen the QT.
This list is far from complete. CredibleMeds keeps a regularly updated international database that grades medicines by their effect on the QT, and it is widely used by doctors and pharmacists.
Many of these medicines are still prescribed to people with a prolonged QT, with monitoring, because the alternative may carry greater risk. They are not forbidden. The aim is that the choice is made knowingly.
Doctors, dentists, and pharmacists can only take a prolonged QT into account if they know about it. Letting each of them know whenever a new medicine is being considered is widely regarded as the most useful habit.
How It Is Treated
When the cause is acquired, treatment usually means removing it. The responsible medicine is stopped or swapped, the potassium or magnesium is corrected, and the ECG is repeated. Often that is the end of the matter.
For the inherited form, beta-blockers are the mainstay and are highly effective, particularly in types 1 and 2. They work by blunting the surge of adrenaline that most often triggers an episode.
Nadolol is often preferred where it is available, for its steady, long-lasting effect, though other beta-blockers are also used. Treatment is generally lifelong, including for people who have never had symptoms, because the protection depends on it being continuous.
Stopping a beta-blocker suddenly can leave the heart briefly more sensitive to adrenaline, the very trigger the medicine is there to blunt. That is why any change is usually made in stages rather than all at once. Whether, when, and how to change treatment is a decision for the treating cardiologist.
An implantable defibrillator is considered for people at higher risk, particularly anyone who has survived a cardiac arrest or keeps having episodes despite beta-blockers. It acts as a safety net, and beta-blockers continue alongside it.
For the small number who keep having episodes despite treatment, a keyhole operation can cut some of the nerves that carry adrenaline signals to the heart. Known as left cardiac sympathetic denervation, it is done in specialist centres for carefully selected people.
Exercise advice is individual rather than a blanket ban. Many people with well-controlled inherited long QT exercise regularly and play some sports. What suits each person depends on the type, the treatment, and their own history, and is worth discussing with a specialist in inherited heart rhythm conditions.
Questions Worth Discussing
The first thing many people want to know is whether their prolonged QT is thought to be acquired or inherited, since almost everything else follows from that.
Where a medicine or low potassium may be responsible, it helps to know whether it is being stopped or corrected, and when the ECG will be repeated.
Where the inherited form is suspected or confirmed, the questions that tend to matter are which type is involved, whether genetic testing has been done, whether family members should be screened, and what level of activity is appropriate.
Conclusion
A prolonged QT is a measurement rather than a diagnosis, and the reason behind it makes all the difference. For most people it comes down to a medicine or a low blood salt, and correcting the cause corrects the QT.
For people with the inherited form, it is lifelong but manageable. Treatment works well, the triggers are known, and finding it early allows prevention rather than reaction. Where a relative has been diagnosed, screening is worth discussing with your own doctor.
Related Reading
- The Electrocardiogram (ECG / EKG)
- Fainting Spells: What Syncope Might Be Telling You
- Understanding Palpitations: A Cardiologist’s Approach
- When a Standard ECG Isn’t Enough: A Guide to Cardiac Rhythm Monitoring
- Beta-Blockers: One Medicine, Many Uses
- Understanding Ventricular Tachycardia
- Heart Attack vs Cardiac Arrest: What Is the Difference?