







The Pulse Newsletter Expert heart health, in plain English. Fortnightly, from our clinicians. Subscribe →
Section

Conditions

A heart diagnosis can feel overwhelming — but understanding what you have is the first step to feeling more in control. The Conditions section covers the most common heart and cardiovascular conditions in plain language, written by specialist cardiologists. From atrial fibrillation to heart failure, each guide explains what the condition means, how it’s treated, and what life looks like going forward.

Jump to a topic
What a Pacemaker Does, and What Life With One Is Like
Latest in Conditions

What a Pacemaker Does, and What Life With One Is Like

Being told you need a pacemaker can feel like a significant moment. In practice it is one of the most established procedures in cardiology, and for a heart beating too slowly the difference it makes is usually large and quick.

All articles
Cholesterol After Menopause: What Changes and When

Cholesterol After Menopause: What Changes and When

Cholesterol is usually described as drifting up slowly with age. For women through menopause that is wrong in an important way, and one number on the panel can move in the wrong direction while appearing not to move at all.

Infective Endocarditis: The Fever That Needs Explaining

Infective Endocarditis: The Fever That Needs Explaining

Infective endocarditis is an infection of the heart's inner lining, usually settling on a valve. It is uncommon, but the early signs are vague enough that it is often missed. Knowing who is at risk is most of the answer.

Complete Heart Block: What It Means and How It’s Treated

Complete Heart Block: What It Means and How It’s Treated

In complete heart block the top and bottom of the heart stop communicating, and a backup rhythm takes over. It is serious, and it is also among the most fixable problems in cardiology.

Clot-Busting Drugs: When a Heart Attack Is Hours From Help

Clot-Busting Drugs: When a Heart Attack Is Hours From Help

Most towns do not have a catheter laboratory. When someone has a heart attack there, a clot-dissolving drug goes in first and the journey comes second. Here is why that order is the right one.

Pericarditis: Chest Pain That’s Worse Lying Down

Pericarditis: Chest Pain That’s Worse Lying Down

Pericarditis is inflammation of the sac around the heart. The pain is sharp, worse lying flat, better sitting forward, and alarming enough to mimic a heart attack. Here is what causes it and what the evidence supports.

When Blood Pressure Won’t Come Down: What Happens Next

When Blood Pressure Won’t Come Down: What Happens Next

Blood pressure that stays high despite three or more medications has a name, and in most cases an explanation. What clinicians check first, why spironolactone is usually the fourth medicine added, and how narrow the role of renal denervation really is.

Prof. Peter Barlis
Editor's note

Understanding your condition is the single most important thing you can do after a heart diagnosis. Don't just read — ask questions, take notes, bring them to your cardiologist.

Prof. Peter Barlis · Founding Editor, Heart Matters
The Hair Loss Question

The Hair Loss Question

Hair clinics and GPs increasingly send people to check with their heart doctor before starting treatment. There is a good reason for that, and it runs in both directions.

Aortic Dissection: The Chest Pain That Cannot Wait

Aortic Dissection: The Chest Pain That Cannot Wait

Most cardiac emergencies build gradually. An aortic dissection does not. It arrives at full force in people who felt perfectly well moments earlier, and recognising the pain is what gets you to hospital in time.

Cardiac Amyloidosis: The Stiff Heart Condition That’s Now Treatable

Cardiac Amyloidosis: The Stiff Heart Condition That’s Now Treatable

Cardiac amyloidosis is caused by misfolded proteins stiffening the heart muscle, and it is now treatable. Here is what patients need to know about this increasingly recognised and now treatable condition.

Deep read

Second-Degree Heart Block: What the Finding Means

Second-degree AV block means most signals reach the lower chambers of the heart and the occasional one does not. Some causes are entirely benign. Here is what the finding describes and what usually happens next.

by Prof. Peter Barlis
Second-Degree Heart Block: What the Finding Means
Demystifying Heart Failure: HFrEF, HFpEF and HFimpEF Explained

Demystifying Heart Failure: HFrEF, HFpEF and HFimpEF Explained

Being told you have heart failure with reduced or preserved ejection fraction can be confusing. Here is what ejection fraction means and why the distinction matters for treatment.

SCAD: Spontaneous Coronary Artery Dissection: What It Is and What to Expect

SCAD: Spontaneous Coronary Artery Dissection: What It Is and What to Expect

SCAD is a heart attack caused by a tear in the artery wall, not cholesterol. It mostly affects healthy women in their 40s and 50s, and the recovery outlook for most people is genuinely positive.

How to Measure Your Blood Pressure at Home

How to Measure Your Blood Pressure at Home

High blood pressure rarely causes symptoms, which is why measuring it regularly matters. This guide covers how to choose the right monitor and how to get accurate readings at home.

AI in Cardiology: What It Means for Your Heart, and What It Cannot Do

AI in Cardiology: What It Means for Your Heart, and What It Cannot Do

You may have heard that artificial intelligence is changing medicine and felt unsure whether to be excited or uneasy. Here is what AI is genuinely doing in cardiology today, and why your cardiologist, not an algorithm, still makes the decisions.

Aortic Stenosis: When the Heart’s Gateway Narrows

Aortic Stenosis: When the Heart’s Gateway Narrows

The aortic valve opens and closes 100,000 times a day. When it begins to narrow, the heart pays the price. Here is how aortic stenosis develops, how it is diagnosed, and how modern treatment, from open surgery to TAVR, restores flow.

Patent Foramen Ovale (PFO): What the “Hole in the Heart” Finding Really Means

Patent Foramen Ovale (PFO): What the “Hole in the Heart” Finding Really Means

A patent foramen ovale, a small opening in the heart present in around one in four adults, can sound alarming when first mentioned. For most people it is entirely harmless and needs no treatment. Here is when it matters, and when it doesn't.

1234

What a Pacemaker Does, and What Life With One Is Like

heartmatters.com 90

Being told you need a pacemaker can feel like a significant moment. In practice it is one of the most established procedures in cardiology, and for a heart beating too slowly the difference it makes is usually large and quick.

Second-Degree Heart Block: What the Finding Means

second degree av heart block
Key Points

  • Second-degree AV block is an ECG finding. It means most electrical signals reach the lower chambers of the heart normally, but every so often one does not, and a beat is missed.
  • Many people have no symptoms at all and only learn about it because an ECG was done for another reason. Where symptoms do occur, tiredness, light-headedness, breathlessness on exertion and fainting are the usual ones.
  • There is more than one pattern, and they are not managed in the same way. Working out which pattern is present, and what it means for you, is a job for your cardiologist rather than something the label alone can settle.
  • Some causes are entirely benign, including being very fit, being asleep, and taking common heart medications.
  • Management ranges from doing nothing beyond keeping an eye on it, through adjusting medication, to a pacemaker where the pattern warrants it.

Second-degree AV block is one of those phrases that appears on a report and stops you in your tracks. The word block suggests something obstructed, and a second degree of it implies there is a first and a third, which invites the immediate question of how bad this one is.

It is worth knowing what the finding describes, what it might explain about how you have been feeling, and what usually happens next. It is also worth saying early that the answer depends a good deal on the detail, and that the detail is something your own cardiologist is best placed to work through with you.

What the Finding Describes

Every heartbeat starts in the upper chambers of the heart and travels down through a junction called the atrioventricular node to the lower chambers, which do the pumping.

In second-degree block, most of those signals get through as they should. Occasionally one does not. When that happens the lower chambers receive no instruction and no beat occurs. On the ECG tracing this shows as a signal from the upper chambers with nothing following it.

It sits between the two other degrees. In a first-degree block, every signal still arrives, just later than usual. In complete heart block, none of them do. Second-degree is the middle ground, where most arrive and some do not.

The Pattern Matters More Than the Name

Missed beats can follow more than one pattern, and this is the part that genuinely determines what happens next.

In one pattern, the delay between the upper and lower chambers stretches a little with each beat until one signal fails to get through. In the other, the delay stays exactly the same and then a beat simply vanishes with no build-up at all.

Two ECG tracings compared. In the first pattern the gap between the signal and the beat lengthens progressively until a beat is dropped. In the second the gap stays constant and a beat is dropped without any warning
The two patterns. In the first the delay stretches with each beat before one fails. In the second every delay is identical and a beat simply disappears. Your report may refer to these as Mobitz I and Mobitz II, after the physicians who first described them, Heart Matters

Those two patterns arise in different parts of the heart’s wiring, which is why they behave differently over time and why they are approached differently. Your report may name them, usually as Mobitz I and Mobitz II, and occasionally Wenckebach. Those are simply the surnames of the doctors who described them, so the words themselves tell you nothing.

What they do tell your cardiologist is a good deal, and that is really the point. Two people can have the same three words on a report and end up with very different plans, neither of which is deducible from the label alone.

What It Might Feel Like

A great many people feel nothing whatsoever and are surprised to be told about it, particularly when the ECG was done for an unrelated reason.

Where symptoms do occur, they follow from the heart rate being effectively lower than it should be. Tiredness that is out of proportion to what you have been doing is common, as is breathlessness on exertion. Light-headedness, particularly on standing or during activity, can occur. So can fainting, and that one carries more weight than the others.

People sometimes notice the missed beats themselves, described as a pause or a stumble in the pulse. Others notice nothing at all even when the ECG shows beats being dropped regularly.

Symptoms tend to matter more than the pattern on paper. Someone feeling well with a reassuring pattern is in a different position from someone fainting with the same one, which is another reason this is a conversation rather than a lookup.

Two people can have the same three words on a report and quite different plans. The label describes the finding, not the situation.

What Causes It

Several of the causes are entirely benign, which is worth saying plainly.

Being very fit is one of them. Endurance training increases the nervous system’s braking influence on the heart, and in athletes this pattern can appear at rest and disappear entirely on exertion.

Being asleep produces the same effect for the same reason, which is why it sometimes shows up on overnight monitoring in people with completely normal hearts.

Medications are a frequent explanation. Beta-blockers, some calcium channel blockers and digoxin all slow conduction deliberately, and in some people that is enough to produce dropped beats.

Wear in the heart’s wiring accumulates with age, much as it does in other tissues, and is a common cause in older people.

Less commonly, it follows a heart attack or cardiac surgery, or accompanies conditions that affect the heart muscle itself.

How It Is Assessed

The ECG that found it is the starting point, and often it shows enough on its own.

Where the picture is unclear, or where the finding comes and goes, longer monitoring over a day or more gives a fuller view than a ten second tracing in a clinic ever could.

An exercise test can be informative, because the two patterns tend to respond to exertion in opposite directions. A review of your current medications is usually part of it. An echocardiogram may be arranged to look at the heart’s structure and pumping.

Your own account of symptoms carries real weight here, so it is worth being specific: what you felt, when, what you were doing, and whether it has happened more than once.

What Management Might Involve

There is a genuine range, and where someone sits within it depends on the pattern, the symptoms, and the cause.

For some people the answer is simply to know about it and be reviewed periodically, particularly where the cause is benign and there are no symptoms.

Where a medication is contributing, adjusting or changing it may resolve the problem, and that is often the first thing considered.

Where the pattern is one that tends to progress, or where symptoms such as fainting are occurring, a pacemaker is the usual recommendation. It is a well-established treatment, generally done under local anaesthetic with sedation, and it reliably resolves symptoms caused by dropped beats.

There is no medication that restores conduction through faulty wiring, which is why a device rather than a tablet is the answer when treatment is needed.

Conclusion

Second-degree AV block describes something specific and fairly narrow: most signals arriving as they should, and the occasional one not. In some people it reflects nothing more than a well-trained heart or a medication doing its job. In others it needs treating, and the treatment works well.

What the phrase on the report cannot tell you is which of those applies to you. That comes from the pattern, your symptoms, the cause, and the rest of your heart health considered together. If you have been given this finding, the questions worth taking to your cardiologist are what pattern is present, whether anything you are taking might be contributing, and whether anything needs doing now or simply keeping an eye on.

Related Reading

Cholesterol After Menopause: What Changes and When

menopause cholesterol
Key Points

  • The cholesterol rise around menopause is driven by the ovaries winding down, not by getting a year older. It appears over a short window rather than drifting slowly across midlife.
  • Studies that followed the same women year after year found LDL cholesterol climbed sharply within about a year either side of the final period, then levelled off at the higher level.
  • HDL cholesterol is the misleading part. The number often holds steady or rises during this time, while the particles themselves change in ways that make them work less well.
  • Women whose LDL rose fastest across this window were more likely to have plaque in their neck arteries years later than women whose LDL rose more slowly.
  • An earlier menopause means the altered cholesterol pattern starts sooner and lasts longer.

Cholesterol is usually described as something that creeps upward with age, the same way for everyone. For women going through menopause, that description misses something important. The change is not a slow creep. It is not about getting older.

It is a distinct shift, and it clusters around one point in time. It is also easy to miss, because the years in which it happens are crowded with symptoms that feel far more pressing.

What Actually Changes

Oestrogen affects how the liver handles cholesterol. It helps keep active the docking points on liver cells that pull LDL particles out of the bloodstream. As oestrogen falls, that removal slows down, and LDL levels rise.

Total cholesterol rises alongside it. So does a measure called apolipoprotein B, usually shortened to apoB. Rather than measuring how much cholesterol is being carried, apoB counts how many of the particles that lodge in artery walls are in the blood. That count often tells more than an LDL figure on its own.

Body shape tends to change over the same years, with more fat settling around the middle. That affects how the body handles both cholesterol and blood sugar, and it adds to the picture.

The Window Around the Final Period

The most useful research followed the same women repeatedly across the transition. That design answers a question earlier studies could not: whether the cholesterol changes belong to the ovaries winding down, or to the calendar.

The answer is reasonably clear. LDL cholesterol and apoB rise sharply within about a year either side of the final period. They then settle at the higher level rather than continuing to climb. That is not the pattern ageing produces on its own.

Not everything on a blood test behaves this way. Triglycerides, blood pressure, and blood sugar also tend to drift upward through midlife. They follow the slower line of age rather than clustering around the final period. The same menopause pattern appeared in every ethnic group studied.

How big is the change?

Small, in any single year. That is much of the reason it goes unnoticed.

One study looked at how fast LDL climbed across this window and then scanned the same women’s neck arteries more than a decade later. Women in the fastest-rising third, gaining roughly 0.19 mmol/L (about 7 mg/dL) a year or more, were about half as likely again to have plaque in those arteries as women in the slowest-rising third, who gained under about 0.14 mmol/L (5 mg/dL) a year.

The gap between those two groups is not dramatic on a single blood test. It is the kind of difference that would be easy to dismiss as noise. What made it visible was measuring the same women repeatedly, and this is an observed link rather than proof that the cholesterol change caused the plaque.

Rises sharply

LDL cholesterol, total cholesterol, and apoB. The climb sits in the year before and after the final period, then levels off.

Looks unchanged, but is not

HDL cholesterol often holds steady or rises. Underneath, larger particles decline, smaller ones increase, and each one clears less cholesterol.

Carries forward

Cholesterol changes measured across this window have been linked to thickening and plaque in the neck arteries years afterwards.

The HDL Number That Misleads

This part deserves more attention than it gets, because an ordinary blood test can offer false reassurance.

HDL cholesterol has long been treated as the good number. Across the menopause transition it often stays level or even rises. Taken at face value, that reads as encouraging news.

Looking at the particles themselves tells a different story. In the couple of years around the final period, the larger HDL particles decline and the average particle gets smaller. The number of small particles rises. Each particle also becomes less effective at collecting cholesterol out of tissue and carrying it away. More particles, each doing less.

A steady HDL number through menopause is not proof that nothing has changed. It is one of the few figures on the panel that can move in the wrong direction while appearing not to move at all.

The practical consequence is that a reassuring HDL result does not cancel out a rising LDL or apoB when a test from these years is being interpreted.

Why This Gets Missed

Several things converge. The transition brings symptoms that are immediate and disruptive. A cholesterol test competes poorly for attention against broken sleep, hot flushes, night sweats, and low mood.

Heart risk assessment in women has also historically happened less often and later than in men. That pattern is examined further in the article on why women’s heart health is different.

Risk calculators add their own problem. Most lean heavily on age. A woman in her early 50s can return a low 10-year risk score at exactly the moment her cholesterol is changing fastest. The score is not wrong on its own terms. It is answering a question about the next decade, not about the direction of travel.

Timing matters too. A woman whose last period comes in her mid-40s spends more years with the altered pattern than one who reaches it at 55. A calculator reading age alone does not capture that.

What Can Be Measured

A cholesterol test taken during the transition says more when there is an earlier one to compare it against. The direction of change carries information a single figure does not. This is why the researchers behind the artery findings suggested that checking cholesterol more often through perimenopause may be worth considering. Where apoB is available, it adds the particle count to the picture.

Lipoprotein(a) is largely inherited and is usually measured once in a lifetime rather than tracked. It does not appear to change with menopause. It is worth knowing about all the same, because it is a test many people never have at all, and the transition is one of the points at which it tends to come up.

Sometimes a risk score still leaves real uncertainty about what the arteries are doing. Several further tests exist. Whether any of them is worth considering, and which one, depends entirely on the individual picture, and that is a decision made with a doctor who knows the full history.

More testing is not automatically better. Each test has limitations as well as uses, none is used routinely, and guidance on who they suit differs from one country to the next. Heart Matters covers the coronary calcium score separately for readers who want to understand what one of these tests involves.

Where Hormone Therapy Fits

This is the question that comes up most often, and the answer has two parts that are easy to run together.

Hormone therapy does change cholesterol. It lowers LDL. Tablets also raise triglycerides in a way that patches and gels largely do not, which is one reason the two forms are not interchangeable. Tablets pass through the liver before reaching the bloodstream, and the liver is where most cholesterol handling happens.

The second part is the one that gets lost. Hormone therapy is not prescribed to prevent heart disease. Current guidance does not support using it for that purpose, and a better cholesterol reading on its own is not treated as a reason to start it.

That is not the same as saying it is off the table. Where hormone therapy is being considered for menopausal symptoms, its effect on cholesterol is one factor weighed within that decision, alongside age, time since the final period, and personal and family history. The wider discussion of timing and heart risk sits in the women’s heart health article.

What Else Helps

Nothing here is specific to menopause, but it all carries more weight when LDL is rising. Beta-glucan, the soluble fibre in oats, has consistent evidence for lowering LDL at amounts achievable in an ordinary breakfast. Phytosterols work a different way, by reducing how much cholesterol the gut absorbs.

Resistance training deserves a specific mention through these years. The loss of muscle that comes with the transition affects how the body handles cholesterol and blood sugar as well as bone strength, and aerobic exercise on its own addresses that less well.

Where cholesterol levels warrant medication, there is a historical point worth knowing. Statins have been prescribed to women less often, and at lower doses, than to men with comparable risk, despite the trial evidence supporting their use. The questions women raise most often are covered in the article on what patients ask most about statins.

What These Conversations Usually Cover

Cholesterol during menopause is not a single number to be judged pass or fail. These are the three things that tend to shape the discussion.

The direction, not just the number

Whether an earlier result exists to compare against. A figure inside the normal range can still be moving quickly.

When menopause happened

The age of the final period sets how many years the altered pattern has been running. Most risk scores do not ask.

What the score is measuring

A 10-year risk score answers a question about the next decade. It is not designed to flag a change happening now.

Heart Matters Resource

When in Doubt, Get Checked Out

Cholesterol changes quietly and causes no symptoms. Chest discomfort, unusual breathlessness, and unexplained fatigue are a different matter entirely, and in women they are more often put down to something else first.

Read: When in Doubt, Get Checked Out →

Conclusion

The cholesterol changes of menopause are not dramatic in any single reading. That is much of the reason they pass unremarked. They amount to a modest rise in LDL, a modest rise in apoB, and an HDL figure offering reassurance it has not entirely earned.

What gives them weight is the link between changes measured across this window and the state of the arteries years afterwards. Menopause is not only a set of symptoms to be managed. It is also a point at which the long-term picture shifts, and one of the few moments when a blood test taken at the right time says more than the same test taken at any other.

Related Reading

Infective Endocarditis: The Fever That Needs Explaining

infective endocarditis
Key Points

  • Infective endocarditis is an infection of the heart’s inner lining, usually settling on one of the valves. It is uncommon, but it is serious and it is often diagnosed later than it should be.
  • The people most at risk are those with an artificial replacement valve, those who have had this infection before, and those with certain valve or congenital heart conditions.
  • The symptom that matters most is a fever that will not go away. In someone with a known valve problem, a replacement valve, or a previous episode, an unexplained fever warrants assessment rather than waiting.
  • Blood cultures taken before antibiotics are started are what make the diagnosis. Starting antibiotics first can make the infection much harder to identify.
  • Guidance on antibiotics before dental work has narrowed considerably. It is now reserved for a defined high-risk group, and recommendations differ between countries.
  • Everyday dental hygiene is now understood to matter more than any single dose of antibiotics before a procedure, because most bloodstream exposure comes from ordinary chewing and brushing rather than from the dentist.

Most heart conditions announce themselves with chest pain, breathlessness, or a change in rhythm. Infective endocarditis often announces itself as feeling generally unwell for weeks, with a low-grade fever that nobody can explain, and that is precisely why it is so frequently missed.

It is uncommon. Most cardiologists see a handful of cases a year rather than a handful a week. But it carries real risk if it is not identified, and the people most likely to develop it are often the people best placed to recognise it early, because they already know they have a valve problem.

What It Actually Is

The inside of the heart, including the surface of each valve, is lined with a thin smooth membrane called the endocardium. Blood passes over it constantly without sticking, which is exactly what you want.

Bacteria get into the bloodstream more often than most people realise. Brushing teeth, chewing food, a minor skin infection, a cannula in the arm. In a healthy heart the immune system clears them within minutes and nothing happens.

The problem arises where the lining is not smooth. A damaged or leaking valve, an artificial replacement valve, or a patch of scarring creates turbulence and a surface bacteria can stick to. Once attached, they build up a mass of infected material called a vegetation, which is protected from both the immune system and, to a degree, from antibiotics reaching it.

Infective endocarditis compared with a healthy heart valve. The healthy valve has smooth leaflets that close cleanly. The infected valve carries a lumpy mass called a vegetation on one leaflet, which stops it closing properly and can shed fragments into the bloodstream
A healthy valve above, and one carrying a vegetation below. The mass destroys the leaflet it sits on, stops the valve closing properly, and can shed fragments into the circulation, Heart Matters

Three things follow from that vegetation, and they explain almost every symptom of the disease. It destroys the valve it sits on. It sheds fragments into the circulation. And it drives a continuous inflammatory response that makes the person feel systemically unwell.

Who Is Actually at Risk

This is not a random event. Risk is concentrated in identifiable groups, and clinicians sort people into three tiers. The tier matters for two reasons: it changes how seriously an unexplained fever is taken, and it determines whether preventive antibiotics are recommended before dental work.

Highest risk
Preventive antibiotics before dental work are generally recommended
  • An artificial replacement valve, or artificial material used to repair a valve. Doctors call these prosthetic valves. They come in two kinds: mechanical ones made from man-made materials, and tissue ones made from treated animal or human tissue. Neither has the natural resistance to infection that a person’s own healthy valve does.
  • A previous episode of endocarditis. The valve has already been damaged once, which makes it easier for bacteria to settle again.
  • Certain congenital heart conditions, meaning those present from birth. This includes unrepaired defects such as a ventricular septal defect, the more complex conditions usually identified and treated in childhood, and any defect repaired using artificial material.
Moderate risk
Antibiotics considered case by case, not routinely
  • Significant valve disease, such as narrowing of the aortic valve, or mitral valve prolapse where the valve also leaks significantly. Prolapse without leaking, and the mild leaking commonly reported on a routine scan, are not in this group.
  • Rheumatic heart disease, which remains a leading cause worldwide and accounts for a large share of cases wherever rheumatic fever is common.
  • An implanted cardiac device such as a pacemaker or defibrillator, where infection can settle along the wires rather than on a valve.
  • Thickened heart muscle or other structural abnormalities that disturb the flow of blood across a valve.
A separate route in
Risk comes from bacteria entering the blood, not from the valve itself
  • Injecting drug use. A distinct and significant risk, and one that tends to affect the right side of the heart, which changes how the illness presents and which valve is involved.
  • Long-term intravenous lines, dialysis access, and repeated hospital procedures. Each provides bacteria with a direct route into the circulation, and this group now accounts for a growing share of cases.
  • Poor dental and gum health. Inflamed gums release bacteria into the bloodstream during ordinary chewing and brushing, day after day.

Most people fall into none of these groups, and for them the everyday risk is negligible. The reason the tiers matter is that they change the answer to two practical questions: what to do about a fever that will not settle, and what to do before a dental appointment.

The Symptom That Matters Most

If there is one thing worth taking from this article, it is this: an unexplained fever, in someone with a valve condition or a replacement valve, is worth investigating rather than waiting out.

The fever is often low grade. It comes and goes. It is easily attributed to a virus, and frequently is one. But the average delay between symptoms starting and diagnosis being made runs into weeks, and almost all of that delay comes from the illness looking unremarkable at the start.

Alongside fever, the common features are drenching night sweats, profound tiredness, loss of appetite, weight loss without trying, and aching joints or muscles. Taken individually each is unremarkable. Taken together, over weeks, in someone with a valve problem, they form a recognisable picture.

A fever with no obvious source, in a person with a valve problem, is endocarditis until something else explains it.

A/Prof. Nagesh Anavekar, Cardiologist

Less common but more specific signs exist, and clinicians look for them: small dark streaks under the fingernails, tender spots on the fingers or toes, painless marks on the palms and soles, and small haemorrhages in the eye. These are the classic findings described in textbooks, though they appear in a minority of modern cases.

Sometimes the first sign is not the infection itself but a fragment breaking off. That can cause a stroke, a sudden loss of blood supply to a limb, or pain in the back or abdomen. A stroke in a younger person with a fever is a combination that prompts a search for this diagnosis.

Why the Order of Tests Matters

The diagnosis rests on two things: growing the responsible bacteria from a blood sample, and seeing the mass on an ultrasound of the heart.

Blood cultures come first, and the timing genuinely matters. A blood culture is simply a blood sample kept warm in the laboratory for several days to see whether any bacteria grow from it, which identifies exactly what is causing the infection. Several sets are taken from different sites over a period of hours. Once antibiotics have been started, the bacteria may not grow, and a case where nothing is ever identified is considerably harder to treat because the choice of antibiotic becomes guesswork.

This is the practical reason clinicians are reluctant to start antibiotics for an unexplained fever before cultures are taken, and it can look like inaction to a worried patient. It is the opposite.

An echocardiogram follows. A standard scan through the chest wall detects many of these masses but misses smaller ones, and it sees replacement valves poorly because artificial material scatters the ultrasound beam.

Watch: what an echocardiogram involves and what it shows, Heart Matters Educational Series

Where suspicion is high, or a replacement valve is involved, a transoesophageal echocardiogram is used instead. The probe sits in the oesophagus, directly behind the heart, and the improvement in image quality is substantial. It is the test that most often settles the question.

Blood tests showing signs of inflammation in the body support the picture without confirming it, and additional scans are sometimes used in difficult cases, particularly around replacement valves and the wires of implanted devices.

How It Is Treated

Treatment is a long course of antibiotics given directly into a vein, typically between two and six weeks depending on which bacteria are responsible and whether a replacement valve is involved. It is not a condition treated with tablets at home, at least not initially, because the concentration of antibiotic needed to penetrate a vegetation cannot be achieved by mouth.

Many people spend the first part of that course in hospital and complete the rest through a home intravenous service where one is available.

Surgery is needed in a substantial minority of cases, not because antibiotics have failed but because of what the infection has already done. The usual reasons are a valve destroyed badly enough to cause heart failure, infection that will not clear despite appropriate treatment, a large vegetation at high risk of shedding fragments, or a pocket of infection forming in the tissue around the valve.

The decision on whether and when to operate is made jointly by cardiologists, surgeons and infection specialists, and the timing is often finely balanced.

The Dental Antibiotics Question

This is where most confusion sits, and the confusion is understandable because the advice genuinely changed.

For decades, anyone with almost any valve abnormality was given antibiotics before dental work. That approach was abandoned because the evidence did not support it. The number of people needing to be treated to prevent one case was enormous, and antibiotics carry their own risks.

What replaced it is narrower. Preventive antibiotics before dental procedures involving the gums are now generally reserved for those at highest risk: people with an artificial replacement valve or artificial repair material in the heart, those who have had endocarditis before, and some people with congenital heart conditions.

Recommendations differ between countries. Guidance in the United Kingdom went further than that in Europe, the United States and Australia, and the position has shifted more than once. So the reliable answer is not what a general article says, but what your own cardiologist and dentist agree applies to you, and it is a reasonable thing to have written down.

The more important shift is what replaced the antibiotics.

Ordinary daily activities, chewing and brushing, release bacteria into the bloodstream far more often across a year than any dental appointment does. Someone with inflamed gums does this constantly. That is why routine dental care and good gum health are now regarded as the more meaningful protection, and why cardiologists ask about dental checkups in a way that can seem beside the point.

⚠
When to Seek Medical Assessment

For anyone with a replacement valve, a known valve problem, a previous episode of this infection, or an implanted device such as a pacemaker, the following warrant prompt assessment rather than waiting:

  1. A fever with no obvious cause that is not settling.
  2. Night sweats, unintended weight loss, or persistent exhaustion.
  3. Any sudden neurological symptom, or a limb that becomes painful, cold or pale.

It is worth mentioning the valve condition explicitly when seeking help, because it changes how a fever is interpreted. It is also worth asking whether blood cultures should be taken before any antibiotic is started, since that decision shapes everything that follows.

The Outlook

Infective endocarditis is a serious illness and it would be dishonest to present it otherwise. It carries meaningful risk even with good treatment, and that risk is higher with replacement valves and with certain bacteria.

What consistently improves the picture is time to diagnosis. Cases identified early, with the bacteria successfully identified from blood cultures and the right antibiotics started promptly, do considerably better than those found after weeks of an unexplained illness.

Which is the reason this article exists. The single thing most likely to change an outcome is a person with a valve condition, feeling vaguely unwell with a low fever, deciding it is worth mentioning.

The Essentials in One Place

Question The short answer
What are the symptoms? A fever with no obvious cause that is not settling. Drenching night sweats, tiredness out of proportion to activity, loss of appetite, weight loss without trying, and aching joints or muscles. Occasionally the first sign is a stroke or a suddenly painful limb.
Who is most at risk? Highest risk: an artificial replacement valve or artificial repair material, a previous episode, and certain congenital heart conditions. Moderate risk: significant valve disease, rheumatic heart disease, and implanted cardiac devices. Separately: injecting drug use, long-term intravenous or dialysis lines, and poor gum health.
When should assessment be sought? Promptly, for anyone in those groups with an unexplained fever. Immediately, for any sudden neurological symptom, or a limb that becomes painful, cold or pale.
What confirms the diagnosis? Blood cultures taken before any antibiotic is started, together with an ultrasound of the heart. A transoesophageal echocardiogram is often needed, particularly where a replacement valve is involved.
What does treatment involve? Antibiotics given into a vein, usually for two to six weeks. Surgery in a substantial minority, generally because of damage the infection has already caused rather than because antibiotics have failed.

Conclusion

Infective endocarditis is uncommon enough that most people will never encounter it, and serious enough that anyone in a higher risk group benefits from recognising it.

The essentials are few. Fever without explanation matters more in someone with a valve problem than in anyone else. Blood cultures before antibiotics are what make the diagnosis possible. And routine dental care does more good over a lifetime than any single preventive dose.

Anyone with a replacement valve, a previous episode, or significant valve disease would reasonably want to know where they sit on the current guidance, and that is a conversation worth having at a routine appointment rather than in an emergency department.

Sources

Related Reading

Complete Heart Block: What It Means and How It’s Treated

complete heart block
Key Points

  • In complete heart block, also called third-degree AV block, the electrical signals from the top of the heart stop reaching the bottom. The lower chambers fall back on their own slower backup rhythm to keep going.
  • Unlike the milder degrees of block, this one usually causes symptoms and usually needs treating. Fainting, near-fainting, marked breathlessness, and profound tiredness are the common ones.
  • The most frequent cause is gradual age-related wear in the heart’s wiring. Medications, a recent heart attack, and heart surgery are the other common explanations.
  • A pacemaker is the usual treatment, and it is genuinely effective. This is one of the few serious cardiac diagnoses where a single procedure restores normal life almost completely.
  • Fainting without warning, particularly in an older person, warrants urgent assessment rather than a wait-and-see approach, because it can be the first sign.

Of all the findings that appear on an ECG report, complete heart block is the one where the alarming name is closest to the truth. Where a first-degree block is really just a delay, and a second-degree block means the occasional missed beat, complete heart block means what it says. The signal is not getting through at all.

That sounds frightening, and it is a serious diagnosis. But it also happens to be one of the most fixable problems in cardiology. The heart has a built-in fallback that keeps things going, and modern treatment addresses the underlying fault directly rather than merely managing it.

What Is Actually Happening

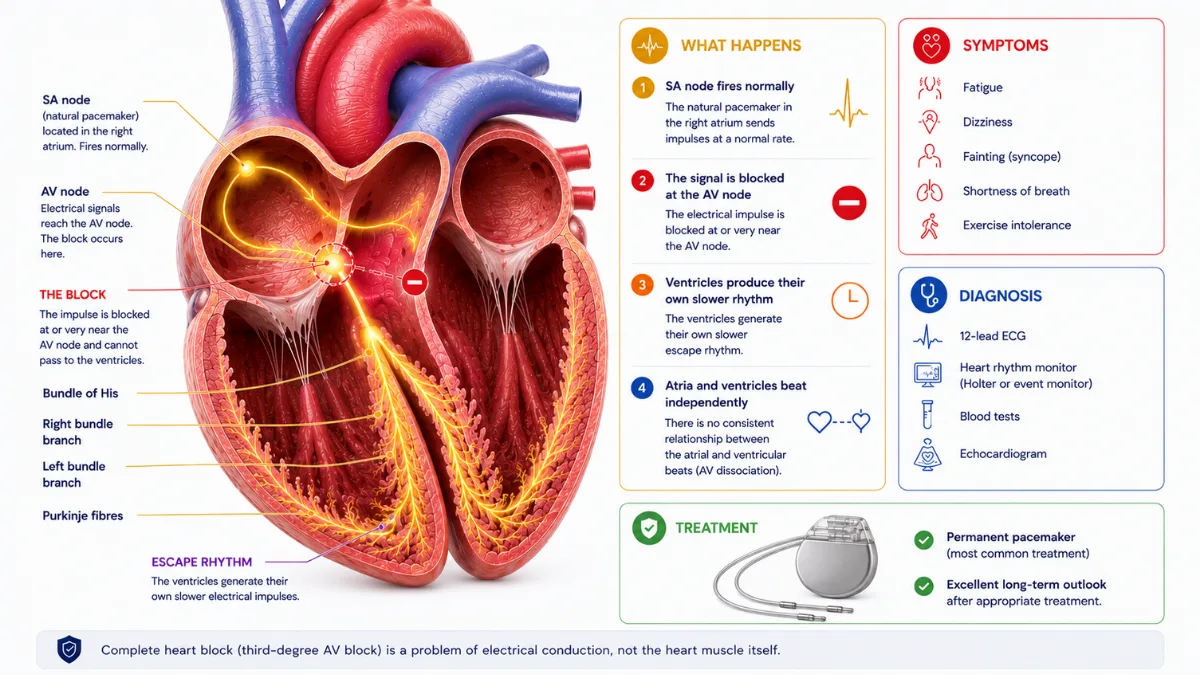
Cross-section of the heart showing the conduction system. The SA node fires normally in the upper chambers, the impulse is blocked at the AV node, and the ventricles generate their own slower escape rhythm. Side panels summarise what happens, the symptoms, how it is diagnosed, and the treatment
Where the failure sits. The signal starts normally in the SA node, stops at or near the AV node, and the lower chambers fall back on their own slower escape rhythm. This is a problem of electrical conduction, not of the heart muscle itself, Heart Matters

Every heartbeat starts in the upper chambers of the heart, the atria. The signal travels down to a junction called the atrioventricular node, then on to the lower chambers, the ventricles, which do the pumping.

In complete heart block, that connection has failed. The upper chambers carry on firing at their normal rate, entirely unaware that nothing is getting through. The lower chambers, receiving no instruction, fall back on their own built-in backup pacemaker.

This backup exists precisely for this situation, and it is why complete heart block is not immediately fatal. But it is a poor substitute. It fires slowly, often somewhere between 20 and 40 beats per minute against a normal 60 to 100, and unlike the normal rhythm it does not speed up when you climb stairs or hurry for a bus.

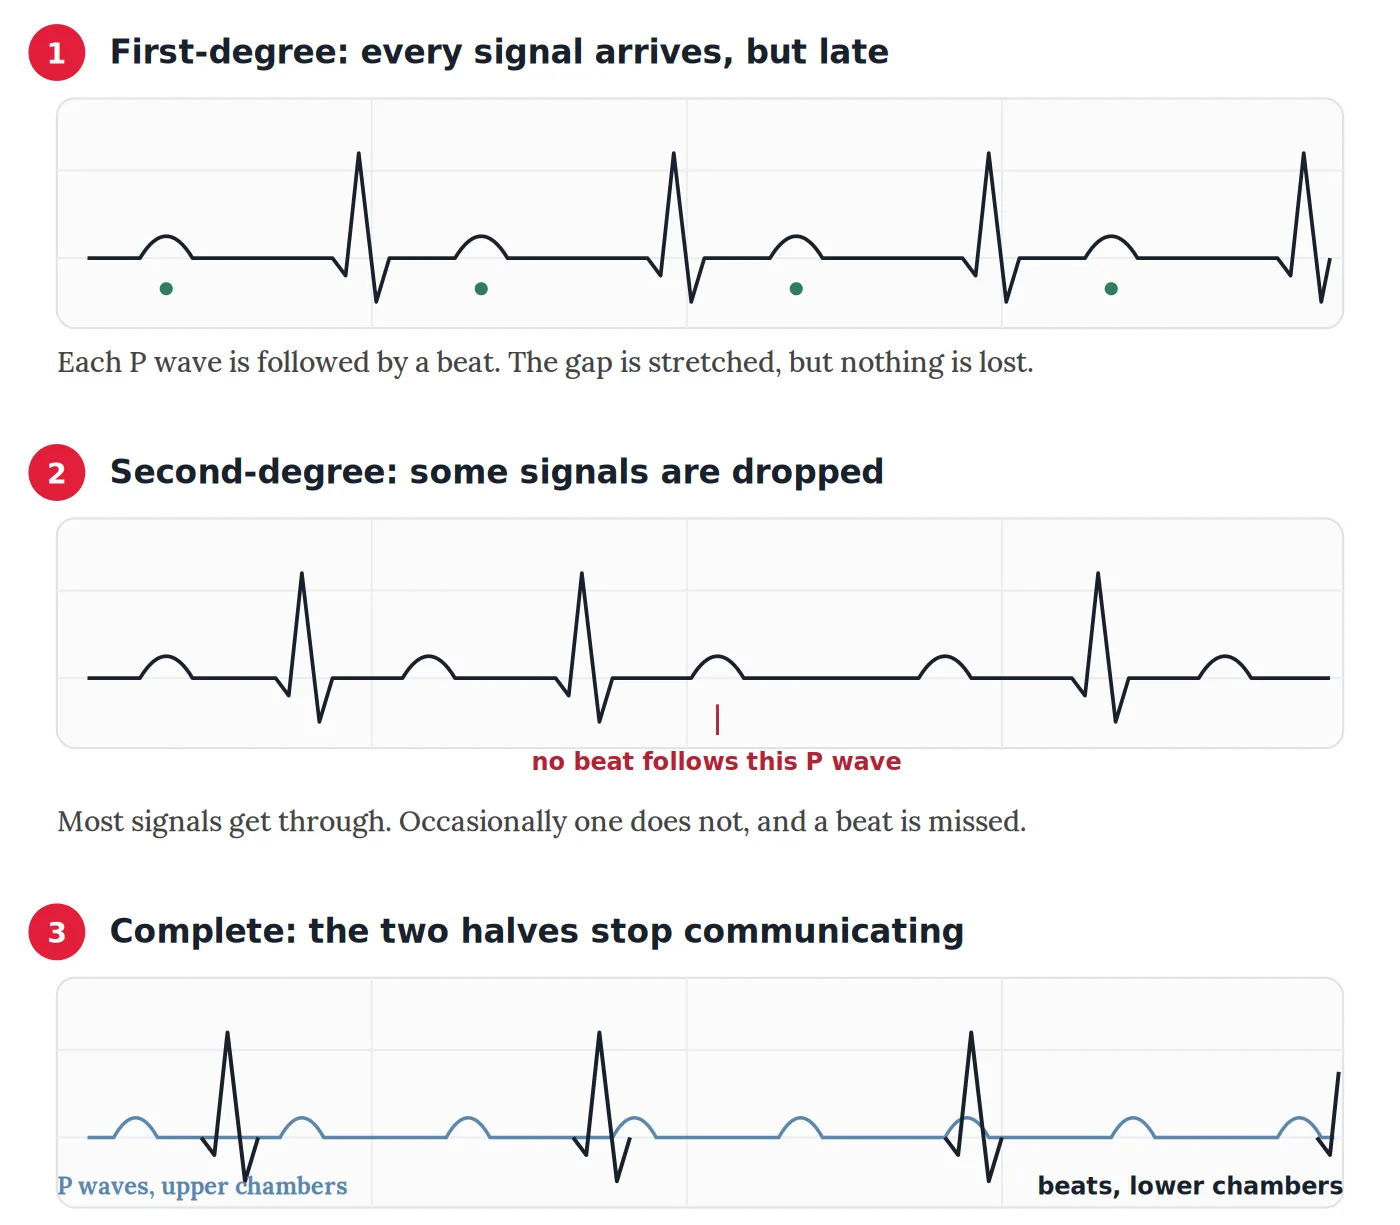
Three ECG tracings compared. In first-degree block every P wave is followed by a beat after a long delay. In second-degree block some P waves are not followed by a beat. In complete heart block the P waves and the beats are entirely independent of each other
The three degrees compared. In the third, the small P waves from the upper chambers and the tall beats from the lower chambers march along at their own separate rates, with no relationship between them, Heart Matters

On the ECG this produces a distinctive pattern that a cardiologist can recognise instantly. The P waves are regular. The beats are regular. But they bear no relationship to one another, each marching to its own timing. Doctors call this atrioventricular dissociation, and it is the signature of the diagnosis.

What It Feels Like

Most people with complete heart block feel something is wrong, though what they feel varies a great deal and is often mistaken for something else.

Fainting or near-fainting is the classic presentation, and it has a particular character. There is often no warning, no dizziness building beforehand, no sense of the world closing in. The person is simply on the floor, and then, usually within a minute, entirely alert again. That pattern of sudden collapse with rapid full recovery is quite specific, and it is worth describing precisely to a doctor, because it points towards a rhythm cause rather than the many other reasons for fainting.

Breathlessness and exhaustion are common and often the earlier signs. With a heart rate stuck at 35 and unable to rise, ordinary exertion becomes hard work. People frequently put this down to age or being out of condition, sometimes for months.

Chest discomfort, confusion, or a general sense of being unwell can appear too, particularly in older people, where the presentation can be vague enough that the heart is not the first suspicion.

A pulse that is persistently very slow is the physical sign, and it is often what prompts the ECG in the first place. Some people, though, feel surprisingly little, particularly if the block came on gradually and the backup rhythm is at the faster end of its range.

Fainting with no warning and full recovery within a minute is one of the more specific stories in cardiology. It is worth describing exactly as it happened.

What Causes It

Age-related wear is the most common cause by some margin. The heart’s conduction tissue develops fibrous change over decades, much as other tissues do, and eventually the connection fails. This is why complete heart block is predominantly a condition of later life and often arrives without any other heart disease at all.

Medications can cause it or contribute to it. Beta-blockers, certain calcium channel blockers, digoxin, and antiarrhythmic drugs all slow conduction deliberately. In a conduction system already worn, that can be enough to tip it over. This possibility is always considered, because a block caused by medication may resolve when the medication is adjusted.

A recent heart attack can interrupt the blood supply to the conduction tissue. Block occurring in this setting sometimes recovers over days as the surrounding muscle settles, which is why temporary pacing is often used first rather than going straight to a permanent device.

Heart surgery or valve procedures carry a recognised risk, because the conduction tissue runs close to the aortic valve. Some blocks after these procedures recover and some do not.

Less common causes include infiltrative conditions such as cardiac amyloidosis and sarcoidosis, certain infections, and inflammatory conditions. These are considered particularly when the person is younger than the usual pattern would suggest.

Congenital complete heart block is a separate entity present from birth. The backup rhythm in these cases often sits higher in the conduction system, runs faster, and is better tolerated, so some people live with it for years before it is picked up.

Why This One Is Different

It is worth being clear about why complete heart block is treated more seriously than the milder degrees, because the difference is real rather than a matter of degree.

A backup rhythm is not a reliable rhythm. It can slow further, and it can pause. A pause of a few seconds causes a faint. A longer pause is dangerous. The risk is not that the heart is beating slowly today, but that the arrangement keeping it beating at all is not a dependable one.

There is also no medication that fixes it. Slow heart rhythms in general have very few drug options, and none that restore conduction through a failed connection. That is the reason a device is the answer rather than a tablet.

What Happens Next

Confirmed complete heart block usually means admission to hospital rather than management as an outpatient, and things tend to move relatively quickly.

The first step is to look for a reversible cause. Medications that could be responsible are stopped or held. Blood tests check for electrolyte problems and thyroid function. If a recent heart attack is the cause, the situation is watched, because recovery is possible.

Where the heart rate is dangerously slow in the meantime, a temporary pacing wire can be placed to hold things steady while the picture becomes clear.

If the block is not reversible, and in most cases it is not, a permanent pacemaker is the treatment. The procedure is usually done under local anaesthetic with sedation, takes an hour or two, and most people go home the following day.

The Genuinely Reassuring Part

Complete heart block is a serious diagnosis with an unusually good ending. A pacemaker does not manage the problem or slow its progression. It replaces the failed connection and restores a normal heart rate, including the ability to speed up on exertion, which modern devices handle automatically.

People who were fainting stop fainting. People who had become breathless walking to the shops generally find that resolves. Life expectancy for someone with a pacemaker for heart block is close to that of anyone else their age.

Watch: a closer look at the pacemaker itself, how it is implanted, and what it does once it is in place, Heart Matters Educational Series

The trade-offs are real but modest: a small scar below the collarbone, periodic device checks, a battery change every several years, and a few practical considerations around strong magnetic fields. Set against a heart that was stopping intermittently, most people regard that as a fair exchange.

⚠
When to Seek Urgent Help

Call your local emergency number if any of the following occur:

  1. Fainting or collapse without warning, particularly if it has happened more than once.
  2. A pulse that is persistently very slow alongside breathlessness, confusion, or chest discomfort.
  3. Near-fainting on standing or on exertion that is new or worsening.

Fainting has many causes and most are not dangerous. What makes it worth treating urgently is the combination of no warning, rapid full recovery, and older age, because that pattern can be the first presentation of a conduction problem. An ECG at the time settles it quickly.

Conclusion

Complete heart block is the one degree of AV block where the alarming name matches the situation. The connection between the top and bottom of the heart has failed, and what is keeping things going is a backup that was never meant to run the show.

It is also, once identified, among the most solvable problems in cardiology. A single procedure restores what was lost, and people generally return to the life they had before the symptoms started. The part that matters is getting to the diagnosis, which is why unexplained fainting in an older person is worth taking seriously rather than putting down to a funny turn. Anyone who has had that experience, or who has been told their pulse is unusually slow, would reasonably want an ECG and a conversation with their doctor about it.

Related Reading

Clot-Busting Drugs: When a Heart Attack Is Hours From Help

heart attack fibrinolysis clot-busting drugs
Key Points

  • A heart attack happens when a clot blocks an artery supplying the heart. Whatever else follows, that artery has to be opened, and quickly.
  • In a large hospital this is done with a thin tube passed up to the heart, then a balloon and a stent. In a hospital without that facility, the first step is a drug given into a vein that dissolves the clot.
  • The drug is not a second-rate substitute. When the specialist hospital is more than about two hours away, it opens the artery sooner than the journey would, and sooner is what counts.
  • The main risk is bleeding, including bleeding into the brain. It is uncommon, but it is the reason your medical team runs through a careful list of questions before giving it.
  • Almost everyone who receives the drug is still transferred afterwards. Dissolving the clot does not repair the narrowing underneath that caused it.

Part of my work as a Cardiologist takes me to Swan Hill, a town on the Murray River in Victoria, Australia. It is almost a five-hour drive from Melbourne, and I do that drive both ways. The hospital there is a good one, with excellent staff. What it does not have, and what most towns of its size anywhere in the world do not have, is a catheter laboratory: the room where a blocked heart artery can be reopened using a fine tube passed up from the wrist or groin.

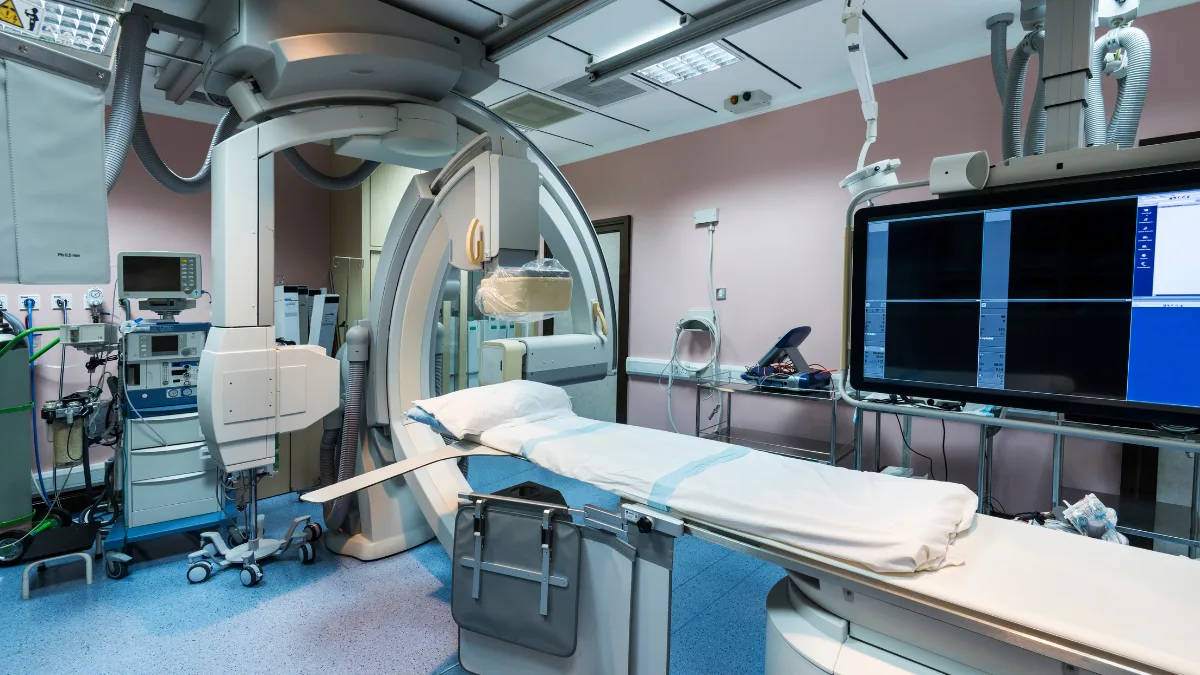
A cardiac catheter laboratory, empty between procedures
A cardiac catheter laboratory. The table sits at the centre, an X-ray camera moves around the patient on a large arm above it, and the screens show the arteries in real time as the cardiologist works. Rooms like this are the reason a heart attack is treated differently depending on where it happens.

So when someone arrives there in the middle of a heart attack, a conversation starts almost immediately between the local team, the retrieval service, and a cardiologist somewhere else. Patients can be flown rather than driven, and retrieval teams are quick and well practised. Even so, the transfer takes time, and heart muscle is at risk while it happens. Do we move this person, or treat them here and move them afterwards?

Millions of people live somewhere that conversation would need to happen. It is worth understanding how it is resolved, because the answer is more reassuring than most people expect.

What Is Actually Happening in a Heart Attack

The heart is a muscle, and like every muscle it needs its own blood supply. Three main arteries sit on its surface and feed it.

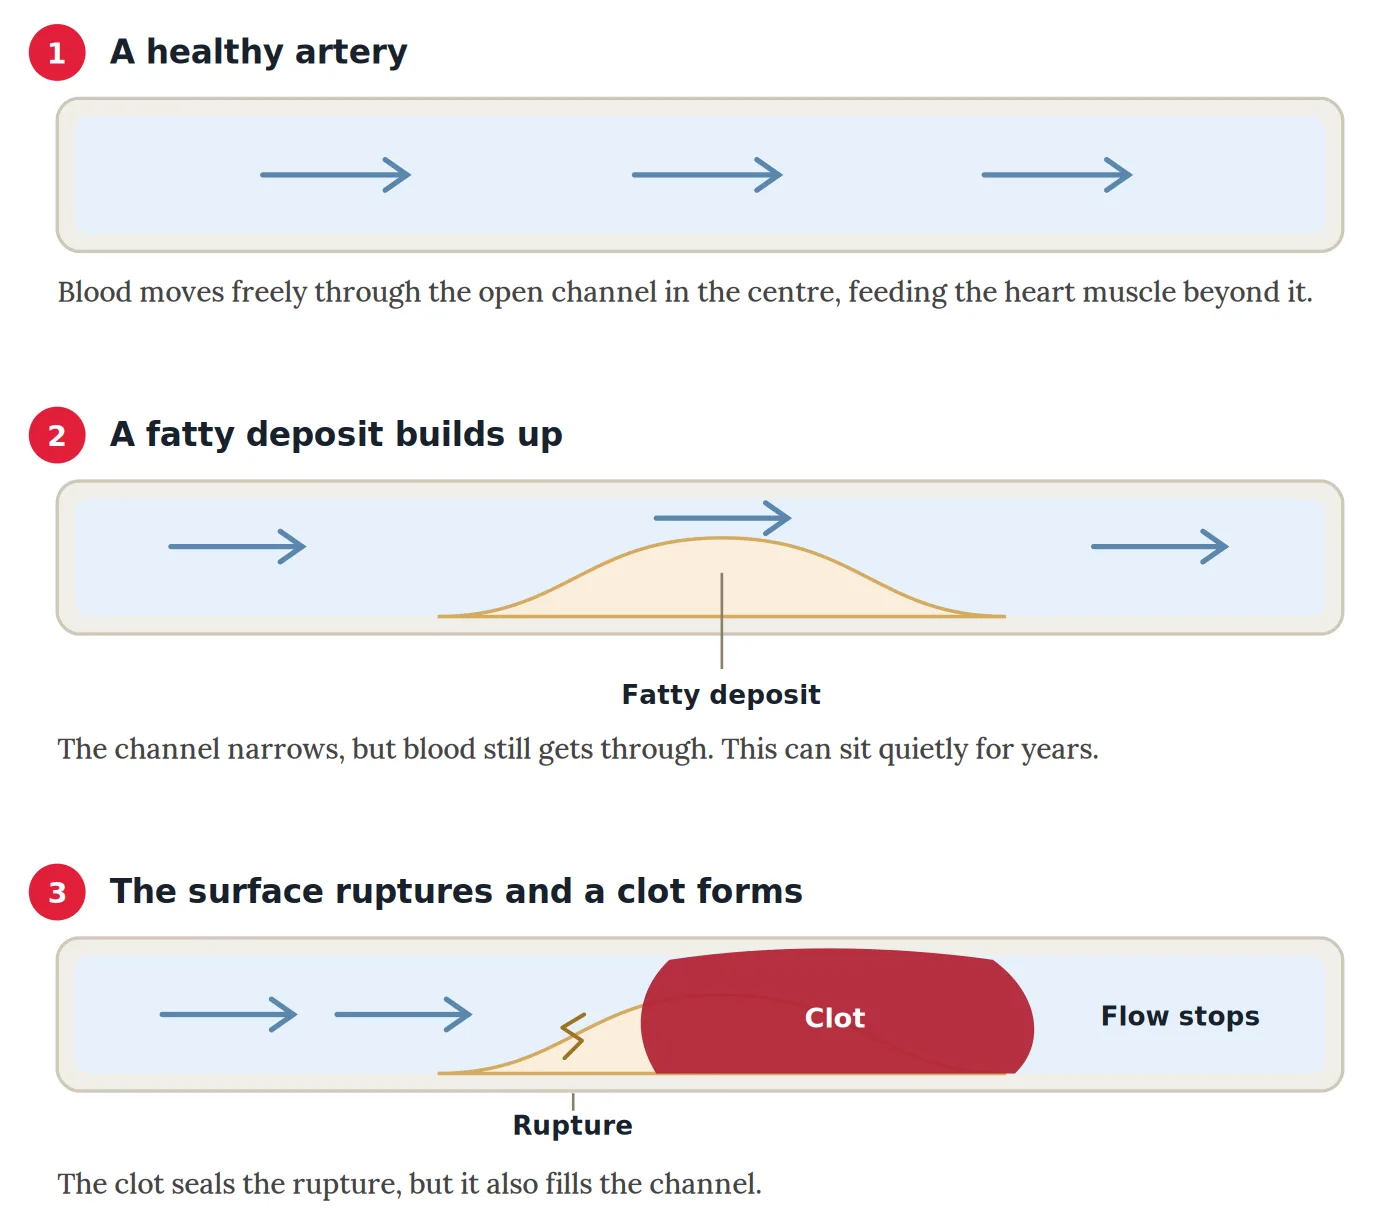
Over years, fatty deposits can build up in the wall of one of those arteries. Most of the time they sit there quietly. A heart attack begins when the surface of one of these deposits ruptures. Your body reacts the way it reacts to any injury, by forming a clot to seal it. If that clot fills the artery completely, blood stops flowing.

Three stage diagram: a healthy artery with blood flowing freely, an artery narrowed by a fatty deposit, and an artery blocked by a clot after the deposit ruptures
How a heart attack begins: a fatty deposit narrows the artery over years, then its surface ruptures and a clot forms over it, Heart Matters

Beyond the blockage, that stretch of muscle is cut off from its supply. How much of it comes through depends almost entirely on how quickly the artery is reopened. Restore the flow early and most of the muscle is preserved. Leave it several hours and less of it is. That is the whole reason for the urgency.

An ECG, the tracing taken from stickers on your chest, shows this pattern clearly within minutes. Doctors have a name for it, a STEMI, and you may see that word on your discharge letter. All it means is that an artery is completely blocked and the clock is running.

Two Ways to Open the Artery

The first way is mechanical. A cardiologist passes a fine tube from the wrist or groin up to the heart, finds the blockage, pushes a small balloon through it, and usually leaves a stent behind to hold it open. This is angioplasty. Where it can be done promptly, it is the better option.

The second way is chemical. A drug goes into a vein and dissolves the clot from the inside. These are the medicines most people know as clot-busters, and they require no special equipment, no cardiologist, and no operating theatre. They can be given in a small emergency department, in an ambulance, or in the back of an aircraft.

Which one a person receives is decided by the clock, not by the quality of the hospital they happen to be standing in.

Watch: a closer look at the stent itself, and how it holds an artery open, Heart Matters Educational Series

Where the Clot-Busting Drugs Came From

For most of the twentieth century, doctors believed the clot in a heart attack formed after the muscle died rather than causing it. Dissolving it therefore looked pointless. That view held into the 1970s.

When it was finally overturned, the first drug tested properly was streptokinase, made from a protein produced by bacteria. In 1986 an Italian study of nearly 12,000 patients found it cut deaths by around a fifth. Two years later, a second large study showed that streptokinase helped, that plain aspirin helped, and that giving both together helped considerably more than either alone.

I would put those two studies among the handful that genuinely changed cardiology. Before them, a heart attack was something you watched. Afterwards, it was something you could interrupt.

Newer drugs followed through the 1990s, tested in trials involving well over 100,000 people between them. The differences between the drugs turned out to be small. The lesson that mattered was something else entirely.

Forty years of research pointed at the same conclusion. Which drug is used matters far less than how quickly it reaches the patient.

Angioplasty later proved better than drug treatment wherever both were genuinely available, and it became the preferred approach. What it could not do was shorten the road from a country town. That is why the drugs never went away, and why they are still given every week in hospitals like the one I visit.

How the Drug Works

Your blood already carries the tools to dismantle a clot. It keeps them switched off until they are needed, which is sensible, since a permanently active clot-dissolving system would be dangerous.

These drugs simply switch that system on. They do not attack the clot directly. They activate your own machinery, which then breaks apart the mesh of protein strands holding the clot together, and the blockage crumbles.

The older drug, streptokinase, switched the system on everywhere in the body at once. It worked, but it thinned the blood generally and sometimes caused allergic reactions.

The newer drugs, alteplase, reteplase, and tenecteplase, are more targeted. They act mainly where a clot already exists, which makes them safer and more effective, and current guidelines recommend them over the older one.

Tenecteplase has become the most widely used, for a very practical reason. It is a single injection given over about five seconds, rather than a drip running for an hour. In a small hospital preparing to move a patient, or in a helicopter, that difference matters enormously.

The Two-Hour Rule

Guidelines around the world agree on the threshold, which is reassuring given how differently health systems are organised.

If a team can get the artery open with angioplasty within roughly two hours of the moment medical help first reaches the patient, that is the route taken. If they cannot, and the person is within 12 hours of their symptoms starting, and there is no specific reason to avoid it, the drug is given without waiting.

2 hours
If angioplasty cannot be reached within roughly this window, giving the clot-dissolving drug first is the better option.
European Society of Cardiology and comparable international guidelines

Once that decision is made, the aim is to have the drug running within 30 minutes of arrival, and sooner where possible. Some ambulance and retrieval services now give it before the patient reaches hospital at all.

The benefit is greatest in the first two or three hours after symptoms begin and fades steadily after that. Beyond about 12 hours there is little left to gain, and the balance shifts back towards transferring the person for angioplasty however far away it is.

What We Check Before Giving It

A clot-dissolving drug cannot tell the difference between a clot that is causing a heart attack and a clot somewhere else that is quietly doing something useful. That is the trade-off, and it is why this treatment carries a bleeding risk that angioplasty does not.

The serious concern is bleeding into the brain. It is uncommon, affecting somewhere around one in 100 people treated or fewer, but it can be devastating when it occurs. The risk is higher in older patients, in very small patients, and where blood pressure is high and not yet controlled.

So before giving it, the team works through a set of questions. Some answers rule the drug out completely. These include any previous bleed into the brain, a stroke caused by a blockage within the last six months, a known weakness or tumour in the brain’s blood vessels, major surgery or a serious head injury in the past month, bleeding from the stomach or bowel in the past month, a known bleeding disorder, or a suspected tear in the body’s main artery.

Other answers do not rule it out but change the balance. Advanced age, a recent fall, pregnancy, a stomach ulcer, or blood pressure that is very high all fall into this group, and they are weighed against how large the heart attack is and what the alternative would involve.

Where the drug genuinely cannot be given, the person is transferred for angioplasty no matter how long the journey takes. That decision gets made quickly, and it is one of the reasons the phone call happens early.

Bruising and minor bleeding around drip sites are common and rarely amount to anything.

Why the Journey Still Happens Afterwards

This part surprises people, and it is the single most useful thing to understand about the whole pathway.

The drug dissolves the clot. It does nothing at all to the fatty deposit underneath that ruptured in the first place. That deposit is still there, still narrowing the artery, and still capable of triggering another clot. Opening the artery buys time. It does not finish the job.

For that reason, guidelines say that essentially everyone who receives the drug should still be moved to a hospital with a catheter laboratory, even when the treatment has clearly worked.

1

The diagnosis

The ECG confirms a blocked artery. The team works out how long it would realistically take to reach a catheter laboratory, usually with the retrieval service already on the phone.

2

The treatment

If that journey would take more than about two hours, the drug is given, along with aspirin and other medicines that stop the clot reforming.

3

Checking it worked

Around an hour to 90 minutes later the ECG is repeated. If the pattern has settled substantially, the artery has almost certainly opened. Chest pain usually eases at the same time.

4

If it did not work

If the artery has stayed blocked, or the person becomes unwell, transfer happens straight away for urgent angioplasty rather than waiting.

5

The planned transfer

If it did work, transfer still happens, with a coronary angiogram usually done between two and 24 hours later, and a stent placed if one is needed.

That timing was not chosen arbitrarily. Going to the catheter laboratory immediately after the drug was tested and caused more bleeding without extra benefit. Waiting several days risked the artery closing again. Somewhere between a few hours and a day turned out to be the sweet spot.

The Part That Matters Most

Across every study ever done in this area, the factor with the biggest effect on how someone does has never been which drug they got or which hospital they reached.

It has been how long they waited before calling for help.

That gap is measured in hours in most countries. It is the only part of the whole sequence that happens before any doctor, nurse, or paramedic is involved, and it is the part most people underestimate. Someone with chest discomfort at 11pm who decides to see how they feel in the morning has already spent the window in which either treatment works best, whether they live next door to a major hospital or five hours from one.

Delay is longer still when the symptoms do not match the picture people carry in their heads. Women in particular are more likely to present with breathlessness, nausea, or exhaustion rather than crushing chest pain, and are more likely to wait, and to be waited on, as a result.

None of which is a failing on anyone’s part. Chest symptoms are frequently vague, they rarely arrive at a convenient moment, and not wanting to make a fuss is among the most human responses there is. It is worth knowing that ambulance services would far rather be called early and turn out to be unnecessary than be called too late.

⚠
When to Call for Emergency Help

Call your local emergency number straight away if any of these occur. Do not drive yourself, and do not wait to see whether it settles.

  1. Chest pain, pressure, tightness, or heaviness lasting more than 10 to 15 minutes.
  2. Discomfort spreading into the arm, jaw, neck, back, or upper stomach.
  3. Sudden breathlessness, a cold sweat, nausea, or feeling faint alongside any of the above.

Symptoms are often less obvious in women, in people with diabetes, and in older adults. Breathlessness or sudden overwhelming tiredness without any chest pain still warrants an emergency call. An ambulance crew can record an ECG on the spot, warn the hospital you are coming, and start treatment on the way, none of which happens if you drive.

Watch: what recovery after a heart attack usually involves, and the questions people most often have afterwards, Heart Matters Educational Series

Conclusion

Clot-busting treatment is not a lesser version of modern heart attack care. It is the treatment that created modern heart attack care, and in the right circumstances it remains the better of the two options rather than the fallback. A drug given at 40 minutes in a country hospital does more good than a flawless angioplasty four hours later.

What matters most is the early hours rather than the map. And if you are reading this because it has already happened, to you or to someone you love, the thing I would want you to take from it is that being treated a long way from a major centre does not mean you were given second best. I have written elsewhere about what recovery usually involves, and your own cardiologist can fill in what is specific to you. But whatever the past few weeks have looked like, the distance did not decide this, and that is worth holding onto.

Related Reading

Pericarditis: Chest Pain That’s Worse Lying Down

pericarditis
Key Points

  • Pericarditis is inflammation of the thin sac surrounding the heart. It is one of the more common causes of chest pain in younger people and, in most cases, one of the least dangerous.
  • The pain has a distinctive signature. It typically sharpens when lying flat and eases on sitting forward, which is unusual enough to be a useful clue.
  • In most cases no cause is ever found, or the illness follows an ordinary virus. Where tuberculosis is common, it is a leading cause and the picture differs. Where a specific cause does turn up, it changes both the outlook and the treatment.
  • Anti-inflammatory treatment combined with colchicine is standard first-line practice. In trial data, adding colchicine roughly halved the chance of the condition returning.
  • Recurrence is the most common complication, affecting somewhere between 15% and 30% of people after a first episode. Serious complications are uncommon. Where no underlying cause is found, fewer than 1 in 100 people go on to develop lasting stiffening of the sac.

The pain arrives sharply, usually behind the breastbone, and it behaves in a way that heart pain is not supposed to behave. Lying down makes it worse. Sitting up and leaning forward makes it better. Taking a deep breath can be enough to catch it.

That pattern sends many people to an emergency department convinced they are having a heart attack, and it is also why the diagnosis is often made quickly once someone describes it. Few cardiac symptoms are as positionally specific.

It tends to affect people younger than the typical coronary patient, and the outlook for most is good. What follows is what the condition actually is, why it happens, and what the evidence supports doing about it.

What the Pericardium Does

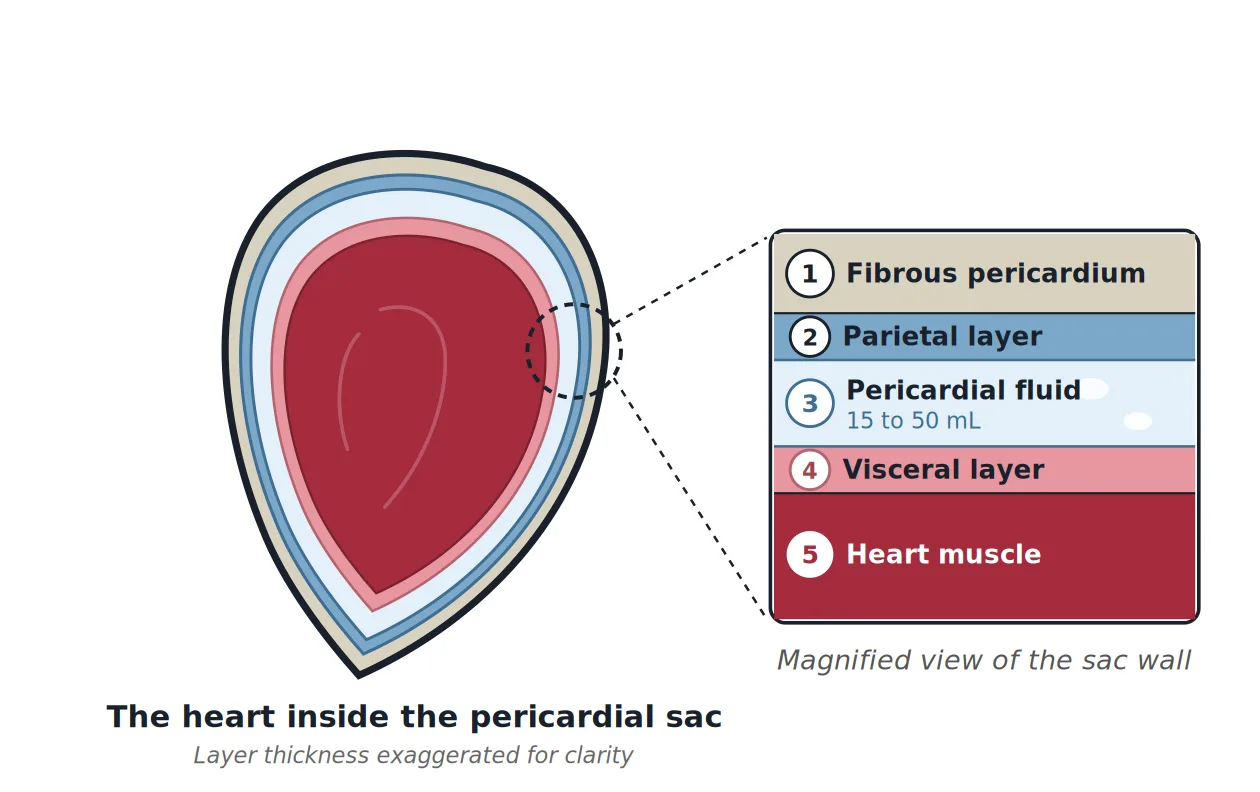
The heart sits inside a two-layered sac called the pericardium. Between the layers is a small amount of fluid, usually only 15 to 50 mL, which allows the heart to move smoothly against surrounding structures with every beat.

The sac anchors the heart, provides a barrier against infection spreading from the lungs, and stops the heart stretching too far. It is not essential to survival, and people who have had it surgically removed generally do well.

When it becomes inflamed, two things follow. The layers lose their smooth glide and rub against each other, which produces pain. Inflammation can also draw extra fluid into the space between the layers. Doctors call that a pericardial effusion, which simply means a build-up of fluid around the heart.

Cross-section of the heart showing the pericardium: the fibrous pericardium, parietal layer, pericardial fluid, visceral layer or epicardium, and the heart muscle beneath. Layer thickness is exaggerated for clarity.
The pericardium is a two-layered sac. Layer thickness is exaggerated in the drawing so each layer can be told apart; in reality the whole wall is only a couple of millimetres thick.
1

Fibrous pericardium, the outer layer. The tough outside of the sac. It anchors the heart in place and stops it stretching too far.

2

Parietal layer, the outer lining. The smooth inside surface of the outer sac.

3

Pericardial fluid. Normally only 15 to 50 mL, enough for the surfaces to glide. Inflammation can increase it, and the build-up is called an effusion.

4

Visceral layer, the inner lining. The same thin membrane as layer 2, folded back on itself and stuck to the heart’s own surface. Its medical name is the epicardium.

5

Heart muscle. Sits beneath the sac and is not affected in straightforward pericarditis. Doctors call it the myocardium.

What It Feels Like

The pain has a recognisable pattern

The pain is sharp rather than heavy, sits centrally behind the breastbone, and often radiates to the neck, the left shoulder, or the ridge of muscle running along the top of the shoulder. That last spot is unusual, and when it happens it is a fairly strong clue.

What sets it apart is how it responds to position and breathing. Lying flat brings the inflamed layers into closer contact and intensifies the pain. Sitting upright and leaning forward relieves it. Deep breaths, coughing, or swallowing often make it worse.

This is close to the opposite of the pain of a heart attack, which is typically a pressure or heaviness, unaffected by position, and frequently accompanied by sweating and nausea. The distinction is useful but not absolute, which is why chest pain of any kind is assessed rather than self-diagnosed.

Other symptoms

A low-grade fever is common, particularly where a viral illness preceded the episode. Fatigue, breathlessness, and a general sense of being unwell frequently accompany the pain, and symptoms tend to build over hours rather than striking instantaneously.

Watch: Prof. Peter Barlis on pericarditis, Heart Matters Educational Series

How the Diagnosis Is Made

European guidelines define acute pericarditis by the presence of at least two of four features: the characteristic chest pain, a particular sound heard through the stethoscope, specific changes on the heart tracing, and new or increasing fluid around the heart.

That sound has a name, a pericardial friction rub, and it is exactly what it sounds like: a scratching or creaking made by the inflamed layers rubbing together. Hearing it points strongly to the diagnosis. It comes and goes, though, so not hearing it rules nothing out.

No single test confirms it. The diagnosis is assembled from several, each answering a different question.

Test What it looks for In pericarditis
ECG The heart’s electrical signal Widespread, not one artery
Echocardiogram Fluid around the heart Effusion, filling affected
CRP Inflammation in the body Raised, tracks response
Troponin Damage to heart muscle Raised if muscle involved
Cardiac MRI Inflammation, seen directly Used when unclear

The ECG point is the one that separates pericarditis from a heart attack most reliably. Its changes are widespread rather than confined to the territory of a single artery. Troponin matters for a different reason. It is a protein released when heart muscle is damaged, so a raised level means the muscle is inflamed alongside the sac. That combination has its own name, myopericarditis, and it is watched more closely.

What Causes It

Most often, no cause is ever found

Where tuberculosis is uncommon, most cases fall into one of two groups: no cause found, or an ordinary virus assumed to be behind it. Doctors label the first group idiopathic, which is simply the medical word for cause unknown.

The two groups blur into each other. Many of the unexplained cases were almost certainly viral all along, with no test ever done to pin down which virus, largely because finding out rarely changes the treatment.

The viruses involved are everyday ones: the family behind common colds and stomach upsets, influenza, and the virus that causes glandular fever. A chest or stomach bug in the few weeks beforehand is a common part of the story.

That is why guidelines in low-tuberculosis regions do not push for exhaustive testing in every case: the search seldom finds anything and the usual causes settle on their own. Where tuberculosis rates are high, it becomes the leading cause of pericarditis and the approach changes completely.

COVID-19 and the vaccine question

This deserves a direct answer rather than a careful silence, because it is what many readers arrive looking for.

Both COVID-19 itself and the mRNA COVID vaccines have been linked to inflammation of the sac and of the heart muscle. Both associations are real. They differ substantially in magnitude.

Analyses of national reporting systems have estimated roughly six cases of heart or sac inflammation per million vaccine doses given, across all ages. Risk concentrates heavily in one group: young males, after the second dose, with estimates of around 12 to 13 cases per million doses in those aged 12 to 39. In adolescent studies, the risk after a second dose has been several times higher than after a first, and considerably higher in males than females. Most cases have been mild and settled with standard treatment.

Catching the virus carries the higher risk. A Hong Kong population study found this inflammation in roughly 326 per million people with confirmed COVID-19, against about 5.5 per million among those vaccinated, the latter being no different from the pre-pandemic background rate. A Spanish hospital study reported the same direction of effect, with the incidence following infection around 20 times that following mRNA vaccination. Cases attributed to infection also tended to be more severe.

Estimates vary between studies according to population, age structure, case definition, and how thoroughly cases were sought, so the precise figures should be read as an order of magnitude rather than a fixed number. The consistent finding across countries is the direction of the comparison. The risk is real on both sides, is counted in cases per million on both sides, and is higher after infection than after vaccination.

None of this makes an individual case less real or less unpleasant for the person experiencing it. Someone who develops pericarditis after a vaccine dose has a genuine condition requiring genuine treatment, and population-level reassurance is not an answer to an individual’s symptoms.

The causes at a glance

No cause found

Nothing is ever pinned down. This is the biggest single group, and it is also the one that settles most easily. Doctors call it idiopathic.

Viral illness

Everyday viruses: colds, stomach bugs, influenza, glandular fever. A chest or stomach illness in the previous few weeks is a common part of the story.

COVID and vaccination

Both infection and mRNA vaccination have been linked to it. Both are counted in cases per million, and the figure is higher after infection. See the section above.

Injury to the heart

After a heart attack, heart surgery, or a procedure done through a tube in an artery. The sac reacts to the injury nearby.

Autoimmune and systemic

Conditions where the immune system attacks the body’s own tissues, such as lupus and rheumatoid arthritis. Also kidney failure, some cancers, radiation treatment to the chest, and certain medicines.

Bacterial and tuberculous

Bacterial infection or tuberculosis. Far less frequent where tuberculosis rates are low, but wherever it occurs the outlook is considerably worse and lasting stiffening of the sac is far more likely.

How It Is Treated

Clinicians work through a fairly settled sequence. Most people never get past the first step of it.

Treatment Where it fits Typical duration
Aspirin or ibuprofen First choice, for the pain Until symptoms settle
Colchicine Added to the first choice 3 months, 6 if it returns
Steroid tablets Where the first two are unsuitable Reduced slowly
Anakinra, rilonacept Repeated relapses only Specialist supervision

Dose and duration are individual. Only the prescribing doctor, who knows the specific circumstances, can determine what is appropriate for a given person.

Two things in that table are worth expanding on.

Colchicine earns its place. The evidence is unusually strong for a condition this common. In the ICAP trial, people having a first episode were randomly given either colchicine or a dummy tablet alongside their usual treatment. The illness persisted or came back in 16.7% of those on colchicine, against 37.5% on the dummy tablet. Looking at return of symptoms alone, the figures were 9.2% against 20.8%. Stomach and bowel side effects were no more common than with the dummy tablet.

Steroids sit third for a reason. They work quickly, which makes their position in the list counter-intuitive. But steroids used during a first attack have been linked to a higher chance of the problem returning, so the medicine that settles things fastest can make the months afterwards harder. They are generally kept for people who cannot take the first two options, or where an immune condition is being treated, and only once infection has been ruled out.

Under 1% get a stiff sac

Where the cause is unknown or viral. The figure rises sharply where bacteria or tuberculosis are responsible.

15% to 30% recur

Recurrence is the most common complication after a first episode, and the figure is higher again without colchicine.

Colchicine halves recurrence

In the ICAP trial, the illness came back or persisted in 16.7% on colchicine, against 37.5% on a dummy tablet.

When It Comes Back

Recurrence is the most common complication and the most frustrating part of the condition. Between 15% and 30% of people experience a recurrence after a first episode, and among those who go on to have a first recurrence, the chance of a further one rises towards 50%.

A recurrence means a fresh episode after four to six weeks with no symptoms at all. The best explanation is that the immune system keeps the reaction running long after whatever set it off has gone. That is why medicines aimed at the immune signal itself work when they do.

The reassuring part, and it is worth stating plainly because people with repeated episodes often assume the opposite, is that recurrence does not signal accumulating damage. In groups of patients followed through repeated unexplained episodes, lasting stiffening of the sac has not been reported at all, and the overall risk in this group looks lower than after a single first episode.

The Complications That Matter

Two complications account for most of the concern.

Fluid squeezing the heart. If fluid gathers quickly enough, or in a large enough volume, it presses on the heart and stops it filling properly. The medical name is cardiac tamponade. It is rare where no cause is found, and much more common where cancer, tuberculosis or bacterial infection is behind the illness. Treatment is to drain the fluid.

A sac that turns stiff. Long-running inflammation can leave the sac thickened and rigid, so it grips the heart like a shell and limits every beat. The medical name is constrictive pericarditis. The risk is under 1% where the cause was unknown or viral, 2% to 5% for immune and cancer-related causes, and 20% to 30% where bacteria or tuberculosis were responsible.

Signs that warrant urgent medical attention include fainting, rapid or laboured breathing, severe or escalating breathlessness, or a sudden deterioration. These can be signs of fluid building up and squeezing the heart. Anyone experiencing them should seek emergency care immediately rather than waiting for a scheduled appointment.

Conclusion

Pericarditis is a condition where the alarming presentation and the actual outlook are poorly matched. The pain is genuinely severe, it mimics a heart attack closely enough to send people to hospital, and yet the great majority of cases settle with anti-inflammatory treatment and leave nothing behind.

Two things most influence how it goes: whether an underlying cause is identified, which changes the outlook substantially, and whether colchicine forms part of the initial treatment, which roughly halves the chance of it returning. For a diagnosis that so often arrives frightening, that is an encouraging picture.

Related Reading

When Blood Pressure Won’t Come Down: What Happens Next

Managing resistant hypertension — blood pressure monitoring and medication options explained by Prof. Peter Barlis

Blood pressure that stays high despite three or more medications has a name, and in most cases an explanation. What clinicians check first, why spironolactone is usually the fourth medicine added, and how narrow the role of renal denervation really is.

The Hair Loss Question

Hair loss and heart medicines
Key Points

  • Several medicines used in cardiology overlap with medicines used for hair, in both directions, which is why questions about hair loss often land with a cardiologist rather than a dermatologist.
  • Minoxidil, the treatment most people are asking about, began life as a blood pressure drug. The scalp solution rarely troubles the heart. The tablets retain a diluted version of the original effects.
  • Spironolactone, prescribed for heart failure and difficult blood pressure, also blocks the effects of male hormones. That is why it is used off-label for female pattern hair loss, and why some women notice a change in their hair while taking it.
  • The same hormonal effect makes spironolactone an unsuitable hair treatment for men, and this is the point most often missed.
  • Some hair loss is a signal rather than a cosmetic problem, including the shedding that commonly follows a heart attack, cardiac surgery, or any serious illness.

It is fair to wonder why a cardiologist is being asked about hair at all. The answer is that patients are increasingly being sent to ask.

Hair clinics and general practices now routinely tell people to check with their doctor about their heart before starting treatment, particularly minoxidil tablets. It arrives as a safety clearance rather than a cosmetic query, and it lands in a cardiology room because that is where it was sent.

There is a sound reason for that. Minoxidil was a blood pressure medicine long before it was a hair treatment, and it never entirely stopped being one. The overlap also runs the other way, because one of the medicines already sitting on many cardiac prescription lists is used by dermatologists for exactly this purpose.

Which is why the question, when it does come, is usually asked apologetically at the very end of the appointment, halfway out of the chair. It does not need to be. It is a question about medicines, and it belongs here.

Minoxidil, the One People Are Sent to Ask About

This is the treatment behind most of the clearance requests, and it has its own cardiovascular history.

It reached the market in the late 1970s as a treatment for severe hypertension. Patients taking it grew hair, and a topical formulation followed in the 1980s. Brand names differ from country to country, so the generic name minoxidil remains the reliable identifier on any packet, and available strengths vary by market.

Minoxidil opens potassium channels in the smooth muscle of small arteries. Those vessels relax and blood pressure falls. The body compensates by retaining salt and water and by raising the heart rate, which is why minoxidil tablets at blood pressure doses were almost always paired with a diuretic and a beta-blocker.

The scalp solution

Applied to intact scalp, only a small proportion of a topical dose reaches the bloodstream, far too little in most people to move blood pressure or heart rate measurably. Palpitations, lightheadedness, and mild ankle swelling have been described, but they are uncommon and tend to follow generous application, use over inflamed or broken skin, or unusual sensitivity to vasodilators.

Low-dose tablets

The bigger change over the past few years has been dermatologists prescribing minoxidil tablets at low doses, a small fraction of the intensity once used for hypertension. The largest published safety experience, a review of 1,404 patients across 10 centres in six countries, found side effects that were mostly mild. Hair growth in unwanted places was by far the most common, affecting about 15% of patients. Lightheadedness, fluid retention, and a faster heart rate each appeared in under 2%, and fewer than one in 50 people stopped treatment because of a side effect.

Hair in other places

The most frequently reported effect. Fine hair on the face, forearms, or upper back. It is not dangerous and it settles once the tablet is stopped.

Fluid retention

Salt and water retention is built into how the drug works. It shows up as puffy ankles or a small rise in weight, and it matters far more in a heart that is already struggling.

Heart rate and blood pressure

A slightly faster resting pulse and a small fall in blood pressure are both expected. People already taking several blood pressure medicines feel this more.

Where the frightening warnings came from

Anyone reading the product information for minoxidil tablets will find warnings about fluid collecting around the heart and about angina becoming worse. These are real, and they are also a product of their era, written from experience with high-dose treatment in patients who had severe hypertension, often alongside significant kidney disease, before modern blood pressure regimens existed. Pericardial effusion, meaning fluid in the sac surrounding the heart, was described in that setting and is identified on an echocardiogram.

At the doses used for hair, events of that severity appear to be rare rather than routine. Rare is not the same as impossible. The fair summary is that low-dose oral minoxidil has a reassuring short-term record in relatively healthy people, and a much thinner evidence base in those with established heart disease, because they are the patients least likely to have been studied.

Minoxidil at blood pressure doses also carries a rebound risk. Stopping abruptly removes the vasodilation while the compensating fluid retention and faster heart rate are still present, and blood pressure can overshoot. That is why the dose is usually stepped down rather than halted outright. Whether, when, and how to stop is a decision for the prescribing doctor, who may reasonably choose to stop immediately if a serious effect appears.

Feature Topical Low-Dose Oral
Brand names (vary by country) Several major brands Usually generic tablets
Reaches the bloodstream A small percentage Effectively all of it
Availability Over the counter in most markets Prescription, and off-label
Common nuisance effects Scalp irritation and itching Unwanted hair, puffy ankles
Cardiovascular relevance Low for most people Modest, worth reviewing
Dose strengths Vary by market Far below blood pressure doses

The situations that usually prompt a fuller review before oral minoxidil is considered are heart failure, known pericardial disease, significant valve disease, pulmonary hypertension, recent unstable angina, reduced kidney function, and a blood pressure regimen that is already crowded. In that last group, home blood pressure readings become genuinely useful information.

Spironolactone, the Medicine Already on the List

Spironolactone is a familiar name in cardiology. It is a mainstay of treatment in heart failure with reduced ejection fraction and one of the more useful options when blood pressure refuses to come down on three other agents.

Less widely known is that it does two things at once. Alongside its effect on salt and water handling, it blocks androgen receptors and reduces the production of male hormones. Androgens are central to pattern hair loss, which is why dermatologists reach for spironolactone in female pattern hair loss, acne, and polycystic ovary syndrome.

So a woman taking spironolactone for her heart who reports that her hair seems less thin is not imagining a mechanism. There is a plausible one, and it is the same mechanism a dermatologist would have been aiming for deliberately.

What the evidence actually supports

The evidence here is honest but modest. Most of it comes from observational series and clinical consensus rather than large randomised trials, and it points toward a partial effect that develops slowly, over many months, in some women rather than all of them. That is worth taking seriously. It is not a promise.

The doses are not the same

There is a further complication. The doses commonly used in dermatology sit above those used in heart failure, where treatment is deliberately conservative to protect kidney function and potassium levels.

Someone taking spironolactone for a cardiac reason is therefore receiving an amount that may or may not be doing much for their hair. A welcome side effect is a reasonable thing to enjoy. It is not a reason to start the drug, or to want more of it.

Why this is a different conversation for men

This is the point that gets lost fastest once the phrase “spironolactone helps hair” is in circulation.

Blocking androgens has consequences that men notice. Breast tenderness and breast tissue enlargement, known as gynaecomastia, are well recognised and become more likely at higher doses. Reduced libido is also reported. These are the reasons spironolactone is not used as a hair loss treatment in men.

Men already prescribed it for heart failure are a separate matter. There the cardiac benefit is substantial and well established, and the hormonal effects are managed as a known trade-off rather than pursued.

Potassium, and the combinations that matter

Spironolactone causes the body to retain potassium. That is intrinsic to how it works, and in most people it is handled without difficulty.

It becomes more delicate in combination. ACE inhibitors, angiotensin receptor blockers, sacubitril with valsartan, potassium supplements, and some anti-inflammatory painkillers all push potassium in the same direction, and reduced kidney function narrows the margin further. Blood tests before starting and at intervals afterwards are the standard way this is monitored, and they are the reason spironolactone is prescribed rather than borrowed from a relative’s cabinet.

Spironolactone is also avoided in pregnancy, because an antiandrogen affects a developing baby.

Finasteride and dutasteride, the other treatments raised most often, work on hormone conversion rather than on blood vessels. No consistent cardiovascular signal has emerged from the trial data, and the discussions around them concern sexual side effects and mood rather than the heart.

The GLP-1 Question

A study published in The BMJ in July 2026 looked at this directly. Researchers followed adults with type 2 diabetes starting a GLP-1 receptor agonist and compared them with people starting two other classes of glucose-lowering medicine. Newly recorded hair loss was more common in the GLP-1 group, by roughly 40% to 70% depending on the comparison.

Three things temper that. The absolute numbers were small, at around seven cases per 1,000 people a year against four to five in the comparison groups. The excess was concentrated in non-scarring hair loss, the diffuse and usually reversible kind linked to rapid weight change. And a study built on diagnoses recorded during routine care cannot fully separate an effect of the drug from an effect of losing weight quickly.

The study was done in one large health system and in people with diabetes, so it does not settle the question for everyone taking these medicines. It matters here because semaglutide and related medicines are now prescribed for cardiovascular reasons and not only metabolic ones. An effect on hair that is usually reversible sits on a very different scale from a reduction in heart attacks and strokes.

When Hair Loss Is a Signal Rather Than a Complaint

Not all hair loss is pattern baldness, and some of it points back toward the heart. A heart attack, cardiac surgery, or any major physiological stress can push a large proportion of hair follicles into their resting phase at once. The shedding arrives two to four months later, by which time most people have stopped connecting the two events.

Growing

Most follicles.
Lasts years.

Resting

A small minority.
Root pulls upward.

Shedding

Follicle empties,
then restarts.

Resting to shedding takes two to four months

A shock to the body pushes many follicles into the resting phase together, so they shed as a group months after the event.

Iron deficiency and thyroid disease belong in the same category. Both cause hair loss, both are common in people with heart disease, and both are treatable once found.

Questions Patients Ask Me Most

These are the ones that come up again and again in clinic, answered as plainly as I can. As always, this is general information, and any decision about your own medicines belongs in a conversation with your doctor.

Can I use the scalp solution if I have a heart condition?

Mostly reassuring

For most people with stable heart disease, topical minoxidil is not the thing a cardiologist is concerned about. Very little of it reaches the bloodstream through intact scalp. It is still worth mentioning at your next appointment, particularly if you have heart failure or your blood pressure is being actively adjusted.

I am already on spironolactone. Will it help my hair?

Worth discussing

It might, if you are a woman with pattern hair loss, and some women do notice a change. The effect is partial, gradual, and not universal, and the doses used in dermatology usually sit above cardiac doses. It is a welcome bonus if it happens, rather than something to count on or to ask for more of.

If it works for women, can a man take it for hair?

Worth discussing

Spironolactone is not used as a hair treatment in men. The same hormone blocking that helps some women causes breast tenderness and breast tissue enlargement in men, and reduced libido is also reported. Men taking spironolactone for heart failure are in a different situation, where the cardiac benefit is the point.

My hair started falling out after my heart attack. Is it the medication?

Mostly reassuring

Usually not. Shedding that begins two to four months after a heart attack, cardiac surgery, or a serious illness is far more often telogen effluvium, the body’s delayed response to the stress itself. It is diffuse rather than patchy and it recovers on its own in most cases. Iron levels and thyroid function are worth checking.

Should I stop my weight loss injection if my hair thins?

Worth discussing

That is a conversation to have rather than a decision to make alone. The hair loss described with these medicines is the reversible kind and the absolute risk is small, while the cardiovascular benefit for people who qualify is substantial. Stopping a medicine prescribed to reduce heart attacks and strokes is not a step to take over hair without advice.

Is there anything worth checking before I try something?

Mostly reassuring

Iron studies and thyroid function are the two most commonly useful tests, because both cause hair loss, both are common in people with heart disease, and both are treatable. Kidney function and potassium matter if spironolactone is being considered. These are simple blood tests rather than anything elaborate.

Heart Matters Resource

When in Doubt, Get Checked Out

New swelling, unexplained weight gain, or a racing pulse after starting any new medicine are worth reviewing properly rather than waiting to see whether they settle.

Read: When in Doubt, Get Checked Out →

Conclusion

Hair and the heart share more pharmacology than either specialty tends to advertise. One widely used cardiac medicine has a genuine effect on hair in women and a set of reasons not to use it that way in men. The best known hair treatment was a blood pressure drug first and never entirely stopped being one.

So when a hair clinic or a GP sends someone to have their heart checked before starting treatment, that is a sensible instruction rather than a formality. For most people the answer will be straightforward. Knowing which people it is not straightforward for is the reason the question is worth asking at all.

Related Reading