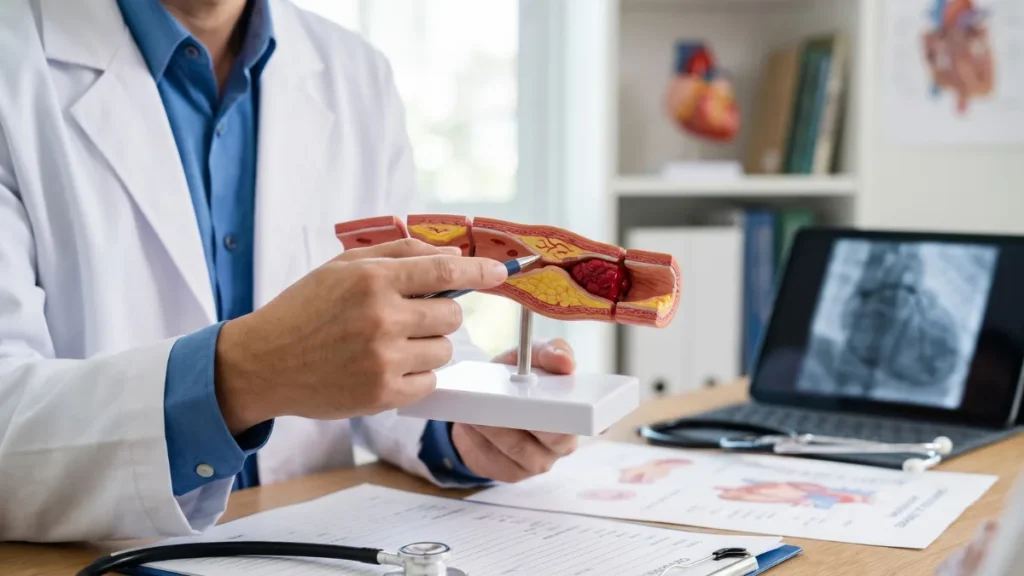



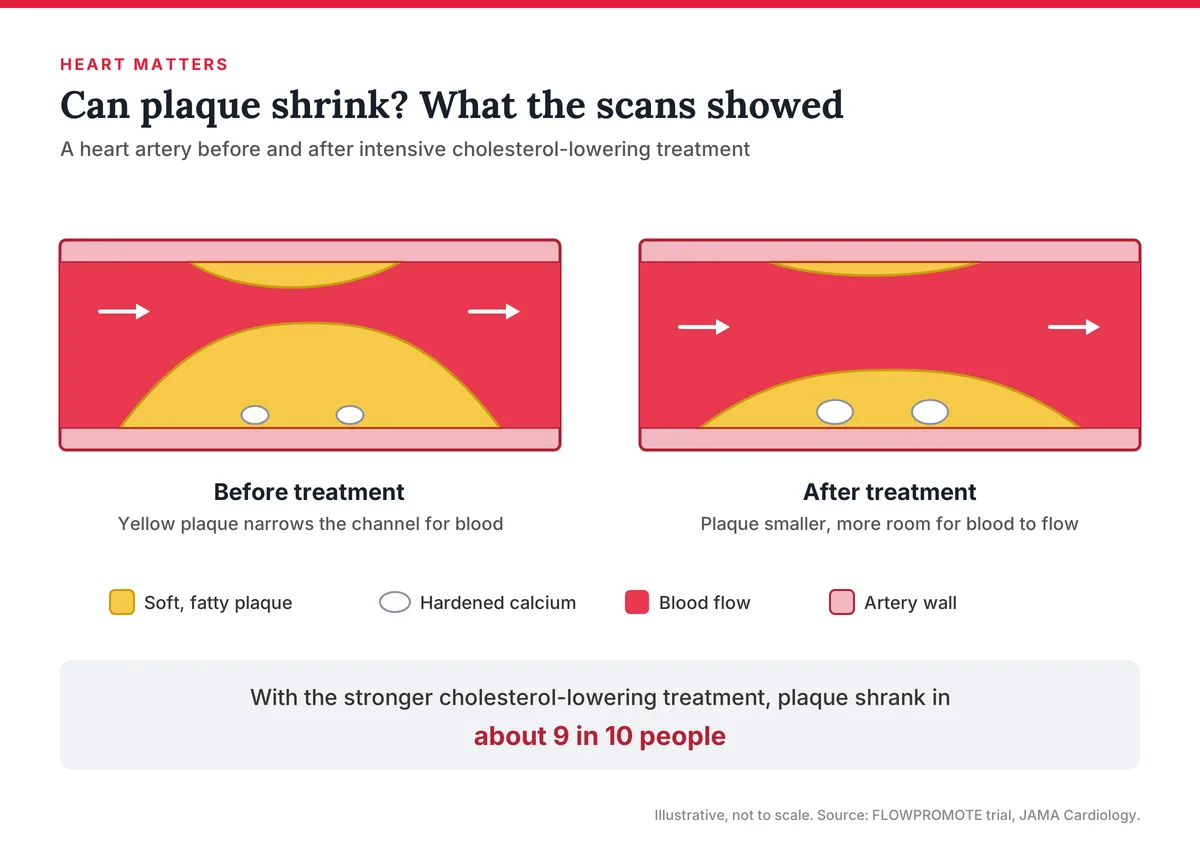
- Plaque in the heart arteries is not necessarily permanent. A study using CT scans found that lowering LDL cholesterol was followed by plaque shrinking in most people.
- The more cholesterol came down, the more the plaque tended to shrink. The soft, fatty part of the plaque changed the most.
- The findings fit with earlier imaging research, and with the wider evidence that statins do more than lower cholesterol. They also help calm and stabilise plaque in the artery wall.
- This matters most for people who have already had a heart attack, a stent, a stroke, or bypass surgery, where the aim of treatment is to prevent a repeat event.
- Concerns about statins are understandable. Side effects are real for some people, and there are usually options when a particular medicine does not suit.
Being told there is plaque in a heart artery can feel like being handed a verdict. One of the most common questions in a cardiology consultation follows straight after: is this permanent, or can anything be done about it?
It is a fair question, and the answer is more encouraging than many people expect. A study published in JAMA Cardiology adds to the evidence that plaque can not only be slowed, but in many people partly reversed.
What the Study Found
Researchers in Denmark followed 104 people who had newly been found to have narrowings in their heart arteries, a condition called atherosclerosis. None had been on long-term cholesterol treatment before.
Everyone was started on cholesterol-lowering medicine, and people were placed at random into one of two groups.
Group 1
Atorvastatin
A widely used statin, at a high dose
Cholesterol
Came down well
Plaque shrank in
About 3 in 4 people
Group 2
Rosuvastatin plus ezetimibe
A more potent statin at a high dose, with a second cholesterol-lowering tablet
Cholesterol
Came down further
Plaque shrank in
About 9 in 10 people
The aim was not to find out which statin is better. The two treatments were chosen to bring cholesterol down by different amounts, so the researchers could see whether lowering it further made a difference to the plaque. Detailed CT scans of the heart arteries were repeated over 18 months to find out.
The results were striking. Plaque shrank in most people in both groups, but more so with rosuvastatin and ezetimibe together. Across everyone, it shrank more in those whose LDL cholesterol, the “bad” cholesterol that builds plaque, came down the furthest.
How the two medicines work
Cholesterol reaches the blood by two main routes. Most is made by the liver, and the rest is absorbed from the gut. The two medicines in this study each work on a different route.
Statins: less made by the liver
Statins slow the liver’s own production of cholesterol. In response, the liver draws more LDL cholesterol out of the blood. Atorvastatin and rosuvastatin both work this way.
Ezetimibe: less absorbed from the gut
Ezetimibe reduces how much cholesterol is taken up from food and digestive juices in the gut. Less reaches the liver, which again pulls more LDL out of the blood.
Because they work in different places, a statin and ezetimibe together lower cholesterol further than a statin alone. Ezetimibe is a small daily tablet and is generally well tolerated, which is why it is a common partner to a statin when more lowering is needed.
Confirming What Earlier Research Showed
This is not the first time plaque has been seen to shrink. Earlier studies, mostly using a tiny ultrasound camera passed inside the artery, found the same pattern with statin treatment.
What this study adds is a wider view. CT scanning allowed the researchers to look along the length of all the main heart arteries, rather than one short section. The shrinking was seen across the whole picture.
It also fits with a long-held view among cardiologists: statins do more than lower a number on a blood test. Research suggests they also settle the low-grade inflammation inside the artery wall and help turn soft, unsettled plaque into firmer, more stable plaque.
Lowers LDL cholesterol
Less cholesterol reaches the artery wall, so less is available to build plaque.
Calms inflammation
Statins appear to quieten the inflammation that makes plaque active and unsettled.
Stabilises plaque
Plaque tends to become firmer and less likely to break open, which is what triggers most heart attacks.
Shrinks soft plaque
In many people, the soft, fatty part of the plaque gets smaller over time.
One finding can sound worrying at first. The small, hardened areas of calcium in the plaque grew in both groups. This is generally understood as part of plaque settling down under treatment, and it is explained further in our article on statins and calcium in the arteries.
Why This Matters Most After a Heart Event
The people in this study had not had a heart attack. Yet the people who often benefit most from this kind of treatment are those who already have: people recovering after a heart attack, those who have had a stent or bypass surgery, and those who have had a stroke caused by narrowed arteries.
A stent or bypass fixes the narrowing that caused the trouble. It does not treat the plaque elsewhere in the arteries, and that plaque is where a future event is most likely to start. This is why medication remains part of care after any procedure, and why a stent or bypass is one part of treatment rather than the whole of it.
After an event, the goal is clear: to reduce the chance of it happening again. Large trials involving many thousands of people have shown that lowering LDL cholesterol does exactly that. Studies like this one help show what may be happening inside the artery while that protection builds.
Plaque is not always a one-way street. With the right treatment, it can be slowed, steadied, and in many people partly reversed.
Understanding the Worry About Statins
Many people feel uneasy about statins. They may have read alarming stories, had a friend who felt unwell on one, or would rather not take a tablet for life. These concerns are understandable and deserve a proper conversation.
It is also fair to say that some people are started on a statin without a thorough look at their individual risk. For someone at low risk, the decision is genuinely finely balanced and worth talking through.
After a heart attack, stent, stroke, or bypass, the balance is very different. The benefit of lowering cholesterol in this group is among the best established in all of medicine.
Side effects are real for some people, most often muscle aches. Large studies comparing statins with dummy tablets have found that many aches occur at similar rates on both, but some people are genuinely affected. In this study, a number of participants had their treatment adjusted, and only 2 of the 104 stopped their statin completely.
When a statin does not suit, there are usually other routes. Clinicians commonly try a different statin or dose, or add or switch to other medicines such as ezetimibe or an injectable PCSK9 treatment.
Stopping a statin after a heart event removes its protective effect on the plaque, and cholesterol levels rise again within weeks. That is why changes are usually made by adjusting or swapping treatment rather than stopping altogether. Whether and how to change a statin is a decision for the prescribing doctor.
What Else Can Change
Medication is where the clearest evidence for shrinking plaque lies. Other changes are strongly linked to whether plaque goes on to cause a heart attack or stroke:
- Not smoking, which is among the most powerful changes available.
- Keeping blood pressure at a healthy level.
- Regular physical activity, including walking.
- A heart-healthy eating pattern, such as a Mediterranean-style diet.
- Good blood sugar control for people with diabetes.
None of this needs to happen at once. Most people find it more realistic to start with one or two changes and build from there. Cardiac rehabilitation programs, offered to many people after a heart event, are a well-supported place to start.
What This Study Does Not Tell Us
This was a small study, and it measured plaque on scans rather than counting heart attacks or strokes. Most participants were men, and all were starting treatment for the first time. The results may differ for people who have been on a statin for years.
Even so, the direction of the findings matches what larger studies have shown over many years. Lower cholesterol, sustained over time, means healthier arteries and fewer repeat events.
Conclusion
Plaque in a heart artery is an important finding, but it is not necessarily a fixed one. This study adds to the evidence that lowering cholesterol can shrink and settle plaque, and that statins do more for the artery than a blood test alone can show.
For anyone who has had a heart attack, stent, stroke, or bypass, that is a reason for genuine hope. Questions or worries about statins are worth discussing with your cardiologist, who can tailor treatment to suit the individual.
Related Reading
- Coronary Artery Disease
- The Coronary Calcium Score: What It Measures and What to Expect
- Angina: What It Is, What It Feels Like, and How It’s Treated
- Understanding Your Cardiovascular Risk Factors
- Lipoprotein(a): The Inherited Heart Risk Most People Have Never Heard Of
- The Timing of Cholesterol-Lowering Medications: Does Nighttime Dosing Make a Difference?
- Dietary Fibre and Your Heart: Why This Nutrient Deserves More Attention