The Pulse Newsletter Expert heart health, in plain English. Fortnightly, from our clinicians. Subscribe →

Aortic Dissection: The Chest Pain That Cannot Wait

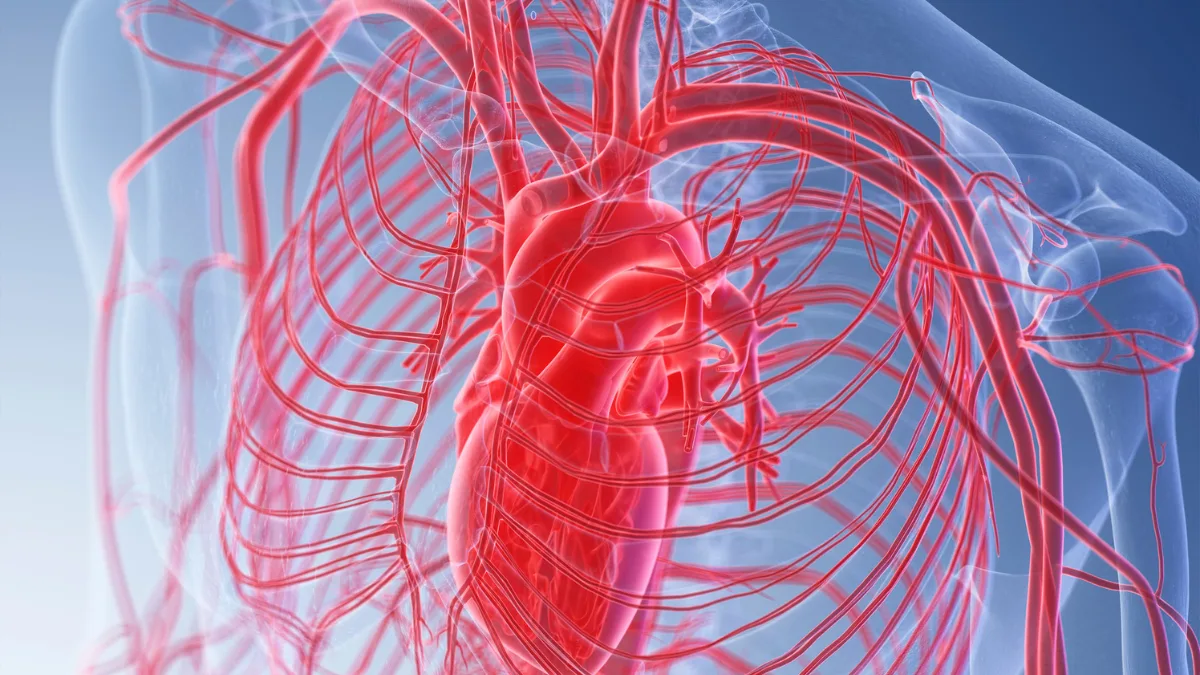
aortic dissection
Key Points

  • An aortic dissection is a tear in the wall of the aorta, the body’s main artery. It is a medical emergency, and every minute counts.
  • The warning sign is sudden, severe chest or back pain, often described as ripping or tearing, and often the worst pain a person has ever felt. It arrives at full intensity within seconds rather than building gradually.
  • Long term high blood pressure is the single biggest risk factor. Most people who have a dissection have had raised blood pressure for years.
  • Inherited conditions such as Marfan syndrome, and a family history of aortic aneurysm or unexplained sudden death, substantially increase risk and are a reason to ask about screening.
  • Dissection is easily mistaken for other conditions, and a normal ECG or normal blood test does not rule it out. If the pain fits the pattern, call 000.

Most cardiac emergencies announce themselves gradually. A heaviness in the chest that builds over minutes. A tightness that comes on with exertion and eases with rest. An aortic dissection does not behave this way. It arrives at full force, without warning, in people who felt perfectly well moments earlier.

It is the emergency that gives no notice. A person is well in the morning, well over lunch, and in cardiac arrest by the evening. That pattern is not a rare exception to how dissection behaves. It is characteristic of it.

Understanding what an aortic dissection is, who is at risk, and above all what it feels like, is the difference between a call to emergency services and a fatal delay.

What Is an Aortic Dissection?

The aorta is the largest blood vessel in the body. It leaves the heart, arches over the top of it, and travels down through the chest and abdomen, carrying every drop of blood the heart pumps out to the rest of the body. It is roughly the width of a garden hose, and it withstands enormous pressure with every heartbeat.

The wall of the aorta is made of three layers, bonded together. A dissection begins when the innermost layer develops a tear. Blood, travelling at high pressure, is forced into that tear and begins to push the layers apart, carving a false channel along the length of the vessel.

Once that channel opens, several things can go badly wrong at once. The false channel can compress the true one, starving organs of blood. It can extend into the branches that supply the brain, kidneys, or the heart muscle itself. It can rupture entirely. And if the tear is close to the heart, blood can leak into the sac that surrounds it, squeezing the heart until it can no longer pump.

The Two Types, and Why the Difference Matters

Doctors classify dissections by where the tear sits. This is not academic. The two types are treated in fundamentally different ways.

Type A dissections involve the ascending aorta, the section closest to the heart. These are surgical emergencies. The tear can extend backwards into the sac around the heart or shear off the arteries feeding the heart muscle, and either can cause sudden cardiac arrest. Type A dissections are taken directly to theatre.

Type B dissections are confined to the descending aorta, further down the chest. These are often managed initially with aggressive blood pressure control in intensive care, with a stent placed inside the vessel in selected cases. Surgery is not always the first step.

Type A

The tear involves the section of aorta nearest the heart. This is the more dangerous form and is treated as an immediate surgical emergency.

Type B

The tear is confined to the descending aorta, further from the heart. Often managed first with intensive blood pressure control, and sometimes a stent.

Why Time Matters

For an untreated Type A dissection, the risk of death rises with every hour that passes after the tear. This is why it is never something to wait out.

What It Actually Feels Like

This is the section worth remembering, because recognising the pain is what gets people to hospital in time.

The classic symptom is sudden, severe pain in the chest or back. Patients describe it as ripping, tearing, or being stabbed. It is frequently described as the worst pain of their life. Two features set it apart from most other chest pain.

First, the onset. It does not build. It is maximal within seconds. People can often tell you exactly what they were doing at the moment it began.

Second, it can move. As the tear extends along the vessel, the pain can travel, migrating from the front of the chest through to between the shoulder blades, or down into the abdomen.

Dissection can also present in ways that look like something else entirely. Stroke-like symptoms if the tear reaches the arteries to the brain. Abdominal pain. Fainting. A leg that suddenly turns cold and pale. In the most severe cases, the first sign is collapse. This was the pattern in the widely reported death of United States Senator Lindsey Graham in July 2026, whose office cited preliminary findings of an aortic dissection due to arteriosclerotic cardiovascular disease. He was 71, had recently returned from an overseas trip, and had shown no sign of being unwell.

Chest pain that arrives at full intensity in an instant, and is described as tearing or ripping, is not a wait and see symptom. It is a call an ambulance symptom.

Why Blood Pressure Sits at the Centre of This

The most important thing to understand about dissection is that in the majority of cases, it is the endpoint of a process that has been building quietly for years.

Every heartbeat sends a pulse of pressure through the aortic wall. Over decades, persistently high blood pressure stresses that wall, stiffening it and degrading the elastic tissue that holds the layers together. Add the plaque and inflammation of atherosclerosis, the same disease process that drives most heart attacks and strokes, and the wall becomes progressively less able to tolerate the pressure it is subjected to.

Chronic hypertension is the single biggest modifiable risk factor for aortic dissection, and it is present in the large majority of cases. This is the uncomfortable but hopeful part of the story. A condition that kills within minutes is driven, more than anything else, by a number that can be measured at home in 60 seconds and treated effectively.

The other well-recognised contributors are:

  • Age and sex. Dissection most commonly affects men in their 60s and 70s, though it can occur far younger, particularly where there is an inherited cause.
  • Smoking. Tobacco accelerates the arterial damage that weakens the aortic wall.
  • An existing aortic aneurysm. A vessel that has already enlarged is a vessel more likely to tear.
  • Stimulant drug use. Cocaine and amphetamines cause abrupt, extreme blood pressure surges.
  • Pregnancy. Uncommon, but a recognised period of increased risk in women with underlying aortic disease.

The Genetic Side, and When Family History Matters

Not every dissection is a story about decades of blood pressure. A meaningful minority occur in younger people whose aortas were structurally vulnerable from birth.

Inherited connective tissue conditions

Marfan syndrome is the best known. It affects the connective tissue that gives the aortic wall its strength, and people with Marfan syndrome can experience dissection in their 30s or 40s. Loeys-Dietz syndrome and vascular Ehlers-Danlos syndrome carry similar risk. These conditions often, though not always, come with recognisable physical features such as tall stature, long limbs and fingers, and problems with the lens of the eye.

Bicuspid aortic valve

Some people are born with an aortic valve that has two leaflets instead of the usual three. This is one of the most common congenital heart differences, and it is associated with weakness in the wall of the ascending aorta, independent of any valve problem. It is also relevant to aortic stenosis later in life.

Familial aortic disease with no syndrome attached

This is the group most often missed. Some families carry a tendency to aortic aneurysm and dissection without any of the classical syndromes and without any outward clues. The only signal is the family history itself.

If a parent, sibling, or child has had an aortic aneurysm, an aortic dissection, or an unexplained sudden death, that is worth raising with your doctor. Imaging can measure the size of the aorta long before it is in danger, and an aorta that is enlarging can be monitored, treated with blood pressure medication, and repaired electively. Elective repair is a very different proposition to emergency surgery on a tearing vessel.

Why It Is So Easily Missed

Aortic dissection is one of medicine’s great imitators, and this is worth understanding because it affects what you should do.

The standard tests used to assess chest pain, an ECG and a blood test for cardiac enzymes, can be entirely normal while the aorta is tearing. A chest X-ray is often unremarkable. The diagnosis usually rests on a CT scan of the aorta, and that scan only gets ordered if someone thinks to order it.

This has two practical implications. If you experience sudden tearing chest or back pain, say so in exactly those words to the paramedics and to the doctor in the emergency department. The description matters. And if you have a family history of aortic disease, say that too, unprompted. It changes how the pain in front of the doctor is interpreted.

It is entirely reasonable, in that situation, to ask directly whether an aortic dissection has been considered. Good clinicians will not be offended by the question.

What You Can Actually Do

The measures that protect the aorta are not exotic. They are the same measures that protect the rest of the cardiovascular system, applied consistently over years.

Know your blood pressure and treat it. If you have been prescribed medication for it, take it. This matters more than any other single action, and there is a great deal you can do alongside medication to help bring the numbers down.

Do not smoke. Treat raised cholesterol. Stay physically active. Understand your overall cardiovascular risk profile rather than any single number in isolation.

And know the alarm symptom. Sudden, severe, tearing chest or back pain, arriving at full intensity, in a person who was well moments before, is an emergency until proven otherwise. In Australia, call 000. Do not drive yourself. Do not wait to see whether it settles.

Conclusion

An aortic dissection is one of the few conditions in cardiovascular medicine where outcome is measured in minutes rather than hours or days. It is also, for most people, the final chapter of a much longer and much quieter story, one written by years of untreated blood pressure and arterial damage. That is the part that is within reach.

Take the blood pressure reading. Ask about the family history. And if the pain ever comes, sudden and tearing and unlike anything before it, do not talk yourself out of the phone call.

Related Reading

Demystifying Heart Failure: HFrEF, HFpEF and HFimpEF Explained

heartmatters.com 2026 04 01T171429.222
Key Points

  • Heart failure does not mean the heart has stopped or is about to. It means the heart is not pumping or filling as efficiently as it should, and in many cases this can be treated and even improved.
  • The confusing letters (HFrEF, HFpEF, and the newer HFimpEF) all describe one thing: the ejection fraction, or how much blood the main pumping chamber squeezes out with each beat.
  • Cardiologists separate these types because the underlying problem and the best treatment differ. The same label points the whole team toward the right medicines.
  • HFimpEF (improved ejection fraction) is the hopeful category. It describes people whose heart function has recovered, and the key lesson is that the medicines usually need to continue.
  • A new international consensus, the Second Universal Definition of Heart Failure published in June 2026, reframes heart failure as a condition that can change over time, with more focus on catching it early.

You have been told you have heart failure, and within the same conversation you have heard HFrEF, HFpEF, and perhaps HFimpEF. It sounds like alphabet soup, and it arrives at exactly the moment you are least equipped to decode it. The good news is that these terms are far less frightening once you understand what they are actually measuring, and why your cardiologist cares about the difference.

This article breaks the language down into plain English: what heart failure really means, what those letters stand for, why the distinction matters for your treatment, and what a major new international definition, published in June 2026, changes for patients.

Start With What Heart Failure Actually Means

The name is one of the cruellest in medicine. “Failure” suggests something has stopped, or is about to. That is not what it means. Heart failure is a clinical syndrome in which the heart cannot pump or fill with blood as efficiently as the body needs, usually producing symptoms such as breathlessness, fatigue, and swelling in the legs and ankles.

Crucially, it is not a single disease and it is not a death sentence. It is a description of how the heart is performing, and modern treatment can stabilise it, ease symptoms, and in a meaningful number of people improve the heart’s function substantially. To understand the categories, you first need to understand one number.

The Number Behind the Letters: Ejection Fraction

Every time the heart’s main pumping chamber, the left ventricle, contracts, it squeezes a percentage of the blood inside it out to the body. That percentage is the ejection fraction, usually shortened to EF. It is measured most often on an echocardiogram, the heart ultrasound.

A normal left ventricle does not empty completely. A healthy EF sits somewhere around 55% to 70%. So an EF of 60% is normal, not a sign that 40% is being left behind in a worrying way. This is the single most misread number in a cardiology report, so it is worth pausing on: a lower EF means the pump is weaker, but the EF is only one part of the picture, and it is not the whole story of how you will feel or fare.

The Three Main Types, Explained

Heart failure is grouped by ejection fraction because that number, more than almost anything else, tells the cardiologist what kind of problem they are dealing with and which treatments are likely to help. Here are the categories you are most likely to hear.

HFrEF: heart failure with reduced ejection fraction

This is the “weak pump” type. The EF is reduced, conventionally 40% or below, meaning the left ventricle is not contracting forcefully enough. The heart muscle has usually been damaged or weakened, and the squeeze is impaired. HFrEF is the type with the largest body of evidence behind its treatment, and, importantly, the type where the right combination of medicines can make the biggest difference.

HFpEF: heart failure with preserved ejection fraction

Here the EF is preserved, conventionally 50% or above, so the pump looks normal on paper. The problem is not the squeeze but the relaxation and filling. A stiff left ventricle cannot relax properly between beats, so it fills poorly and pressure backs up, producing the same symptoms of breathlessness and swelling. HFpEF is more common in older adults, in women, and in people with long-standing high blood pressure, diabetes, or obesity. For years it was the harder type to treat, though that has changed recently.

HFimpEF: heart failure with improved ejection fraction

This is the newest and most hopeful category. It describes someone who started with a reduced EF (40% or below) and, with treatment, has seen it recover to above 40%. Their heart has improved. The vital message attached to this label, and the reason cardiologists coined it rather than simply calling the person “better,” is that the improvement is usually because of the medicines, not instead of them. Stopping treatment because the numbers look good is one of the most common ways people relapse.

You may also hear HFmrEF, heart failure with mildly reduced ejection fraction, describing the middle band where EF sits between 41% and 49%. Think of it as the territory between the reduced and preserved categories, treated with a foot in both camps.

HFrEF: reduced

The pump is weak. Ejection fraction 40% or below. The muscle is not squeezing hard enough. Strong evidence exists for treatment that helps the heart recover.

HFpEF: preserved

The pump looks normal (EF 50% or above) but the ventricle is stiff and fills poorly. More common with age, in women, and with high blood pressure or diabetes.

HFimpEF: improved

Started reduced, now recovered above 40%. The good-news category, with one rule: the medicines that produced the recovery usually need to continue.

Why Cardiologists Bother Splitting Hairs

It is a fair question. If the symptoms are similar, why label the types at all? The answer is that the underlying mechanics are genuinely different, and so is the treatment that works. A medicine proven to save lives in a weak, reduced-EF heart may do little for a stiff, preserved-EF heart, and vice versa. The category is not bureaucratic tidiness. It is the shorthand that points your whole care team toward the treatments most likely to help you, and away from ones that will not.

Getting the category right also shapes what your cardiologist watches over time, from your BNP blood test to repeat scans that track whether your EF is holding steady, worsening, or improving.

The table below sets the three types side by side. It is a map, not a diagnosis, and your own cardiologist remains the person who reads it onto your particular heart.

Feature HFrEF (reduced) HFpEF (preserved) HFimpEF (improved)
Ejection fraction 40% or below 50% or above Was 40% or below, now above 40%
Core problem A weak squeeze A stiff chamber that fills poorly A previously weak heart that has recovered
More common in People with prior muscle damage or a weakened heart Older adults, women, and people with high blood pressure or diabetes People treated early and effectively for HFrEF
Treatment focus The four pillars of medicine, built up together Treating the drivers, plus SGLT2 inhibitors Continuing the medicines that produced the recovery
Outlook message Strong evidence that treatment helps Improving fast as new evidence arrives The hopeful category, if treatment continues

The label is not there to frighten you. It is there to make sure the right medicine reaches the right heart.

What Causes Each Type

The causes overlap, but they cluster differently across the categories, and identifying the cause is often as important as measuring the EF.

Reduced-EF heart failure most often follows damage to the heart muscle: a previous heart attack that has left a weakened area, longstanding uncontrolled blood pressure, disease of the heart muscle itself (the cardiomyopathies), heart rhythm problems such as atrial fibrillation, valve disease, or, in some people, alcohol and certain toxins.

Preserved-EF heart failure tends to grow out of years of a heart working against stiffening and pressure: chronic high blood pressure, diabetes, obesity, obstructive sleep apnoea, and ageing itself. Less commonly, an infiltrative condition such as cardiac amyloidosis stiffens the muscle, which matters because some of these causes now have specific treatments.

Improved-EF heart failure, by definition, starts as the reduced type and gets better, usually because the cause was treatable and the treatment worked. That is precisely why the medicines are rarely a temporary measure.

How Each Type Is Treated

This is where the categories earn their keep. The following is a general map, not a prescription. The right combination, and every dose, is individual, and only your own cardiologist can advise what is right for you.

For reduced-EF heart failure, the modern approach uses four classes of medicine together, often called the four pillars or quadruple therapy. In broad terms these are a medicine that relaxes and protects the blood vessels and heart (an ACE inhibitor, an ARB, or the combination agent Entresto), a beta-blocker, a mineralocorticoid receptor antagonist such as spironolactone, and an SGLT2 inhibitor. Used together and built up carefully, this combination has transformed outcomes over the past decade.

For preserved-EF heart failure, the picture has brightened considerably. SGLT2 inhibitors now have good evidence here too, which was not the case a few years ago. Beyond that, the priority is treating the drivers: controlling blood pressure and diabetes, managing weight, addressing sleep apnoea, and using diuretics to clear the fluid that causes congestion and breathlessness. Treating the specific cause, where there is one, matters more in this group than in any other.

For improved-EF heart failure, the treatment is, in most cases, to keep going. Trials have shown that stopping the medicines once the heart has recovered often allows the weakness to return. The recovery is best understood as the treatment succeeding, not as the illness disappearing, and the safest path is to maintain the therapy under your cardiologist’s guidance. Never stop a heart failure medicine without speaking to them first.

What the New 2026 Definition Changes

In June 2026, the world’s leading cardiovascular bodies, including the American Heart Association, the American College of Cardiology, the European Society of Cardiology, and the World Heart Federation, published the Second Universal Definition of Heart Failure, simultaneously in the journals JACC, Circulation, the European Heart Journal, and Global Heart. The American Heart Association has also released a plain-language summary for patients. It updates the first such definition from 2021, and although the document is written for clinicians, several of its changes matter to patients.

64 million
adults worldwide are estimated to live with heart failure, a number driven up by ageing populations and rising rates of high blood pressure, diabetes, and obesity.
American Heart Association, June 2026

First, it moves away from rigid cut-off numbers for ejection fraction and acknowledges that a normal EF differs by sex, age, and ethnicity, while keeping the familiar reduced, preserved, and improved categories as practical guides. Second, it puts far greater emphasis on catching heart failure early, before symptoms appear, so that prevention and treatment can start sooner. Third, and perhaps most reassuringly, it formally describes heart failure as a dynamic condition that can improve, go into remission, or progress, rather than a fixed, one-way diagnosis. The document is intended to be the foundation for the next major heart failure guideline, expected in 2027.

For a patient, the takeaway is encouraging: the field increasingly sees heart failure not as a static verdict but as a condition to be caught early, categorised accurately, and, in many people, improved.

Questions Worth Asking at Your Next Appointment

  • Which type of heart failure do I have, and what does that mean for my treatment?
  • What is my ejection fraction, and has it changed since my last echocardiogram?
  • Am I on the right combination of medicines for my specific type?
  • Are there conditions contributing to my heart failure, such as blood pressure, diabetes, or weight, that we should be managing more closely?
  • What symptoms should prompt me to contact the team between appointments?

Heart Matters Resource

When in Doubt, Get Checked Out

New breathlessness, unusual tiredness, or swelling in the legs are worth having assessed early. Heart failure is far more treatable when it is picked up sooner rather than later.

Read: When in Doubt, Get Checked Out →

Conclusion

The terminology around heart failure sounds far more alarming than the reality for most people. HFrEF, HFpEF, and HFimpEF are simply three ways of describing how well the heart’s main chamber is pumping and filling, and each points toward a different and increasingly effective set of treatments. The letters are a tool for getting you the right care, not a measure of how worried you should be.

If you have been given one of these labels, the most useful thing you can do is understand which type you have, take the medicines as prescribed even if you feel well, and keep the conversation with your cardiologist going. Heart failure is more treatable today than at any point in medical history, and, as the newest category reminds us, it can genuinely improve.

Related Reading

CoQ10 and Your Heart: What the Evidence Actually Shows

heartmatters.com 51

CoQ10 is a widely used supplement, especially among people on statins, but the evidence is more mixed than the marketing suggests. Here is what it can and can’t do, who might benefit, and the interactions that matter if you are on a blood thinner.

Vascepa and Vazkepa: What This Prescription Omega-3 Actually Does

Vascepa Vazkepa
Key Points

  • Vascepa and Vazkepa are two brand names for the same prescription medication, icosapent ethyl, a highly purified form of the omega-3 fatty acid EPA. The medication is sold as Vascepa in the United States and as Vazkepa across Europe, the United Kingdom, Australia and other markets. Neither is the same as an over-the-counter fish oil supplement.
  • It is prescribed as an add-on for people already taking a statin who have raised triglycerides and are at high risk of a heart attack or stroke. It is not a replacement for a statin.
  • The REDUCE-IT trial found it reduced the risk of serious cardiovascular events by 25% in this group, a result that changed guidelines in several countries.
  • The dose is two 998 mg capsules twice daily, four capsules a day in total, always taken with a meal. Food is essential for proper absorption.
  • The two side effects to know about are a small increased risk of atrial fibrillation and an increased tendency to bleed. Tell your doctor and pharmacist about every other medication you take. Never stop without speaking to your cardiologist first.

For many years, cardiologists recommended fish oil capsules to patients with high triglycerides, and the evidence was modest at best. Then in 2018 a major clinical trial changed the conversation.

The REDUCE-IT trial reported that a specific prescription omega-3 medication reduced the risk of heart attack, stroke, and cardiovascular death in high-risk patients already on statin therapy. The results prompted cardiologists to rethink how they managed this group. This article explains what the medication is, who it is for, how it works, and what to expect if you have been prescribed it.

What Are Vascepa and Vazkepa?

Vascepa and Vazkepa are two brand names for the same medication, icosapent ethyl, a highly purified, prescription-strength form of EPA, one of the omega-3 fatty acids found in oily fish. It was first approved in the United States, where the REDUCE-IT trial was run, and is sold there as Vascepa. In Europe, the United Kingdom, Australia and a number of other markets it is sold as Vazkepa. The active ingredient and the dose are identical, so everything in this article applies equally to both.

What makes this medication different from a standard fish oil supplement is that it contains only EPA, with no DHA, and it is manufactured to a far higher standard of purity. That distinction matters clinically, and we will come back to it in the comparison section below.

How Does It Work?

The medication lowers blood triglycerides, a type of fat that circulates in the bloodstream. At the full prescribed dose it typically reduces triglycerides by around 20 to 30%. The cardiovascular benefit seen in REDUCE-IT was larger than triglyceride lowering alone could explain, and researchers believe several additional mechanisms are involved.

Lowers triglycerides

Reduces this blood fat by about 20 to 30% at the full prescribed dose.

Reduces inflammation

EPA enters blood vessel walls, where it may cool the chronic inflammation that drives arterial plaque.

Stabilises plaque

May make existing fatty deposits more stable and less likely to rupture, the event that triggers most heart attacks.

Reduces platelet stickiness

Platelets are the cells that clump to form clots. Making them less sticky may reduce the risk of a dangerous blockage.

The precise contribution of each pathway is still being studied. You can read more about how inflammation drives heart disease in a separate article.

Who Is It Prescribed For?

This medication is not for everyone. It is mainly used to lower heart risk in people who are already taking a statin but still have raised triglycerides, and who are at high risk because they have already had heart trouble or have diabetes alongside other risk factors. In some countries it is also used to bring down very high triglyceride levels. It is taken alongside a statin, not instead of one.

The exact rules for who can be prescribed it differ from one country to another, and they change over time. So the only reliable answer to “is this right for me?” comes from your own doctor, who can weigh it against your personal situation. Always check with your cardiologist or GP before assuming it does or does not apply to you.

This is not a fish oil capsule from the supermarket. It is a purified, prescription medicine with trial evidence behind it, for a specific group of high-risk patients already on a statin.

Prof. Peter Barlis, Interventional Cardiologist

The REDUCE-IT Trial

The evidence behind this medication comes largely from one landmark clinical trial.

8,179
Patients across 11 countries
4.9
Years average follow-up
25%
Reduction in serious heart events vs placebo
2018
Published in the New England Journal of Medicine

All participants were on stable statin therapy with raised triglycerides. Roughly 70% had already had cardiovascular disease, while the rest had diabetes and additional risk factors. They were randomly assigned to receive either icosapent ethyl or a placebo, a dummy capsule with no active ingredient.

The result was a 25% reduction in serious heart events, a group that included heart attacks, strokes, cardiovascular deaths, and hospital admissions for severe chest pain. Put another way, several fewer people in every hundred had a serious heart event over about five years. In a population already at elevated risk, that is a meaningful difference.

25%
lower risk of serious cardiovascular events in high-risk patients on statin therapy, a result that prompted guideline updates in several countries.
REDUCE-IT trial, New England Journal of Medicine, 2018

How to Take It

The approved dose is two 998 mg capsules twice daily, four capsules a day in total, taken with meals. Food is not optional here. The medication is far better absorbed when taken with food, so the capsules should always be swallowed whole with or just after a meal, never crushed or chewed.

Morning
2 x 998 mg capsules
Take with your morning meal. Swallow whole. Do not crush or chew.
Evening
2 x 998 mg capsules
Take with your evening meal. Storing capsules in the fridge can reduce any fishy aftertaste.

This is a long-term medication whose benefits accumulate over time. If you miss a dose, take your next one as normal with your next meal, and do not double up. The dose and duration are individual, and only your cardiologist can advise what is right for you. Never stop taking it without speaking to your cardiologist first.

Side Effects to Know About

The medication is generally well tolerated, and most people take it without significant problems. Two effects deserve specific attention.

Atrial fibrillation

REDUCE-IT found a small increase in atrial fibrillation, the most common abnormal heart rhythm. The absolute increase was modest. Worth discussing with your cardiologist if you have a history of AF or palpitations.

Increased bleeding tendency

It reduces platelet stickiness, which can increase the tendency to bleed. In the trial, bleeding events were modestly more common than with placebo (around 12% versus 10%), and the risk was greater in people also taking blood-thinning medications such as aspirin, clopidogrel, or warfarin. Tell your doctor and pharmacist about every medication you take.

Other reported effects include constipation, swelling of the hands, feet, or legs, joint or muscle pain, gout, and a fishy aftertaste. Serious reactions are uncommon. Because this is a relatively new medicine, it remains under additional safety monitoring in many countries, and any side effects can be reported to your doctor or your national medicines regulator.

How It Differs From Standard Fish Oil

Many patients ask whether this is just an expensive fish oil capsule. It is not, and the difference is clinically important.

Vascepa / Vazkepa (prescription) Standard fish oil (over the counter)
Active ingredient EPA only, highly purified Mix of EPA and DHA, typically 30 to 40% omega-3
Manufacturing standard Pharmaceutical grade Supplement grade
Contains DHA No Yes
Effect on LDL cholesterol Neutral to slightly favourable DHA may raise LDL slightly
Cardiovascular trial evidence REDUCE-IT: 25% fewer serious heart events No comparable outcome data
Suitable for vegetarians No, fish-derived EPA and capsule shell Most are not, check labelling

The absence of DHA is deliberate. DHA may raise LDL cholesterol slightly, potentially offsetting some of the benefit, which may be part of why this medication performed differently from standard fish oil in trials. It is worth being clear about one practical point: because both the EPA and the capsule shell are fish-derived, the medication is not suitable for vegetarians, vegans, or people who avoid fish products for religious or cultural reasons, and there is currently no approved vegetarian alternative with the same evidence. If this applies to you, raise it with your cardiologist rather than simply stopping.

Cost and Availability

Because this is a prescription medication rather than a supplement, how much you pay depends heavily on where you live and how your healthcare system works. In some countries it is subsidised through a national scheme or covered by insurance for patients who meet specific criteria, which can reduce the cost substantially. In others it is paid for privately and can be expensive. Approval status and the exact eligibility rules also differ from country to country, and they change over time. The reliable approach is to ask your cardiologist or pharmacist about availability, eligibility, and cost where you live, rather than relying on a figure you read online.

Common Questions

Can I replace my statin with it? No. It works alongside a statin, not instead of one, and all the trial evidence comes from patients already on statin therapy.

Will it show up on a blood test? Yes. Your triglyceride level will fall, and your cardiologist will likely recheck your lipids a few months after starting to confirm it is working as expected.

How long until it works? The triglyceride-lowering effect appears within weeks, but the cardiovascular benefit builds over years of consistent use. This is a medicine for the long term, not a short course.

Heart Matters Resource

When in Doubt, Get Checked Out

If you have raised triglycerides and established heart risk, whether a medication like this fits your care is a conversation worth having. Your cardiologist can weigh it against the rest of your treatment plan.

Read: When in Doubt, Get Checked Out →

Conclusion

For a specific group of patients, those already on a statin with raised triglycerides and significant heart risk, the REDUCE-IT evidence shows that icosapent ethyl, whether dispensed as Vascepa or Vazkepa, can reduce the chance of a serious cardiovascular event. It is not a treatment for everyone, and it is not a substitute for the rest of your care.

If you have been prescribed it, take it consistently with meals, keep your pharmacist informed about all your other medications, and attend your regular blood test appointments. That is what gives this medication the best chance of working well for you.

And if you have read this wondering whether it might help you, the most useful next step is simply to ask. Whether this medication is suitable for you depends on your own health, your other medicines, and your level of risk, and only a doctor who knows your history can make that call. Always check with your cardiologist or GP before starting, stopping, or changing any treatment.

Related Reading

ApoB Explained: What It Measures and Why LDL Still Matters

apoB
Key Points

  • ApoB is a single protein that sits on the surface of every cholesterol particle capable of causing plaque, so an apoB result is effectively a headcount of all the particles that can harm your arteries.
  • A standard LDL cholesterol result measures the cholesterol carried inside your particles, not how many particles there are. Most of the time the two agree, but in some people they do not.
  • When LDL cholesterol looks reassuring but apoB is high, this mismatch (called discordance) can reveal hidden risk that a routine cholesterol panel misses.
  • Strong evidence supports apoB as an accurate marker of cardiovascular risk, particularly in people with high triglycerides, type 2 diabetes, or metabolic syndrome.
  • ApoB does not replace your LDL, triglycerides, or lipoprotein(a) results. Each tells you something the others cannot, and the best assessment uses them together.
  • No single number captures your risk. Heart disease is multifactorial, so blood pressure, diabetes, smoking, weight, and family history all matter alongside your lipids. Investigations such as a calcium score add another layer, and whether to add apoB is a conversation worth having with your cardiologist.

There is a lively and sometimes heated debate online about cholesterol. One vocal group argues that the LDL cholesterol number most of us have measured for decades is almost beside the point, and that a different number, apolipoprotein B, or apoB, is the one that truly predicts heart disease. If you have come across this argument and felt unsure who to believe, you are not alone.

The truth, as is so often the case in medicine, sits between the two extremes. ApoB is a genuinely valuable measurement, and the science behind it is sound. It is also not a magic number that makes everything else obsolete. This article explains what apoB actually is, why it can outperform a standard cholesterol result, and how to think about whether it belongs in your own blood tests.

What Is ApoB, Exactly?

To understand apoB, it helps to picture how cholesterol travels through your blood. Cholesterol is a fatty substance, and fat does not dissolve in water. So your body packages cholesterol inside tiny spherical particles that can move through the bloodstream. The particles that drive atherosclerosis, the gradual furring of the arteries, include LDL (low density lipoprotein) and a few close relatives.

Here is the key fact. Every one of these harmful particles carries exactly one molecule of a protein called apolipoprotein B on its surface. One particle, one apoB. This includes LDL, VLDL, IDL, and even lipoprotein(a). So when a laboratory measures your apoB level, it is effectively counting the total number of particles in your blood that are capable of lodging in your artery wall and forming plaque.

Why Counting Particles Can Beat Measuring Cholesterol

A standard lipid panel reports your LDL cholesterol, which sounds like it should tell you everything. But LDL cholesterol measures the amount of cholesterol carried inside your LDL particles. It does not measure how many particles you have.

This distinction matters because particles vary in size. Some people carry a smaller number of large, cholesterol-rich particles. Others carry a large number of small, cholesterol-poor particles. Two people can have an identical LDL cholesterol result while one has far more circulating particles than the other. Since it is the particles themselves that burrow into the artery wall, the person with more particles carries more risk, even though their cholesterol number looks the same.

A useful way to picture it: imagine traffic on a motorway. LDL cholesterol tells you the total weight of cargo being carried. ApoB tells you how many vehicles are on the road. If your arteries are the road, it is the number of vehicles, not the total cargo, that determines how often something collides with the wall.

One protein per particle

Every harmful cholesterol particle carries a single apoB protein, so your apoB level counts every particle that can cause plaque.

Cargo versus headcount

LDL cholesterol measures the cargo carried inside particles. ApoB counts the particles themselves, which is what damages the artery wall.

Why the gap matters

When particle count is high but cholesterol per particle is low, your LDL result can look fine while your true risk is not.

The family of particles apoB counts

ApoB does not just count LDL. It tags several related particles, each of which can contribute to plaque. This is part of why a single apoB result can be so informative: it captures the whole atherogenic family in one number.

LDL

Low density lipoprotein. The most familiar and most numerous of the harmful particles, and the main driver of plaque in most people.

VLDL and IDL

Larger, triglyceride-rich particles and their remnants. They become more important when triglycerides are high.

Lipoprotein(a)

An LDL-like particle with an extra protein attached. Largely inherited, and counted within apoB but not separately identified by it.

Each of these carries one apoB protein, so they are all captured in your total. What apoB cannot do is tell you the breakdown. It will not reveal, for instance, whether a high count is driven by ordinary LDL or by an inherited excess of Lp(a). That is one reason the individual tests retain their value, a point we return to below.

When LDL Cholesterol and ApoB Disagree

Most of the time, your LDL cholesterol and your apoB tell the same story. When both are high, or both are low, doctors call this concordance, and a standard cholesterol panel serves you perfectly well.

The interesting and clinically important situations are the mismatches, known as discordance. This is when your LDL cholesterol looks acceptable but your apoB is high, signalling many small particles quietly carrying on their work. In this scenario, a reassuring cholesterol result can give false comfort. A large 2024 review of 15 studies involving nearly 600,000 people found that apoB was a more accurate marker of risk than LDL cholesterol in every discordance study examined.

Who is most likely to be discordant

You are more likely to have a meaningful gap between your LDL cholesterol and your apoB if you have any of the following: high triglycerides, type 2 diabetes, metabolic syndrome, central weight gain around the abdomen, or a pattern of small dense LDL particles. People in these groups can have a deceptively normal LDL cholesterol while their particle count, and their risk, runs higher. This is precisely the group in which apoB adds the most.

What the Evidence Actually Shows

The case for apoB is strong, and it is worth being clear about what the research does and does not say.

On the supportive side, apoB has performed consistently well as a predictor of heart attack and stroke, often edging out both LDL cholesterol and non-HDL cholesterol, particularly in people whose results are discordant. Because it counts particles directly, it is less affected by the variations in particle size that can distort a standard cholesterol reading. For people with diabetes or high triglycerides, this advantage is most pronounced.

On the cautious side, this does not mean LDL cholesterol is worthless. Far from it. Lowering LDL cholesterol remains the single most trial-tested intervention in all of preventive cardiology. Decades of randomised trials, including the trials that established statins and newer agents such as PCSK9 inhibitors, were built on LDL cholesterol as the target, and the benefit of lowering it is beyond dispute. The online voices declaring LDL cholesterol irrelevant overstate the case considerably.

Why LDL, Triglycerides, and Lp(a) Still Matter

The enthusiasm for apoB has, in some corners of the internet, tipped into dismissing the numbers we have relied on for years. That is a mistake. Each of the established measurements tells you something apoB alone does not, and a good lipid assessment uses them together.

LDL cholesterol

LDL cholesterol is not a flawed or outdated number. It is the most thoroughly validated treatment target in cardiology, and every major guideline still places it at the centre of care. The reason is simple: when we lower LDL cholesterol in clinical trials, heart attacks and strokes fall in proportion, reliably and repeatedly. ApoB refines how we interpret LDL cholesterol in certain people. It does not unseat it. If you are tracking one number over time to see whether your treatment is working, LDL cholesterol remains an entirely sensible choice.

Triglycerides

Triglycerides are a separate and valuable piece of the puzzle. A raised triglyceride level is one of the clearest signals that your LDL cholesterol and apoB may be discordant, because high triglycerides tend to accompany the small, dense, numerous particles that apoB picks up. Triglycerides also respond strongly to lifestyle, which makes them a useful and motivating number to watch. Diet matters here, and the evidence supporting the Mediterranean diet and omega-3 fats is particularly relevant for people with elevated triglycerides.

Lipoprotein(a)

Lipoprotein(a), or Lp(a), deserves its own place on the test request entirely. It is largely inherited, it changes very little over a lifetime, and a single measurement tells you whether you carry this extra, independent layer of risk. While apoB does count Lp(a) particles among its total, it cannot tell you how much of your risk comes specifically from Lp(a), which is why a dedicated Lp(a) test remains worthwhile in its own right. For many people this is a once-in-a-lifetime measurement that meaningfully changes how aggressively their other risk factors should be managed.

What Does a Statin Do to Your ApoB?

This is a question worth answering directly, because it is one of the most useful things to understand about apoB in practice. Statins lower apoB substantially, typically by somewhere in the range of a quarter to nearly half, broadly in step with how much they lower LDL cholesterol. Adding ezetimibe or a PCSK9 inhibitor brings it down further still. So if you are already on treatment, your apoB is very likely already falling alongside your other numbers.

There is one important exception, and it is the reason apoB does not make the individual tests redundant. Statins do very little to lipoprotein(a). Someone can take a statin, watch their LDL cholesterol and apoB fall nicely, and still carry a high inherited Lp(a) that the treatment has barely touched. This is exactly why measuring Lp(a) at least once, separately, remains worthwhile even for people whose apoB looks well controlled.

ApoB Is One Piece of a Multifactorial Picture

Perhaps the most important point in this whole discussion is the one the online debate tends to forget. Cardiovascular disease is multifactorial. No single number, however good, captures your risk on its own, and apoB is no exception.

Your overall risk is shaped by a web of factors that interact with one another. These include your blood pressure, whether you have type 2 diabetes or features of metabolic syndrome, whether you smoke, your weight and waist measurement, your family history, your level of inflammation, and your age. A person with a perfect apoB but uncontrolled blood pressure and a smoking habit is not low risk. Conversely, a moderately raised apoB carries very different weight in an otherwise healthy 45-year-old than in someone with diabetes and a strong family history.

This is why fixating on any one marker, apoB included, can be misleading. The most useful approach is the one your cardiologist actually uses: weighing your lipids alongside every other modifiable factor. Two of the most powerful of those, smoking and high blood pressure, are entirely separate from your cholesterol particles and yet enormously important. You can read a fuller account in our overview of cardiovascular risk factors.

The Role of Investigations

Blood markers tell you about risk. Imaging can tell you what is actually happening in your arteries, and the two together are far more informative than either alone.

The coronary calcium score is the investigation patients most often ask about, and it can be confusing, so it is worth being clear. A calcium score does not measure your cholesterol or your particle count. It measures calcified plaque that has already formed in your coronary arteries, giving a direct picture of the disease itself rather than the risk factors driving it. A high score can prompt more intensive treatment even when your blood results look reasonable. Our article on what a high calcium score really means explains how to interpret the number.

One genuine source of confusion deserves a mention. Because statins can convert soft plaque into denser, calcified plaque, people on a statin can sometimes see their calcium score rise even as their risk falls. This apparent paradox is explained in our piece on statins and your calcium score. For people who need a more detailed look at the arteries themselves, a CT coronary angiogram can show both calcified and soft plaque. Inflammation markers such as hs-CRP can add yet another dimension. Which of these, if any, is right for you depends entirely on your circumstances and is a decision for you and your cardiologist.

Where the Guidelines Stand

The official guidance reflects this balanced reality. Different expert bodies place apoB at slightly different points on the spectrum, but none has discarded LDL cholesterol.

Guideline body Position on apoB
European (ESC/EAS) Accepts apoB as an alternative to LDL cholesterol for risk assessment. The 2025 update still confirms LDL cholesterol as the primary target.
Canadian (CCS) The most apoB-forward. Allows apoB to be used as the primary therapeutic target, especially when triglycerides are raised.
United States (ACC/AHA) Lists a high apoB as a risk-enhancing factor that supports more intensive treatment, but does not yet set a routine apoB target.
National Lipid Association Proposes graded apoB targets that become stricter as cardiovascular risk rises.

The main reason apoB has not yet replaced LDL cholesterol everywhere is not weak evidence. It is the absence of a single agreed target across all guidelines, combined with a degree of caution about changing long-established practice. Availability and cost also vary from one health system to another.

Should You Add ApoB to Your Next Blood Test?

In Australia, apoB can be measured by most pathology laboratories, usually reported in grams per litre. It is not always part of a standard lipid panel and may not be routinely rebated, so it is worth asking whether it applies to your situation and whether there is an out of pocket cost.

There is a strong argument for measuring apoB at least once if you fall into a higher-risk group, particularly if you have raised triglycerides, type 2 diabetes, metabolic syndrome, or a family history of early heart disease. It is also useful when your LDL cholesterol seems well controlled but you or your cardiologist remain concerned about residual risk. For someone already tracking LDL, HDL, and lipoprotein(a), as many thoughtful patients now do, apoB is a natural and informative addition rather than a replacement for any of them.

What apoB cannot do is stand alone. It works best alongside your other blood results, any imaging you have had, and the broader picture of your risk factors. The number is only as useful as the conversation it prompts with the person managing your care.

Heart Matters Resource

When in Doubt, Get Checked Out

If you are unsure whether your cholesterol results tell the full story, a focused review of your numbers with your GP or cardiologist is one of the most worthwhile conversations you can have.

Read: When in Doubt, Get Checked Out →

Conclusion

ApoB is one of the most useful advances in everyday cardiovascular risk assessment, because it counts the particles that actually cause plaque rather than estimating the cholesterol they carry. For people whose standard cholesterol result may be quietly misleading, it can uncover risk that would otherwise go unnoticed.

The balanced takeaway is this. LDL cholesterol, triglycerides, and lipoprotein(a) each remain valuable, and apoB sharpens the picture rather than replacing any of them. None of these numbers stands alone, because heart disease is multifactorial: your blood pressure, diabetes, smoking status, weight, and family history all matter alongside your lipids. The most useful conversation you can have is not about a single number, but about the whole picture, with the cardiologist who knows your circumstances.

Related Reading

Vitamin K and Your Arteries: What the Evidence Shows

vitamin K
Key Points
  • A new randomised trial, VitaK-CAC, found that a daily vitamin K2 supplement (a form called MK-7) modestly slowed the build-up of calcium in the heart’s arteries over two years compared with a placebo.
  • The effect was small. Calcium scores still rose in both groups, but they rose less in the people taking vitamin K2. The annual increase was reduced by about 19 points on the standard calcium scoring scale.
  • The study was small, with 180 participants, and ran into delays, so the findings are best seen as a promising early signal rather than proof that supplements prevent heart attacks.
  • Independent experts urge caution. We do not yet know whether slowing the rise in a calcium score actually translates into fewer heart attacks or strokes, and there is even debate about whether calcified plaque is the dangerous kind.
  • Vitamin K can interfere with warfarin and other blood-thinning medications, so nobody on an anticoagulant should start a supplement without speaking to their doctor first.

For years, the question of whether vitamin K supplements can protect the heart has been long on theory and short on evidence. A new clinical trial has now offered the clearest signal yet, and the answer is a carefully qualified “possibly”.

The study, called VitaK-CAC, was published recently in JAMA Cardiology. It found that a daily vitamin K2 supplement slowed the progression of calcium build-up in the coronary arteries over two years. The result is genuinely interesting. It is also a long way from a recommendation that everyone should head to the pharmacy.

What the Study Looked At

Researchers in the Netherlands recruited 180 adults who already had some calcium in their coronary arteries, measured using a CT scan that produces a coronary calcium score. Everyone in the study had a score between 50 and 400, which represents mild to moderate calcification.

Half the group took a daily dose of a vitamin K2 supplement known as MK-7, also called menaquinone-7. The other half took an identical placebo, an inactive tablet with no medicine in it, sometimes called a sugar pill. Neither the participants nor the researchers knew who was taking which until the study ended. This kind of design is the gold standard in medical research, because it stops expectation alone from influencing the result. The participants returned every six months for two years so their calcium scores and vitamin K blood levels could be tracked.

MK-7 is a specific form of vitamin K2. It is favoured in research because the body absorbs it well and it stays in the bloodstream longer than the more common vitamin K1 found in leafy greens.

What They Found

Calcium scores rose in both groups over the two years, which is what usually happens as calcification is a gradual, ongoing process. The difference was in how much they rose.

19 points the estimated reduction in the yearly rise of coronary calcium score among people taking vitamin K2, compared with placebo. VitaK-CAC trial, JAMA Cardiology, 2026

At the start, the two groups had similar average calcium scores, around 135 and 145. By two years, the placebo group had climbed to 214, while the vitamin K2 group reached 184. The slower climb in the supplement group was statistically significant, meaning it was unlikely to be down to chance alone.

Blood tests confirmed the supplement was doing something measurable. Vitamin K2 levels rose sharply in the treatment group, and a protein involved in keeping calcium out of artery walls behaved differently between the two groups. The researchers calculated that the calcium score and the vitamin K2 treatment were the two strongest predictors of how calcification changed over time.

Why Calcium in the Arteries Matters

Calcium in bones and teeth is essential. In artery walls it is a marker of atherosclerosis, the gradual furring and stiffening of blood vessels that underlies most heart attacks and strokes. The higher the calcium score, the more plaque a person tends to have, and the higher their cardiovascular risk.

The idea behind vitamin K2 is that it activates proteins which help direct calcium towards bones and away from artery walls, the same mechanism we explored in our explainer on vitamins D3 and K2. VitaK-CAC is the first reasonably robust trial to suggest the theory might hold up in the coronary arteries themselves.

A promising early result is not the same as a proven treatment. This trial opens a door. It does not tell us to walk through it just yet.

Why Experts Are Urging Caution

The researchers themselves were measured about their findings, and independent commentators were more cautious still. There are several reasons to hold back.

The first is size and design. With 180 participants and a study that suffered delays, this is a small trial. Small studies can produce real findings, but they need to be repeated in larger groups before anyone can be confident the result is reliable.

The second is more subtle. A calcium score is normally used to measure how much plaque a person has, not as something we actively try to lower. We have strong evidence that a high score predicts higher risk, but very little evidence about what happens when you deliberately slow the score’s rise. Lowering the number is not automatically the same as lowering the danger.

There is even a debate about whether calcified plaque is the dangerous kind. Statins tend to stabilise plaque and can leave behind calcium as a sign of that stability, a counter-intuitive effect we cover in our article on statins and your calcium score. Some experts worry that reducing calcified plaque could leave more of the softer, rupture-prone plaque behind. Nobody yet knows whether that concern is real. The earlier Danish AVADEC trial, which tested vitamin K2 in people with calcified aortic valves, found no significant benefit, underlining how unsettled this field still is.

What This Means for You

If you have had a calcium score done and it showed mild calcification, this study is worth being aware of, but it does not change current advice. The trial’s own authors said they would want larger studies before recommending vitamin K2 in any guideline, and other specialists who reviewed the work agreed they are not yet advising it for their patients.

Vitamin K2 is available without prescription and appears safe for most people at the doses studied. That is partly why some of the researchers said they would not object to people trying it. Safe and available, however, is not the same as proven to prevent heart attacks.

The most important practical point is a safety one. Vitamin K plays a central role in blood clotting, and it directly interferes with warfarin and similar anticoagulant medications. Anyone taking a blood thinner should not start a vitamin K supplement, or make large changes to their intake of vitamin K-rich foods, without first discussing it with their doctor or anticoagulation clinic.

More broadly, what is right for one person is not automatically right for another. Whether a supplement suits you depends on your own health history, the other medicines you take, and any conditions you live with. A supplement that is harmless for one person can interact with medication or be unsuitable for another. Your GP, cardiologist, or pharmacist knows your individual circumstances and is the right person to tell you whether vitamin K2 is sensible, safe, and compatible with the rest of your care.

For everyone, the foundations of heart health have not shifted: not smoking, managing blood pressure and cholesterol, staying active, and understanding your own cardiovascular risk factors. A supplement, even a promising one, sits well behind those.

Heart Matters Resource

When in Doubt, Get Checked Out

A calcium score, a new supplement, or a question about your medications is always worth raising with a professional who knows your history. If you are unsure whether something applies to you, that is reason enough to ask.

Read: When in Doubt, Get Checked Out →

Conclusion

VitaK-CAC is a thoughtful, well-conducted small trial that has nudged a long-standing theory a step closer to reality. It suggests that vitamin K2 might slow the build-up of calcium in the coronary arteries, and that finding deserves to be taken seriously and tested further.

For now, the sensible position is curiosity rather than action. If vitamin K2 interests you, the best next step is a conversation with your own cardiologist, GP, or pharmacist, who can tell you whether it is right for you and compatible with any other medicines or conditions you have. The science here is moving, and it is worth watching, but the proven path to a healthier heart still runs through the well-established basics.

Related Reading