
The Pulse Newsletter Expert heart health, in plain English. Fortnightly, from our clinicians. Subscribe →

Taking Heart Medicines Well: Why It Matters and What Helps

heart medicines adherence
Key Points

  • Heart medicines only protect the heart when they are taken, and missing or stopping them is one of the most common reasons treatment works less well than it could.
  • People miss or stop medicines for understandable reasons, including feeling well, side effects, a long list of tablets, cost, and confusion after a hospital stay.
  • Some heart medicines, such as antiplatelets and beta-blockers, can cause problems if stopped suddenly, which is why changes are usually planned with the prescribing doctor.
  • Simple supports such as daily routines, pill organisers, reminders, and an up-to-date medicine list help many people, though what works varies from person to person.
  • Pharmacists and doctors can often simplify a routine, change a medicine that is causing side effects, or answer questions about timing and missed doses.

Barely a day goes by in my clinic without a conversation about medicines. Questions about tablets are also one of the most common reasons patients call the office between appointments. I understand why.

Heart medicines can be genuinely confusing. The same medicine can have a generic name, a brand name, and a different-looking packet each time it is dispensed. Some people arrive at an appointment with a shopping bag full of boxes, and for others the morning tablets have become almost a meal in their own right.

Many of these medicines also do not make anyone feel better, at least not straight away. Some can make people feel a little worse at first, perhaps light-headed or tired. They can cause side effects, and the cost adds up. When a medicine brings no obvious benefit day to day, it is entirely reasonable to wonder why it is needed at all.

These are fair questions, and they deserve clear answers. This article explains why taking heart medicines as prescribed matters, why so many people find it hard, and what tends to make it easier.

Why Taking Medicines as Prescribed Matters

Most heart medicines work quietly in the background. Statins lower cholesterol and help stabilise plaque in the arteries. Antiplatelet medicines keep blood from clotting on a stent or a narrowed artery. Blood pressure medicines reduce strain on the heart and blood vessels.

None of these effects can be felt day to day. The benefit shows up as things that do not happen: a second heart attack, a stroke, or a hospital admission. That is exactly why the protection is easy to underestimate, and why it fades when doses are missed regularly.

About 1 in 2
people with long-term conditions do not take their medicines as prescribed, making this one of the most common challenges in all of medicine.
World Health Organization

Health professionals often use the word “adherence” for this. It means taking medicines in the way that was agreed with the prescribing doctor. It is not about blame. Missing doses is common, and the World Health Organization has long pointed out that health systems and clinicians share responsibility for making treatment easier to follow.

Why People Miss or Stop Their Medicines

The reasons are usually practical and very human. Feeling well is one of the most common. When there are no symptoms, it is natural to wonder whether a tablet is still needed.

Side effects are another. A dry cough on an ACE inhibitor, tiredness on a beta-blocker, or muscle aches that may or may not be related to a statin can all make people reluctant to keep going.

Other common reasons include:

  • A long list of tablets taken at different times of day.
  • Changes to medicines after a hospital stay that are not fully explained.
  • The cost of several medicines at once.
  • Running out between appointments.
  • Worry about taking a medicine for many years, often fuelled by stories online or from friends.
  • Forgetting, especially when routines change on holidays or weekends.

Worries about statins come up particularly often. These concerns are understandable and worth talking through openly. The article Statins: What Patients Ask Me Most covers the questions patients raise most frequently.
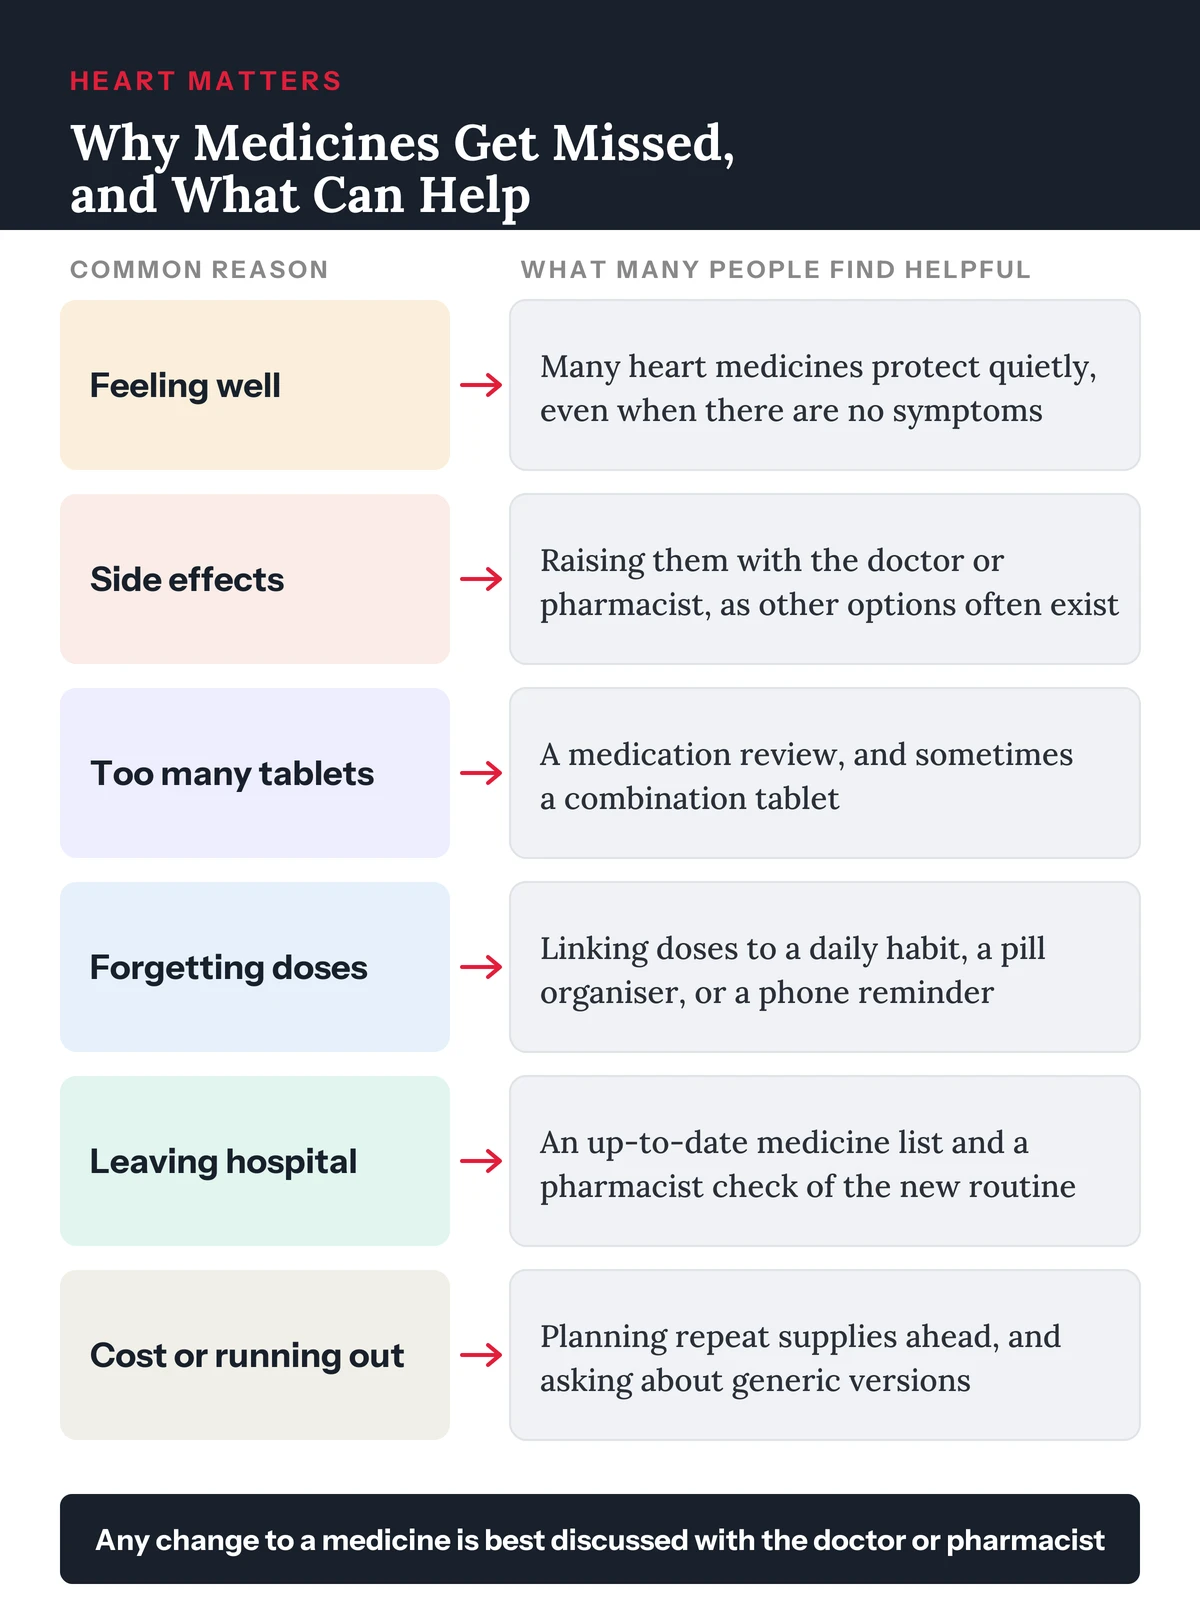
Infographic showing six common reasons heart medicines get missed, including feeling well, side effects, too many tablets, forgetting doses, leaving hospital, and cost, each paired with what many people find helpful
Common reasons medicines get missed, and what many people find helpful

What Happens When Heart Medicines Are Stopped

Stopping a medicine affects the body in different ways depending on the medicine. For some, the protection simply fades. For others, stopping suddenly can cause a rebound effect.

Antiplatelet medicines, such as aspirin, clopidogrel, and ticagrelor, prevent platelets from sticking together. When they are stopped, platelets become sticky again within days. After a stent, this raises the risk of a clot forming inside the stent, which can cause a heart attack. This is why the length of antiplatelet treatment is planned carefully, and why any pause around surgery or dental work is usually coordinated with the cardiologist. Whether, when, and how to stop is a decision for the prescribing doctor.

Beta-blockers slow the heart and reduce its workload. When they are stopped abruptly, the heart can speed up and become more sensitive to adrenaline, which may bring on palpitations, chest pain, or a rise in blood pressure. This is why the dose is usually reduced in stages rather than halted outright. There are some situations where a doctor may stop a beta-blocker straight away, and the decision rests with the prescribing doctor.

Statins and blood pressure medicines do not usually cause a sudden rebound, but their protective effect wears off over time once they are stopped. Cholesterol and blood pressure tend to drift back towards their earlier levels.

Practical Approaches Many People Find Helpful

There is no single system that suits everyone. The approaches below are ones that many people use, and the best choice depends on the person, their routine, and their medicines.

Linking doses to a daily habit

Tying a dose to something that already happens every day, such as breakfast, brushing teeth, or the evening news, is one of the most commonly used strategies. The habit acts as the reminder.

Pill organisers and blister packs

A weekly pill organiser with compartments for each day makes it easy to see whether a dose has been taken. Many pharmacies can also prepare medicines in sealed blister packs or sachets, sorted by day and time. These can be especially useful for people on several medicines, or for carers helping someone else.

Reminders

Phone alarms and medication reminder apps help some people, particularly when routines change. Others find a note on the fridge or a family member’s prompt works better.

An up-to-date medicine list

A written list of every medicine, including the dose and what it is for, is useful at every appointment and in an emergency. It is particularly valuable after a hospital stay, when medicines are often added, stopped, or changed. Many people keep a copy in their wallet or on their phone.

Planning repeat supplies

Running out is a common and avoidable reason for missed doses. Checking supplies a little ahead of time, and arranging repeat prescriptions before the last packet, helps keep treatment continuous.

Timing, Food, and Fitting Medicines Into the Day

Some medicines come with general guidance about when or how to take them. The details vary between medicines and between people, so the pharmacist or prescribing doctor is the best source of advice on any individual routine. Some common examples:

  • Aspirin is often taken with or after food, which can reduce stomach upset.
  • Fluid tablets (diuretics) are usually taken earlier in the day, so that extra trips to the toilet are less likely to disturb sleep.
  • For many statins, taking them consistently matters more than the exact time of day. The article on timing cholesterol-lowering medicines explains this in more detail.
  • For blood pressure medicines, a large trial of more than 21,000 people found no difference in heart attacks, strokes, or heart-related deaths between morning and evening dosing.

For most people, the best time to take a medicine is the time that fits their routine and is easiest to remember. Consistency usually matters more than the clock.

What About Missed Doses?

Almost everyone misses a dose at some point. What to do next depends on the medicine, how often it is taken, and how much time has passed. For some medicines, the missed dose is taken as soon as it is remembered. For others, it is skipped and the usual schedule continues. Doubling up is generally not recommended without advice.

Because the answer differs between medicines, a pharmacist or the prescribing doctor is the right person to ask. Many people find it helpful to ask this question once for each medicine, so they know in advance.

The Pharmacist’s Role

Pharmacists are often the most accessible health professionals, and their knowledge of medicines is extensive. They can explain what each medicine is for, check for interactions, and help with practical questions about timing, food, and missed doses.

Many pharmacies also offer a structured medication review. This involves looking across the whole list of medicines, including vitamins, supplements, and over-the-counter products, to make sure everything still makes sense together. Some things that seem unrelated, such as certain anti-inflammatory painkillers or cold and flu tablets, can affect blood pressure or interact with heart medicines.

Simplifying the Routine

A routine that is simpler is usually easier to keep. Doctors and pharmacists can often help with this in several ways:

  • Reviewing whether every medicine is still needed.
  • Moving doses to the same time of day where that is safe and suitable.
  • Using a combination tablet that contains two medicines in one.

A “polypill” takes this idea further by combining several heart medicines in a single tablet. In a large trial of older adults after a heart attack, a polypill containing aspirin, ramipril (an ACE inhibitor), and atorvastatin (a statin) improved how consistently people took their treatment. It also led to fewer major heart events compared with taking the same medicines separately. Polypills and combination tablets are not available everywhere, and they are not suitable for everyone, but they show how much a simpler routine can matter.

The best medicine routine is one that fits real life. If a routine is hard to follow, that is worth raising, because it can often be changed.

Side Effects and Worries Are Worth Raising

Quietly stopping a medicine because of a side effect or a worry is very common. Yet in many cases there is another option: a lower dose, a different medicine in the same family, or a change in timing. The ACE inhibitor cough is a good example, as switching to a related medicine called an angiotensin receptor blocker is a well-established solution for many people.

Doctors and pharmacists generally find it far more helpful to hear about a problem than to discover later that a medicine was stopped. An honest conversation is how a treatment plan gets adjusted to suit the person taking it.

For people who have recently had a heart event, the article on recovering after a heart attack explains how medicines fit into the wider picture of recovery.

Conclusion

Heart medicines protect quietly, and that protection depends on taking them consistently. Missing or stopping medicines is common, and the reasons are usually understandable: feeling well, side effects, complicated routines, cost, or simply forgetting.

Small supports such as routines, pill organisers, and an up-to-date medicine list help many people. Equally important is an open conversation with the pharmacist and doctor, who can often simplify a routine, answer questions about timing and missed doses, and find an alternative when a medicine is not agreeing with someone.
Related Reading

Can Plaque in Your Arteries Actually Shrink?

can plaque shrink
Key Points

  • Plaque in the heart arteries is not necessarily permanent. A study using CT scans found that lowering LDL cholesterol was followed by plaque shrinking in most people.
  • The more cholesterol came down, the more the plaque tended to shrink. The soft, fatty part of the plaque changed the most.
  • The findings fit with earlier imaging research, and with the wider evidence that statins do more than lower cholesterol. They also help calm and stabilise plaque in the artery wall.
  • This matters most for people who have already had a heart attack, a stent, a stroke, or bypass surgery, where the aim of treatment is to prevent a repeat event.
  • Concerns about statins are understandable. Side effects are real for some people, and there are usually options when a particular medicine does not suit.

Being told there is plaque in a heart artery can feel like being handed a verdict. One of the most common questions in a cardiology consultation follows straight after: is this permanent, or can anything be done about it?

It is a fair question, and the answer is more encouraging than many people expect. A study published in JAMA Cardiology adds to the evidence that plaque can not only be slowed, but in many people partly reversed.

What the Study Found

Researchers in Denmark followed 104 people who had newly been found to have narrowings in their heart arteries, a condition called atherosclerosis. None had been on long-term cholesterol treatment before.

Everyone was started on cholesterol-lowering medicine, and people were placed at random into one of two groups.

Group 1

Atorvastatin

A widely used statin, at a high dose

Cholesterol

Came down well

Plaque shrank in

About 3 in 4 people

Group 2

Rosuvastatin plus ezetimibe

A more potent statin at a high dose, with a second cholesterol-lowering tablet

Cholesterol

Came down further

Plaque shrank in

About 9 in 10 people

The aim was not to find out which statin is better. The two treatments were chosen to bring cholesterol down by different amounts, so the researchers could see whether lowering it further made a difference to the plaque. Detailed CT scans of the heart arteries were repeated over 18 months to find out.

The results were striking. Plaque shrank in most people in both groups, but more so with rosuvastatin and ezetimibe together. Across everyone, it shrank more in those whose LDL cholesterol, the “bad” cholesterol that builds plaque, came down the furthest.

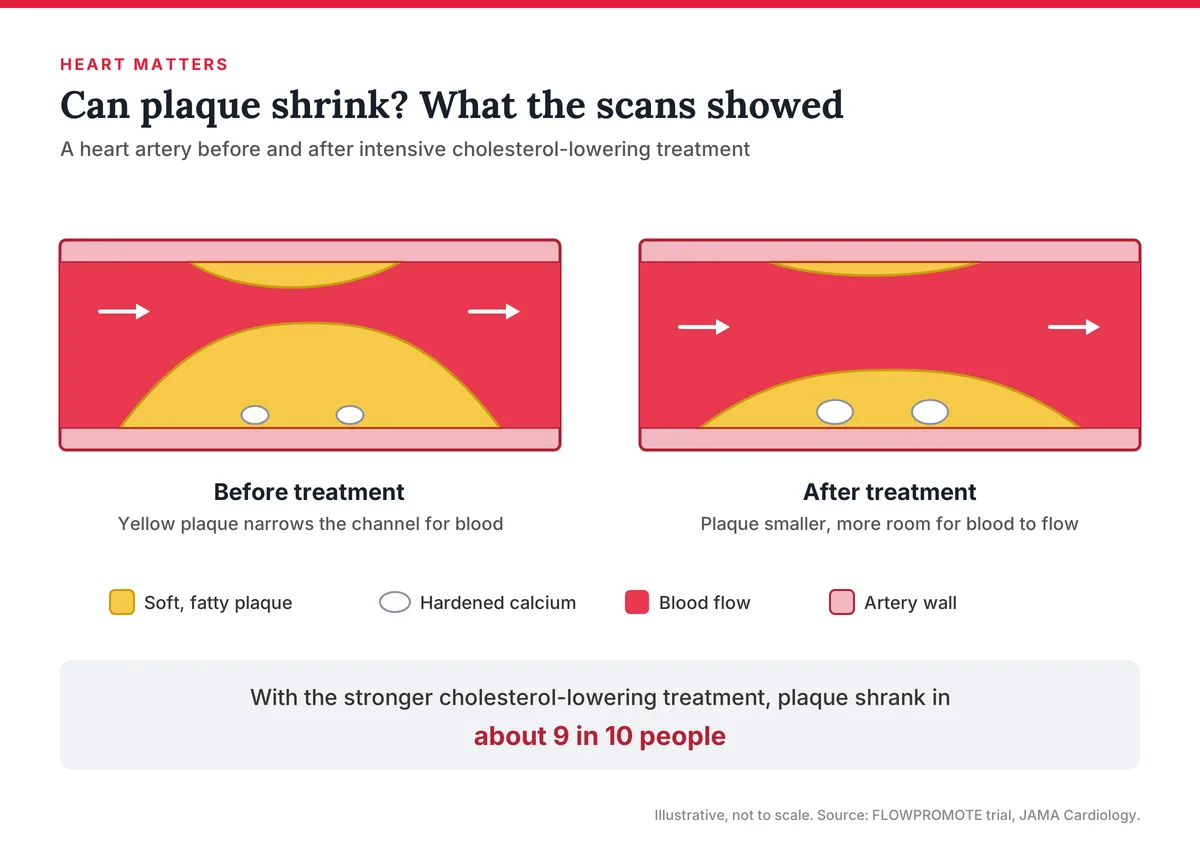
Illustration of a heart artery cross-section before and after cholesterol-lowering treatment, showing soft plaque reducing and the channel for blood flow widening
Soft plaque reduced most with intensive cholesterol lowering. Illustrative, not to scale.

How the two medicines work

Cholesterol reaches the blood by two main routes. Most is made by the liver, and the rest is absorbed from the gut. The two medicines in this study each work on a different route.

Statins: less made by the liver

Statins slow the liver’s own production of cholesterol. In response, the liver draws more LDL cholesterol out of the blood. Atorvastatin and rosuvastatin both work this way.

Ezetimibe: less absorbed from the gut

Ezetimibe reduces how much cholesterol is taken up from food and digestive juices in the gut. Less reaches the liver, which again pulls more LDL out of the blood.

Because they work in different places, a statin and ezetimibe together lower cholesterol further than a statin alone. Ezetimibe is a small daily tablet and is generally well tolerated, which is why it is a common partner to a statin when more lowering is needed.

Confirming What Earlier Research Showed

This is not the first time plaque has been seen to shrink. Earlier studies, mostly using a tiny ultrasound camera passed inside the artery, found the same pattern with statin treatment.

What this study adds is a wider view. CT scanning allowed the researchers to look along the length of all the main heart arteries, rather than one short section. The shrinking was seen across the whole picture.

It also fits with a long-held view among cardiologists: statins do more than lower a number on a blood test. Research suggests they also settle the low-grade inflammation inside the artery wall and help turn soft, unsettled plaque into firmer, more stable plaque.

Lowers LDL cholesterol

Less cholesterol reaches the artery wall, so less is available to build plaque.

Calms inflammation

Statins appear to quieten the inflammation that makes plaque active and unsettled.

Stabilises plaque

Plaque tends to become firmer and less likely to break open, which is what triggers most heart attacks.

Shrinks soft plaque

In many people, the soft, fatty part of the plaque gets smaller over time.

One finding can sound worrying at first. The small, hardened areas of calcium in the plaque grew in both groups. This is generally understood as part of plaque settling down under treatment, and it is explained further in our article on statins and calcium in the arteries.

Why This Matters Most After a Heart Event

The people in this study had not had a heart attack. Yet the people who often benefit most from this kind of treatment are those who already have: people recovering after a heart attack, those who have had a stent or bypass surgery, and those who have had a stroke caused by narrowed arteries.

A stent or bypass fixes the narrowing that caused the trouble. It does not treat the plaque elsewhere in the arteries, and that plaque is where a future event is most likely to start. This is why medication remains part of care after any procedure, and why a stent or bypass is one part of treatment rather than the whole of it.

After an event, the goal is clear: to reduce the chance of it happening again. Large trials involving many thousands of people have shown that lowering LDL cholesterol does exactly that. Studies like this one help show what may be happening inside the artery while that protection builds.

Plaque is not always a one-way street. With the right treatment, it can be slowed, steadied, and in many people partly reversed.

Understanding the Worry About Statins

Many people feel uneasy about statins. They may have read alarming stories, had a friend who felt unwell on one, or would rather not take a tablet for life. These concerns are understandable and deserve a proper conversation.

It is also fair to say that some people are started on a statin without a thorough look at their individual risk. For someone at low risk, the decision is genuinely finely balanced and worth talking through.

After a heart attack, stent, stroke, or bypass, the balance is very different. The benefit of lowering cholesterol in this group is among the best established in all of medicine.

Side effects are real for some people, most often muscle aches. Large studies comparing statins with dummy tablets have found that many aches occur at similar rates on both, but some people are genuinely affected. In this study, a number of participants had their treatment adjusted, and only 2 of the 104 stopped their statin completely.

When a statin does not suit, there are usually other routes. Clinicians commonly try a different statin or dose, or add or switch to other medicines such as ezetimibe or an injectable PCSK9 treatment.

Stopping a statin after a heart event removes its protective effect on the plaque, and cholesterol levels rise again within weeks. That is why changes are usually made by adjusting or swapping treatment rather than stopping altogether. Whether and how to change a statin is a decision for the prescribing doctor.

What Else Can Change

Medication is where the clearest evidence for shrinking plaque lies. Other changes are strongly linked to whether plaque goes on to cause a heart attack or stroke:

  • Not smoking, which is among the most powerful changes available.
  • Keeping blood pressure at a healthy level.
  • Regular physical activity, including walking.
  • A heart-healthy eating pattern, such as a Mediterranean-style diet.
  • Good blood sugar control for people with diabetes.

None of this needs to happen at once. Most people find it more realistic to start with one or two changes and build from there. Cardiac rehabilitation programs, offered to many people after a heart event, are a well-supported place to start.

What This Study Does Not Tell Us

This was a small study, and it measured plaque on scans rather than counting heart attacks or strokes. Most participants were men, and all were starting treatment for the first time. The results may differ for people who have been on a statin for years.

Even so, the direction of the findings matches what larger studies have shown over many years. Lower cholesterol, sustained over time, means healthier arteries and fewer repeat events.

Conclusion

Plaque in a heart artery is an important finding, but it is not necessarily a fixed one. This study adds to the evidence that lowering cholesterol can shrink and settle plaque, and that statins do more for the artery than a blood test alone can show.

For anyone who has had a heart attack, stent, stroke, or bypass, that is a reason for genuine hope. Questions or worries about statins are worth discussing with your cardiologist, who can tailor treatment to suit the individual.

Related Reading

To Fast or Not to Fast Before a Blood Test?

blood test
Key Points

  • Most heart-related blood tests do not require fasting. Fasting matters most for the fasting glucose and glucose tolerance tests, and is often recommended for cholesterol tests, particularly when triglycerides are measured.
  • Fasting is often recommended before a cholesterol panel, because meals raise triglycerides and fasting keeps results consistent between tests. A normal meal changes LDL and HDL cholesterol only slightly, so a non-fasting sample is acceptable for many routine checks.
  • The HbA1c test, which reflects average blood glucose over the previous two to three months, does not require fasting.
  • When fasting is needed, it usually means no food or drinks other than water for 8 to 12 hours. Exact instructions vary between laboratories.
  • Fasting can cause low blood sugar in people taking insulin or some diabetes tablets, which is why they are usually given specific instructions before a fasting test.

Few instructions cause as much confusion as “fast before your blood test.” Does black coffee count? What about morning tablets? And why does one cholesterol test come with fasting instructions while the next does not?

The short answer is that fasting matters a great deal for a few tests, matters in particular situations for cholesterol, and makes very little difference for most others. Knowing which is which can spare an uncomfortable morning and, for some people, avoid a genuine risk.

Why Food Affects Some Blood Tests

After a meal, sugars and fats from food pass into the bloodstream. For a few hours, the levels of some substances in the blood rise, while others barely change.

Glucose (blood sugar) and triglycerides are the two most affected. A test designed to measure a “resting” level of either can be misleading if taken soon after eating. Most other routine blood tests are affected so little by a normal meal that fasting makes no practical difference.

Which Heart-Related Tests Need Fasting?

The table below shows how fasting requirements typically apply to common blood tests in heart care. Individual laboratories may set their own requirements, and the instructions given with a test request take priority.

Test Fasting Usually Needed? Why
Fasting glucose Yes Food raises blood glucose for several hours
Glucose tolerance test Yes Measures the response to a standard glucose drink from a fasting start
HbA1c No Reflects average glucose over months, not today’s meals
Cholesterol panel, including triglycerides Often recommended Meals raise triglycerides, and fasting keeps results comparable from one test to the next
Iron studies Sometimes Some laboratories prefer a morning sample, as iron levels vary
Troponin and BNP No Often urgent, and not meaningfully affected by food
INR, kidney function, hs-CRP Usually not Routine checks are generally done without fasting

Tests used to assess chest pain or heart strain, such as troponin and BNP, are taken whenever they are needed, often in an emergency department. Fasting plays no part in them.

Routine monitoring tests, such as the INR used for people taking warfarin and the hs-CRP test, are generally done without fasting. For iron studies, used to check for iron deficiency, some laboratories prefer a morning sample because iron levels in the blood vary through the day.

Glucose Tests and Fasting

Blood glucose tests are where fasting matters most. They are used to check for diabetes and prediabetes, both important risk factors for heart disease.

Fasting glucose

A fasting glucose test measures blood sugar after a period without food. The American Diabetes Association defines fasting as no calorie intake for at least 8 hours. An overnight fast with a morning test is the usual arrangement.

Eating before this test can push the result into a range that looks like diabetes when it is not. That is why a fasting glucose result taken after breakfast cannot be interpreted in the usual way.

Glucose tolerance test

The oral glucose tolerance test shows how well the body clears sugar from the blood. After an overnight fast, a blood sample is taken, a standard drink containing 75 g of glucose is given, and a second sample is taken two hours later. The test takes a couple of hours in total and is commonly used in pregnancy.

HbA1c

The HbA1c test measures how much glucose has attached to red blood cells over the previous two to three months. Because it reflects a long-term average, a meal beforehand has no meaningful effect, and no fasting is needed.

HbA1c is reported in two ways around the world: as a percentage, or in millimoles per mole (mmol/mol). A result of 6.5% is the same as 48 mmol/mol.

Glucose results in both units

Glucose is reported in mmol/L in many countries and in mg/dL in others, including the United States. A result in mmol/L multiplied by 18 gives the value in mg/dL. The table shows the levels the American Diabetes Association uses to define diabetes.

Test Fasting? Diabetes Range (mmol/L) Diabetes Range (mg/dL)
Fasting glucose Yes 7.0 or higher 126 or higher
Glucose tolerance test (2 hours) Yes 11.1 or higher 200 or higher
Random glucose, with symptoms No 11.1 or higher 200 or higher

The range for prediabetes differs between organisations. The American Diabetes Association uses a fasting glucose of 5.6 to 6.9 mmol/L (100 to 125 mg/dL), while the World Health Organization uses 6.1 to 6.9 mmol/L (110 to 125 mg/dL). Unless a result is clearly abnormal, a diagnosis of diabetes is usually confirmed with a second test, and interpreting results is a matter for the requesting doctor.

Cholesterol Tests: When Fasting Helps

Cholesterol tests were traditionally done after fasting. A joint consensus statement from the European Atherosclerosis Society and the European Federation of Clinical Chemistry and Laboratory Medicine reviewed large studies comparing fasting and non-fasting results.

After normal meals, triglycerides rose by up to about 0.3 mmol/L (26 mg/dL), while total and LDL cholesterol fell by about 0.2 mmol/L (8 mg/dL). HDL cholesterol and lipoprotein(a) were not affected. Non-fasting results predicted heart disease risk just as well as fasting ones, so the statement recommends non-fasting samples for routine testing.

Why triglycerides are different

Triglycerides are the part of the cholesterol panel most affected by food. The average rise after a meal is small, but it can be much larger after a fatty meal, and in people with diabetes, excess abdominal weight, or already raised triglycerides.

This matters for LDL cholesterol too. In most laboratories, LDL is calculated from the other values, including triglycerides. The higher the triglyceride level, the less accurate that calculation becomes.

For these reasons, American guidelines state that a fasting sample is most helpful in several situations:

  • When triglycerides have been high before, particularly above 4.5 mmol/L (400 mg/dL).
  • When high triglycerides are being diagnosed or monitored.
  • When there is a family history of early heart disease or an inherited cholesterol disorder.
  • When checking how much risk remains for a person already on cholesterol-lowering treatment.

European guidance suggests a fasting repeat when a non-fasting triglyceride level is above 5 mmol/L (440 mg/dL). In everyday practice, many doctors request a fasting sample for cholesterol tests, particularly when triglycerides are part of the question. When a test request asks for fasting, that instruction is the one that applies.

I usually recommend fasting before a cholesterol test. I often request a full panel, including glucose and triglycerides, and fasting keeps results consistent, which makes monitoring over time more reliable.

Prof. Peter Barlis, Interventional Cardiologist

What Counts as Fasting?

Definitions vary. The American Diabetes Association uses at least 8 hours without calories, while European laboratory guidance recommends 12 hours. Water is permitted in both, and many laboratories encourage it, as good hydration can make blood easier to draw.

European laboratory guidance also advises against alcohol for 24 hours beforehand, and against coffee, tea, and smoking on the morning of the test. Chewing gum can affect some results too. Because practice differs between countries and laboratories, the instructions supplied with the test are the most reliable guide.

Medicines and Fasting

Advice about medicines on the morning of a fasting test varies. Most regular heart medicines are commonly taken as normal with water, but some laboratories and doctors ask for particular medicines to be delayed until after the sample. The requesting doctor or laboratory gives instructions for each person.

People with diabetes need particular care. Insulin and some diabetes tablets can cause low blood sugar when a meal is skipped, which can lead to shakiness, sweating, confusion, or fainting. For this reason, people taking these medicines are usually given specific instructions about timing their medicine and the test, and tests are often booked early in the morning.

Conclusion

Fasting matters for a small number of blood tests, chiefly the fasting glucose and glucose tolerance tests. For cholesterol tests, fasting is often recommended because it gives a clearer and more consistent triglyceride result, although a non-fasting sample is acceptable for many routine checks. For most other heart-related tests, including HbA1c, fasting makes little or no difference.

When fasting is required, the instructions that come with the test request are the best guide, and questions about medicines are worth raising with the requesting doctor or laboratory beforehand. A few minutes of clarification can prevent a wasted trip or an unreliable result.

Related Reading

Understanding Your Cholesterol Test: What Each Number Means

cholesterol test
Key Points

  • A standard cholesterol test, often called a lipid profile, measures several different fats in the blood. LDL cholesterol is the number most closely linked to heart attack and stroke risk.
  • There is no single “normal” LDL level that suits everyone. The goal depends on each person’s overall cardiovascular risk, and a result flagged as normal on a lab report may still be above the goal for someone with heart disease.
  • Results are reported in one of two units depending on the country and laboratory: millimoles per litre (mmol/L) or milligrams per decilitre (mg/dL). The same result looks very different in each.
  • Lipoprotein(a) is the exception. Its two units, mg/dL and nmol/L, cannot be converted reliably, so the result is best read in the unit the laboratory used.
  • For most routine tests, fasting beforehand is not required.

A cholesterol result often arrives as a column of numbers, a few abbreviations, and perhaps an asterisk. What it rarely includes is an explanation. One figure may be flagged high, another low, and it is not always clear which matter most.

This guide explains what each part of a standard cholesterol test measures, how the two international units work, and why the right number for one person can be quite different from the right number for another.

Why Cholesterol Matters

Cholesterol is a waxy fat the body needs to build cells and make hormones. It travels in the blood inside particles called lipoproteins. Some of these particles can lodge in artery walls, where they build up over many years into the fatty plaque of atherosclerosis.

That plaque narrows arteries and can rupture, triggering a heart attack or stroke. The more of these particles in the blood, and the longer they are there, the greater the build-up. This is why cholesterol testing sits at the centre of heart disease prevention.

What a Cholesterol Test Measures

A standard lipid profile usually reports four or five values. Some laboratories add others, such as lipoprotein(a) or apolipoprotein B, when requested.

The numbers on a cholesterol report
LDL cholesterol
The main driver of plaque build-up. The number most treatment goals are based on.

HDL cholesterol
Carries cholesterol away from the arteries. Low levels are linked to higher risk.

Triglycerides
A different type of blood fat, influenced by diet, alcohol, weight, and diabetes.

Total cholesterol
All cholesterol combined. Useful for calculations, less useful on its own.

Non-HDL cholesterol
Total minus HDL. Captures all the particles that can form plaque.

Lipoprotein(a)
An inherited particle, usually measured once in a lifetime rather than routinely.

LDL cholesterol

LDL (low-density lipoprotein) cholesterol is the most important number on the report. Large genetic studies and clinical trials consistently show that lower LDL levels mean less plaque and fewer heart attacks and strokes. Most treatment decisions are built around it.

In many laboratories LDL is calculated from the other values rather than measured directly. The calculation is less accurate when triglycerides are very high or LDL is very low, which is why some laboratories measure it directly in those situations.

HDL cholesterol

HDL (high-density lipoprotein) cholesterol helps carry cholesterol away from artery walls. Low HDL levels are linked to higher cardiovascular risk. However, medicines that raise HDL have not, on their own, been shown to reduce heart attacks in trials, and HDL is not a treatment goal in major guidelines.

Triglycerides

Triglycerides are the body’s main store of fat. Levels are influenced by diet, alcohol, body weight, diabetes, and some medicines. Raised triglycerides add to cardiovascular risk, and very high levels can also inflame the pancreas.

Non-HDL cholesterol

Non-HDL cholesterol is total cholesterol minus HDL. It captures every type of particle that can contribute to plaque, not only LDL. Both European and American guidelines use it as a secondary goal, particularly for people with raised triglycerides or diabetes.

Two Units, One Result

Cholesterol results are reported in one of two units, depending on the country and the laboratory. Much of the world, including the UK, Canada, Australia, and New Zealand, uses millimoles per litre (mmol/L). The United States and a number of other countries use milligrams per decilitre (mg/dL).

The same blood sample gives very different-looking numbers in each unit. An LDL of 2.6 mmol/L is the same as 100 mg/dL. Knowing which unit a report uses is the first step in making sense of it, and the unit is usually printed beside each value.

For cholesterol values (total, LDL, HDL, and non-HDL), a result in mmol/L multiplied by about 38.7 gives the value in mg/dL. Triglycerides use a different factor, about 88.6, because they are a different molecule. Throughout this article, mmol/L is given first, with mg/dL in brackets.

Lipoprotein(a) is the exception

Lipoprotein(a), often written Lp(a), is reported either in mg/dL or in nanomoles per litre (nmol/L). Unlike cholesterol, there is no reliable way to convert between these units, because Lp(a) particles vary in size from person to person.

The guidelines themselves show the difficulty. European guidelines treat an Lp(a) above 50 mg/dL (105 nmol/L) as a risk-enhancing factor, while American guidelines treat 50 mg/dL (125 nmol/L) as the equivalent threshold. An Lp(a) result is therefore best read in the unit the laboratory reported, without converting it.

Why There Is No Single “Normal” Number

Laboratory reports usually print a reference range beside each result. This range describes typical values in the general population. It does not describe the right level for any particular person.

Guidelines set LDL goals according to overall cardiovascular risk. That risk takes into account age, blood pressure, smoking, diabetes, kidney function, family history, and whether heart or artery disease is already present. The higher the risk, the lower the LDL goal.

This is why an LDL of 2.5 mmol/L (97 mg/dL) might be flagged as normal on a report, yet sit well above the goal for someone who has had a heart attack. The table below shows the goals used in European guidelines. American guidelines use closely matching goals for most risk groups.

Risk Level LDL Goal (mmol/L) LDL Goal (mg/dL)
Very high Below 1.4 Below 55
High Below 1.8 Below 70
Moderate Below 2.6 Below 100
Low Below 3.0 Below 116

Most people who have had a heart attack, a stent, or a stroke fall into the very high risk group. European guidelines also recommend that people in the high and very high risk groups reduce their LDL by at least half from their starting level. Which risk group applies to an individual, and what their goal should be, is a judgement for their own doctor.

Preparing for the Test

For most routine cholesterol tests, fasting is not required. A meal before the test has only a small effect on most values, although triglycerides rise a little after eating. A fasting sample is sometimes requested when triglycerides are high or when an earlier result needs checking.

Cholesterol levels also vary naturally from one test to the next. An illness in the weeks before the test, a significant change in diet, or a change in medicines can all shift results. For this reason, doctors usually look at the trend across several tests rather than reacting to a single figure.

What Happens After the Result

When LDL is above a person’s goal, the first step is usually a look at overall risk and lifestyle. Diet plays a real but often modest role. Eating patterns rich in unsaturated fats and fibre help, and some foods affect blood cholesterol less than commonly assumed, as the evidence on eggs and cholesterol shows.

Where medicines are needed, statins are the foundation of treatment. Ezetimibe is commonly added when a statin alone does not reach the goal, and PCSK9 inhibitors are an option for people at the highest risk. A repeat test after starting or changing treatment shows how well it is working.

A cholesterol result means little on its own. It becomes meaningful when read alongside a person’s overall risk.

Conclusion

A cholesterol test is one of the most useful blood tests in heart health, but the numbers only make sense in context. LDL cholesterol matters most, the unit on the report changes how every figure looks, and the right goal depends on each person’s overall risk rather than a single normal range.

For anyone unsure what their own results mean, the report is worth discussing with their doctor or cardiologist, ideally alongside their other risk factors. That conversation turns a column of numbers into a plan.

Related Reading

Cardiac Rehabilitation: The Heart Treatment Most People Miss

cardiac rehabilittion
Key Points

  • Cardiac rehabilitation is a structured program of supervised exercise, education, and emotional support offered after a heart attack, a stent procedure, bypass surgery, and several other heart conditions.
  • A Cochrane review of 85 trials involving more than 23,000 people found that exercise-based rehabilitation lowered the chance of another heart attack and of being admitted to hospital in the following year.
  • Supervised exercise after a heart event is very safe. One large study recorded about one serious cardiac event for every 50,000 hours of exercise training.
  • Only around 4 in 10 eligible people take part, and women and older people are the least likely to be referred or to attend.
  • Trials found similar benefits whether rehabilitation took place at a centre or at home, which opens the door for people who live far away, work, or care for others.

Leaving hospital after a heart attack or heart surgery can feel like being handed back a body that no longer feels familiar. Walking to the letterbox raises questions. So does climbing stairs, going back to work, or simply sleeping through the night without worry.

Cardiac rehabilitation exists to answer those questions. It is one of the best-studied treatments in cardiology, yet it is also one of the most underused. Many people who would benefit never start, and many who start do not finish.

What Is Cardiac Rehabilitation?

Cardiac rehabilitation, often shortened to cardiac rehab, is a coordinated program that helps people recover after a heart event and lowers the chance of another one. It combines supervised exercise with education about the heart, medicines, and lifestyle, along with support for the emotional side of recovery.

It is not a single class or a leaflet. It is usually run by a team that can include nurses, exercise physiologists, physiotherapists, dietitians, psychologists, and doctors. The exercise is tailored to each person’s fitness and condition, then increased gradually as confidence and strength return.

Who It Is For

Rehabilitation is most often offered to people who have had a heart attack, a stent inserted during a coronary angiogram, or bypass surgery. People living with stable angina are also commonly referred.

Many programs also accept people with heart failure, people recovering from heart valve surgery, and people who have had a pacemaker or defibrillator fitted. Which conditions qualify varies between countries and services. Whether a program suits a particular person is worth discussing with their cardiologist or treating team.

The Three Phases of Rehabilitation

Rehabilitation is often described in phases. The names and numbering differ between countries, but the overall journey is broadly similar everywhere.

1
In hospital
Recovery begins on the ward. Staff help people get up and walk safely, explain what has happened to the heart, and arrange referral to an outpatient program before discharge.

2
Structured program
The core of rehabilitation. Supervised exercise sessions, usually one to three times a week over several weeks, run alongside education and support. This can take place at a hospital, a community centre, or at home.

3
Lifelong maintenance
The habits built during the program carry on independently. Some people join community exercise groups, while others continue on their own with occasional check-ins.

What Happens in a Program

Programs usually begin with an assessment. This usually covers symptoms, medicines, fitness, risk factors such as blood pressure and cholesterol, and how the person is coping emotionally. The results shape a plan that fits the individual.

What a program usually includes
Aerobic exercise
Walking, cycling, or circuit work, monitored by staff and built up gradually.

Strength work
Light weights or resistance bands to rebuild muscle and everyday strength.

Heart education
How the heart works, what happened, and which symptoms need attention.

Medicines
What each medicine does and why it has been prescribed.

Emotional support
Help with anxiety, low mood, and the loss of confidence common after a heart event.

Lifestyle
Support with eating well, stopping smoking, sleep, and returning to work and driving.

The exercise sessions usually centre on activities such as walking and stationary cycling. Many programs also include resistance training, which helps with everyday tasks such as carrying shopping or getting up from a chair.

The education sessions often cover eating patterns such as the Mediterranean diet, and practical support for stopping smoking. Family members and carers are often welcome to attend.

What the Evidence Shows

The most thorough look at the evidence is a Cochrane review that pooled 85 randomised trials involving 23,430 people with coronary heart disease. Most had had a heart attack, a stent, or bypass surgery. The review compared people who took part in exercise-based rehabilitation with people who received usual care without structured exercise.

12 in 100
people in rehabilitation were admitted to hospital within a year, compared with 21 in 100 who did not take part.
Cochrane Review, 85 trials
1 in 75
For every 75 people who took part, one heart attack was prevented within a year.
Cochrane Review, 85 trials

In plain numbers, about 5 in 100 people who did not take part had a heart attack within a year, compared with between 3 and 4 in 100 of those who did. The reviewers rated this finding as high certainty. The fall in hospital admissions was rated moderate certainty.

The effect on survival within the first year was small and less certain, at about 5 in 100 deaths with rehabilitation compared with about 6 in 100 without. Trials that followed people for longer found fewer deaths from heart causes among those who took part, although fewer trials contributed to that result.

Quality of life scores also improved slightly, although the differences may be too small for many people to notice. The benefits were broadly similar regardless of the type of heart condition, whether the program was exercise alone or combined with education, and where it took place.

The evidence has limits. Most people in the trials were middle-aged men, and women made up fewer than 15% of participants. Findings in women and in older people with several health conditions rest on thinner data.

Rehabilitation is not a reward for recovering well. It is part of how recovery happens.

Is Exercise Safe After a Heart Event?

Fear of bringing on another heart attack is one of the most common reasons people hold back. The data are reassuring. One large study of more than 25,000 people in rehabilitation programs recorded about one serious cardiac event for every 50,000 hours of exercise training.

Part of that safety comes from the assessment at the start, which sets exercise at a level suited to the individual. Staff also watch for chest pain, unusual breathlessness, dizziness, or palpitations during sessions. These symptoms usually prompt a pause in exercise and a medical review.

Why So Many People Miss Out

Despite strong guideline support from the European Society of Cardiology and the American Heart Association, only around 4 in 10 eligible people take part. Some are never referred. Others are referred but do not start, or start but do not finish.

The reasons are often practical. Travel distance, work commitments, caring responsibilities, and cost all play a part, and access and funding vary widely between countries. Some people feel well after a stent and see no need for it. Others feel too anxious or unwell to begin.

Women and older people are the least likely to be referred and to attend. This matters because both groups face a real risk of further heart problems, and both stand to gain from the support rehabilitation provides, as outlined in recovering after a heart attack.

Home-Based and Virtual Programs

Rehabilitation does not have to take place in a hospital gym. In the Cochrane review, about a quarter of the trials delivered rehabilitation entirely at home, some using mobile phones or the internet. The benefits were similar regardless of setting.

Home and virtual options can suit people in rural areas, people who work, and people who are uncomfortable in group settings. Centre-based programs offer direct supervision and the encouragement of others on the same path. The format that works best is the one a person can keep attending, and the choice is typically made together with the rehabilitation team.

Conclusion

Cardiac rehabilitation lowers the chance of another heart attack and of returning to hospital, and it helps people regain strength and confidence after a frightening event. It is safe, well supported by evidence, and offered in several formats, yet most eligible people never take part.

For anyone recovering from a heart attack, a stent, or heart surgery, rehabilitation is worth discussing with the treating cardiologist or hospital team. It is one of the most useful conversations in the whole recovery journey.

Related Reading

Berry Power Protein Booster: A Cardiologist’s Breakfast

heartmatters.com 45

The breakfast question patients ask most often is what will actually keep them full until lunch. This 10-minute smoothie answers it with viscous fibre, protein, and berries, and explains why the milk you pour in matters more than it looks.

T Wave Inversion on Your ECG: What It Actually Means

T wave inversion
Key Points

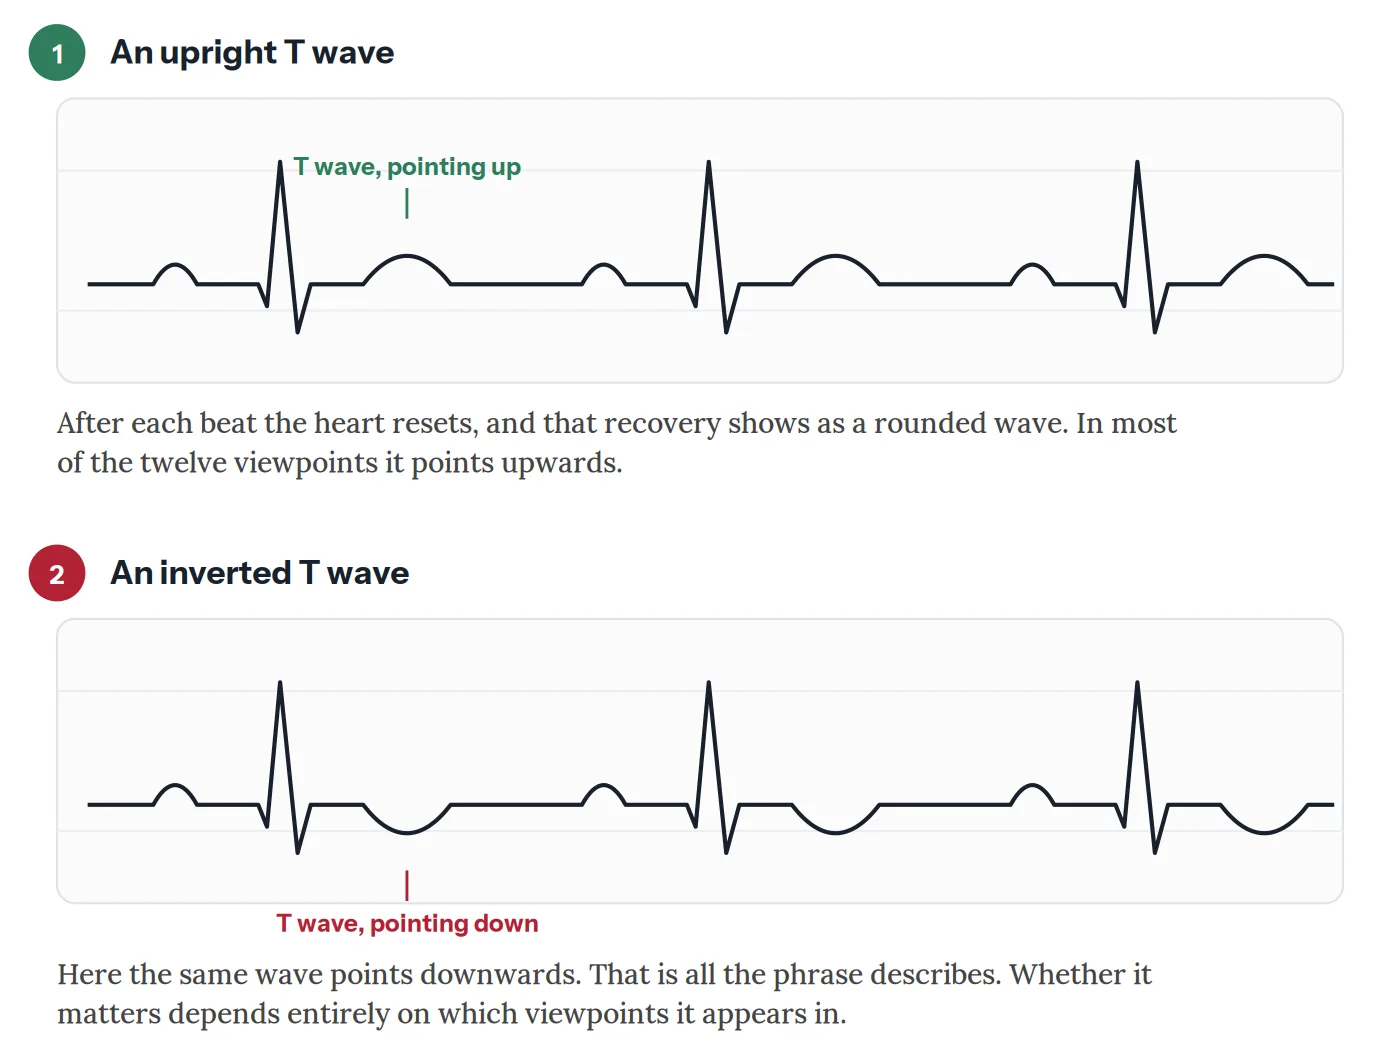
  • An ECG records the heart from twelve different viewpoints. After each beat the heart resets, and that recovery shows on the tracing as a rounded wave called the T wave.
  • In most viewpoints that wave points upwards. When it points downwards instead, the report describes it as T wave inversion.
  • In several viewpoints a downward T wave is entirely normal and expected, so the phrase on its own says very little.
  • What determines whether it matters is which viewpoints are involved, whether it is new compared with a previous tracing, and whether there are any symptoms.
  • A previous ECG, if one exists, is often the single most useful piece of information, because a longstanding pattern and a new one carry very different weight.

Of all the phrases that turn up on an ECG report, T wave inversion is among the most common and the least self-explanatory. It sounds like something has been reversed, or has gone wrong in a way that ought to be obvious.

What it describes is narrower than that. A small wave on the tracing points downwards instead of upwards. In several of the heart’s twelve viewpoints that is completely normal. In others it can be important. The phrase alone does not tell you which situation you are in.

What the T Wave Is

Each heartbeat has two halves. The heart muscle activates and contracts, then it has to reset electrically before it can do it again.

On an ECG tracing, the tall spike is the contraction. The rounded wave that follows it is the reset. That second wave is the T wave.

Two ECG tracings compared. In the first the T wave after each beat points upwards, which is the usual pattern in most leads. In the second the T wave points downwards, which is what a report means by T wave inversion
The difference is simply which way the recovery wave points. Whether that matters depends on which of the heart’s twelve viewpoints it appears in, Heart Matters

Because the twelve viewpoints look at the heart from different angles, the same electrical recovery appears differently in each. In most of them the T wave points upwards. In a few it normally points down, and always has.

Where a Downward T Wave Is Simply Normal

This is the part that resolves most people’s concern, and it is worth stating plainly.

One viewpoint, the one labelled aVR, has a downward T wave in essentially everybody. It looks at the heart from the opposite direction to the others, so an upward wave there would be the abnormal finding.

Two others, V1 and lead III, very commonly show a downward T wave in healthy people. So does lead V2 in some. An automated report will still flag these, because software counts rather than interprets.

There is also a pattern sometimes called the persistent juvenile pattern. Children normally have downward T waves across several of the chest viewpoints, and in most people these turn upward through adolescence. In some adults, more often women and more often people of African or Caribbean ancestry, the childhood pattern simply persists. It is a normal variant, not a disease.

In some viewpoints a downward T wave is the expected finding. The software flags it anyway, because it counts rather than interprets.

What Determines Whether It Matters

Three questions decide almost everything, and a cardiologist works through them in this order.

Reassuring
Usually needs nothing beyond an explanation
  • The inversion sits only in aVR, V1, or lead III, where it is normal.
  • An older tracing shows the same pattern, unchanged over years.
  • There are no symptoms, and the rest of the ECG is normal.
  • The person is young, fit, and the pattern fits a recognised normal variant.
Worth explaining
Usually has a cause that is already known
  • The inversion accompanies a bundle branch block, where changed conduction alters the recovery wave as a matter of course.
  • It accompanies a thickened heart muscle, where the pattern is sometimes described as strain.
  • Certain medicines, including digoxin, change the shape of the recovery wave predictably.
  • Low potassium or magnesium can flatten or invert it, and correcting the level corrects the tracing.
Investigated promptly
The pattern, the symptoms, or the change over time raises concern
  • The inversion is new compared with a previous tracing.
  • It appears across several neighbouring viewpoints rather than one.
  • It is deep and symmetrical rather than shallow, particularly across the front of the heart.
  • There are symptoms, especially chest discomfort, breathlessness, or fainting.

The Pattern Cardiologists Look For First

There is one specific arrangement worth knowing about, because it is the reason this finding is never dismissed out of hand.

Deep, symmetrical T wave inversion across the viewpoints that look at the front of the heart, appearing in someone who has recently had chest pain that has since settled, can indicate a critical narrowing in the artery supplying that territory. The person often feels fine at the moment the tracing is taken, which is exactly what makes it dangerous.

It is uncommon. Most T wave inversion is nothing like this. But it is the reason a cardiologist will ask carefully about recent chest pain even when someone currently feels well, and why this particular pattern prompts prompt assessment of the coronary arteries rather than watchful waiting.

Other Causes Worth Knowing

Beyond the coronary arteries, several conditions change the recovery wave.

A previous heart attack leaves permanent changes in the viewpoints that looked at the damaged area, often alongside Q waves.

Thickened heart muscle, whether from long-standing high blood pressure or from hypertrophic cardiomyopathy, alters recovery across several viewpoints. In the inherited condition the changes can be striking, and they are one of the findings that prompts further imaging in a young person.

Inflammation of the heart muscle or its surrounding sac produces widespread changes rather than ones confined to a single artery’s territory.

A clot in the lungs can invert the T waves across the right-sided viewpoints, usually alongside breathlessness and a fast heart rate.

Conditions affecting the brain, including bleeding around it, can produce dramatic deep T wave inversion. These are sometimes called cerebral T waves, and the heart itself is normal.

Athletic training changes the ECG in ways that overlap with disease, and distinguishing the two is a recognised specialty in its own right. Ancestry matters here: T wave inversion across the front chest viewpoints is a well-described normal finding in athletes of African or Caribbean ancestry, and considerably more concerning in others.

What Usually Happens Next

The single most useful step is finding an old ECG. A pattern that has been present for a decade means something entirely different from one that appeared last month, and comparison answers the question faster than any new test.

If there is no previous tracing, or the pattern is new, the usual next steps depend on the picture. A troponin blood test checks whether heart muscle has been damaged. An echocardiogram looks at the muscle thickness and how well each area is moving, which can show a problem in the same territory the ECG pointed at.

Where the coronary arteries are the concern, a stress test or a CT coronary angiogram follows. Where the finding is unexplained in a young person, cardiac MRI is often used, because it shows the muscle in more detail than ultrasound can.

And in a great many cases none of this is needed, because the inversion sits in a viewpoint where it belongs and the conversation ends there.

Conclusion

T wave inversion describes the direction of a small wave on a tracing. That is genuinely all the phrase means, and in several viewpoints the downward direction is the normal one.

What turns it into something worth investigating is context: which viewpoints, whether it is new, and whether anything else is going on. Those are questions a person cannot answer from the report alone, and they are the right things to ask.

If you have been given this finding, two pieces of information will shape the conversation more than anything else. Whether an older ECG exists for comparison, and whether you have had any symptoms, particularly chest discomfort, in the weeks beforehand. Both are worth mentioning without being asked.

Related Reading