





The Pulse Newsletter Expert heart health, in plain English. Fortnightly, from our clinicians. Subscribe →
Section

Tests & Procedures

Being referred for a cardiac test can feel daunting, especially when you’re not sure what to expect. The Tests section explores the most common cardiac investigations — from ECGs and echocardiograms to stress tests and coronary angiograms. Each article explains what a test involves and what the results generally mean, written by cardiologists to help readers feel more informed going into their next appointment.

Jump to a topic
TAVI Explained: A New Aortic Valve Without Open Surgery
Latest in Tests & Procedures

TAVI Explained: A New Aortic Valve Without Open Surgery

A narrowed aortic valve once meant opening the chest and stopping the heart. TAVI implants a new valve through an artery in the groin, usually in one to two hours, with the patient awake. What the procedure involves, who it suits now, and how the choice between TAVI and surgery is made.

All articles
To Fast or Not to Fast Before a Blood Test?

To Fast or Not to Fast Before a Blood Test?

Should blood tests be done fasting? Only a few need it, chiefly glucose tests. Here is which heart-related tests require fasting, what counts as a fast, and why cholesterol usually does not.

Understanding Your Cholesterol Test: What Each Number Means

Understanding Your Cholesterol Test: What Each Number Means

A cholesterol result often arrives as a column of numbers and abbreviations with little explanation. Here is what each value measures, how the two international units compare, and why the right LDL level differs from person to person.

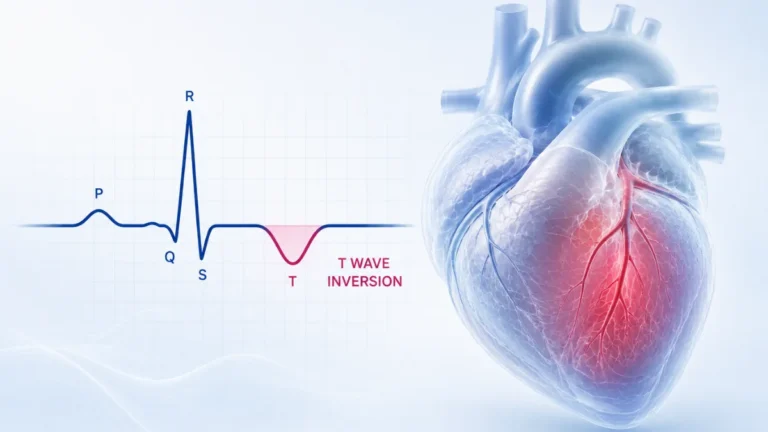
T Wave Inversion on Your ECG: What It Actually Means

T Wave Inversion on Your ECG: What It Actually Means

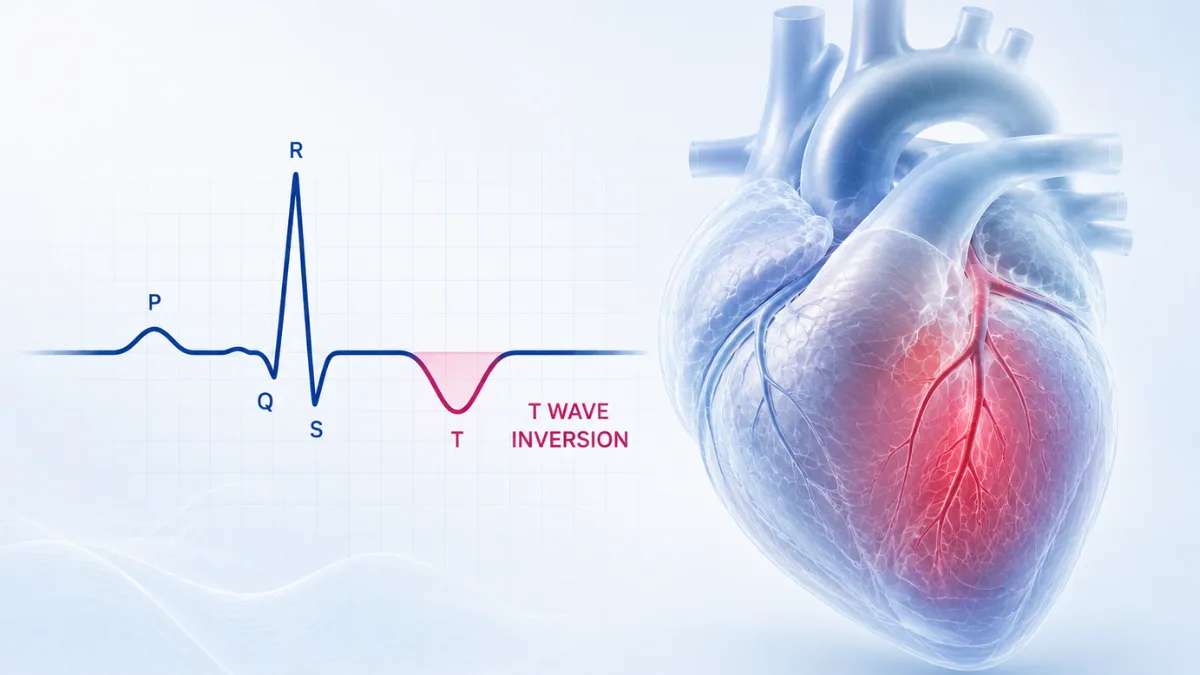
T wave inversion describes a small wave on the tracing pointing down instead of up. In several of the heart's twelve viewpoints that is completely normal. What matters is which ones, and whether it is new.

Left Ventricular Hypertrophy (LVH) on Your ECG

Left Ventricular Hypertrophy (LVH) on Your ECG

Left ventricular hypertrophy, or LVH, is commonly seen on ECG reports and often means less than it sounds. The tracing measures electrical signals, not muscle thickness. Here is what the finding describes and what usually settles it.

The Stress Echocardiogram: What to Expect

The Stress Echocardiogram: What to Expect

A stress echocardiogram combines an ultrasound of the heart with an exercise challenge, revealing how the heart performs under pressure, not just at rest.

ApoB Explained: What It Measures and Why LDL Still Matters

ApoB Explained: What It Measures and Why LDL Still Matters

ApoB is a cholesterol measurement gaining attention as a marker of heart risk. This article explains what it measures, how it relates to LDL cholesterol, and why triglycerides and lipoprotein(a) each remain part of a fuller, multifactorial picture.

Prof. Peter Barlis
Editor's note

Understanding your condition is the single most important thing you can do after a heart diagnosis. Don't just read — ask questions, take notes, bring them to your cardiologist.

Prof. Peter Barlis · Founding Editor, Heart Matters
What Is a Troponin Test, and Why Is It Used for Chest Pain?

What Is a Troponin Test, and Why Is It Used for Chest Pain?

Troponin is the blood test at the heart of chest pain assessment. If you have been to emergency with chest pain, here is what it measures and what the result means.

Right Bundle Branch Block (RBBB): Why It Sounds Worse Than It Usually Is

Right Bundle Branch Block (RBBB): Why It Sounds Worse Than It Usually Is

A right bundle branch block on your ECG may sound alarming, but in a healthy person, it is common and usually harmless. Here is what RBBB actually means, why it happens, and the smaller number of situations where it genuinely matters.

The Echocardiogram: What It Shows and Why It Matters

The Echocardiogram: What It Shows and Why It Matters

The echocardiogram is cardiology's most comprehensive non-invasive imaging test. Here is what it reveals about your heart and what to expect from the procedure.

Deep read

Recovering After a Coronary Angiogram: What to Expect

Most people are home within hours of a coronary angiogram, but knowing what to expect from the TR band, the results conversation, and the days after makes a real difference.

by Prof. Peter Barlis
Recovering After a Coronary Angiogram: What to Expect
CT Coronary Angiogram (CTCA): What It Is, What to Expect, and What It Shows

CT Coronary Angiogram (CTCA): What It Is, What to Expect, and What It Shows

The CT coronary angiogram gives a detailed view of the coronary arteries without any catheters, just a scan and a cannula. Here is what to expect from the procedure and how to interpret the results.

What Is a BNP Test? Understanding This Key Heart Failure Blood Test

What Is a BNP Test? Understanding This Key Heart Failure Blood Test

BNP and NT-proBNP are blood markers released when the heart is under strain — the primary tests used to diagnose and monitor heart failure. An elevated result is the beginning of an investigation, not a verdict.

The hs-CRP Test: Inflammation, Heart Risk, and Why Context Matters

The hs-CRP Test: Inflammation, Heart Risk, and Why Context Matters

The hs-CRP test measures inflammation in the blood — but it is not a diagnostic test for heart disease. Here is what it can and cannot tell us about cardiovascular risk.

Leadless Pacemakers: A New Era in Cardiac Pacing

Leadless Pacemakers: A New Era in Cardiac Pacing

Leadless pacemakers offer a promising alternative to traditional devices, no leads, no chest wound. Here's how they work.

Lipoprotein(a): The Inherited Heart Risk Most People Have Never Heard Of

Lipoprotein(a): The Inherited Heart Risk Most People Have Never Heard Of

Lp(a) is genetic, largely untreatable by standard medications, and affects one in five people, yet most have never had it measured. Here is what you need to know.

Drug-Coated Balloons: A New Frontier in Treating Coronary Artery Disease

Drug-Coated Balloons: A New Frontier in Treating Coronary Artery Disease

Drug-coated balloons treat coronary blockages by delivering medication directly to the artery wall, then are removed completely, leaving no metal behind.

12

TAVI Explained: A New Aortic Valve Without Open Surgery

TAVI
Key Points

  • A TAVI procedure implants a new aortic valve through a thin tube (catheter) passed up through an artery, usually in the groin. The chest is not opened and the heart keeps beating throughout.
  • TAVI and TAVR are two names for the same procedure. TAVI is the usual term in Europe, the UK, Australia and much of Asia, and TAVR in North America.
  • Who is offered TAVI now depends less on how risky surgery would be and more on age, the anatomy of the valve and arteries, and life expectancy. European guidelines published in 2025 recommend TAVI for most suitable people aged 70 or over, and surgery for most people under 70 who are at low risk from an operation.
  • A detailed CT scan is central to planning. It decides the type and size of the new valve and shows the best artery for access and the pathway to the heart.
  • The most common complication involves the heart’s electrical wiring. Up to about one in 10 people need a permanent pacemaker afterwards.
  • Most people are walking within a few hours and home from hospital within a few days.

Replacing a heart valve once meant opening the chest, stopping the heart and handing its work to a bypass machine. It was, and still is, an excellent operation. But many people with a narrowed valve were judged too old, too frail or too unwell to undergo such a large operation, and were left with very little to be offered.

Over the past two decades an alternative has emerged, and it is one of the biggest shifts in modern cardiology. A replacement valve, folded down to roughly the width of a pencil, travels to the heart through an artery and is opened inside the diseased valve while the heart carries on beating. Most people are awake, or lightly sedated, throughout.

If you or someone close to you has recently been told a valve is narrowed, this article explains what the procedure involves and how the choice between TAVI and surgery is usually made. It is background for the conversation with your own cardiologist, not a substitute for it.

What TAVI Is

TAVI stands for transcatheter aortic valve implantation. A catheter is a long, thin, flexible tube, and transcatheter means the whole procedure is done through that tube, rather than through a surgical opening.

TAVR, short for transcatheter aortic valve replacement, is exactly the same procedure under a different name. Which term you hear depends mostly on where you live. TAVI is standard in Europe, the UK, Australia and much of Asia, while TAVR is used in North America. This article uses TAVI, and everything in it applies equally to TAVR.

Strictly speaking, nothing is replaced. The diseased valve stays where it is, pressed outwards against the artery wall, and the new valve sits inside it. That detail matters more than it might seem, and it explains several points later in this article.

The new valve is made from treated animal tissue, from a cow or pig, sewn inside a collapsible metal frame. Crimped onto the end of the catheter, it is steered up through the arteries to the heart, with live X-ray images acting as a guide. Once it is in position inside the old valve, the frame is expanded. It pushes the stiff old leaflets aside, anchors itself in place and starts working straight away.

The Words You Will Hear

Valve clinics use some terms so often that staff can forget to explain them. Here is what they mean in plain English.

Aortic stenosis

The condition TAVI treats. The aortic valve is the doorway between the heart and the body’s main artery, the aorta. When the valve stiffens and narrows, the heart has to work harder to push blood through it.

Calcification

Hard calcium deposits build up in the valve over many years and make it thick and stiff. They come from wear and inflammation in the valve itself, not from calcium in the diet.

Leaflets

The thin flaps that make up the valve, opening and closing with every heartbeat, around 100,000 times a day. Most people have three (tricuspid), while some are born with two (bicuspid). In aortic stenosis they become too stiff to open fully.

The conduction system

The heart’s own electrical wiring, which sets the heartbeat. Part of it runs just below the aortic valve, so a new valve in that position can press on it.

Antiplatelet

A type of blood thinner that makes platelets, the tiny blood cells that start a clot, less sticky. Low-dose aspirin is the best-known example.

Anticoagulant

A stronger type of blood thinner that acts on the clotting proteins in the blood rather than on platelets. Warfarin and the newer direct oral anticoagulants (DOACs), such as apixaban and rivaroxaban, belong to this group.

Who TAVI Is Suitable For

Few things in valve medicine have changed as much as the answer to this question, and it is still changing.

TAVI started as a treatment for people with no other option, those judged too unwell to survive an operation. Trials then tested it in people at moderate risk from surgery and, later, in those at low risk. In the groups studied, results matched or improved on surgery.1,2 The question shifted from whether someone is well enough for an operation to which approach suits that person best.

The European guidelines published in 2025 recommend TAVI for people aged 70 or over whose valve has the usual three leaflets (tricuspid) and whose arteries for access are suitable, whatever their surgical risk. Surgery remains the recommended choice for most people under 70 who are at low risk from an operation, and for many people born with a two-leaflet (bicuspid) valve.3 American guidelines draw a broader band. Surgery is generally favoured under 65 and TAVI over 80, with either considered reasonable in between and the choice made case by case.4

When deciding how someone’s aortic stenosis should be treated, the heart team weighs up many things:

  • How many years the new valve needs to last, and what will happen when it eventually wears out.
  • Whether the arteries in the legs and pelvis are wide and clear enough for the delivery tube to pass through.
  • The anatomy of the valve and where the calcium sits. Some anatomies are less well suited to a transcatheter approach, or may not offer the same durability.
  • Whether other heart problems need fixing at the same time. Someone who also needs bypass grafting or another valve repaired is usually better served by a single operation.
  • Frailty and other medical conditions, which affect recovery from open surgery far more than recovery from TAVI.

Because so much of this turns on individual anatomy, two people of the same age can be offered different things for good reasons. Where that choice sits for any one person is worth going through carefully with the treating cardiologist.

One more change in the 2025 European guidelines affects people with severe aortic stenosis who have no symptoms yet. Until recently they were usually monitored and treated only once symptoms appeared. The guidelines now say early treatment should be considered for many of them, provided the risk of the procedure is low.3 This follows a trial in which early TAVI reduced a combined measure of death, stroke and unplanned heart-related hospital stays. The benefit came mainly from fewer hospital admissions, with little difference in deaths over the period studied.5

The Assessment Beforehand

Planning a TAVI takes more work than the procedure itself, and it is where most of the important decisions are made.

An echocardiogram, an ultrasound scan of the heart, confirms how severe the aortic stenosis is and shows how well the heart muscle is coping. A CT scan with contrast dye then does the detailed work. It measures the valve to a fraction of a millimetre, which decides the size of the new valve, and maps the arteries from the groin upwards to check they can take the delivery tube. In many people the same scan can also check the arteries that supply the heart muscle, which may avoid a separate coronary angiogram.

Getting the size right matters. A valve that is slightly too small can leak around its edges. One that is slightly too large presses harder on the electrical wiring just below the valve, which raises the chance of needing a pacemaker.

An ECG, a tracing of the heart’s electrical activity, is also checked carefully. Existing wiring problems are among the strongest predictors of needing a pacemaker afterwards.

A dental check is usually arranged too, because untreated dental infection can spread to a newly implanted valve.6

The results then go to a heart team meeting, where interventional cardiologists, cardiac surgeons, imaging specialists and other specialists such as geriatricians review the case together. The meeting is not there to rubber-stamp a decision already made. Its job is to work out whether TAVI, surgery or continued monitoring suits this person best, taking their own wishes into account.
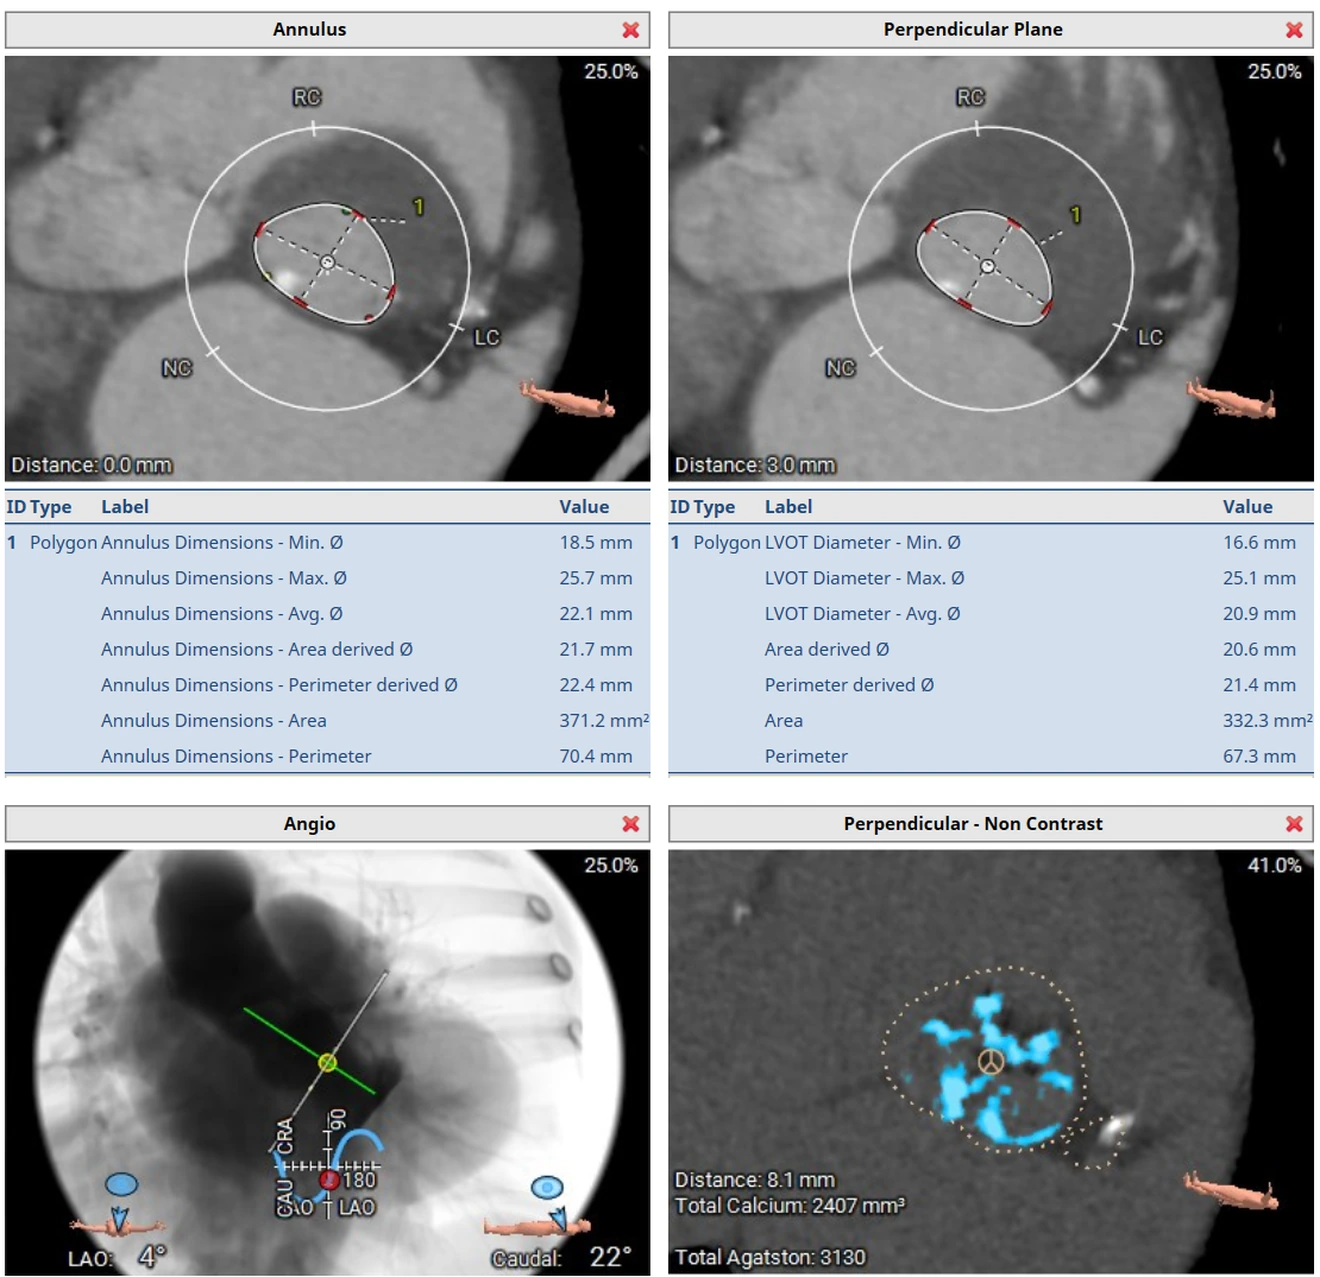
CT planning images for a TAVI. The upper panel shows the aortic valve opening measured in two planes with the dimensions listed. The lower panel shows the X-ray camera angle chosen for the procedure and a map of the calcium in the valve.
Figure 1. Part of the CT planning for a TAVI. Top: the valve opening measured in two planes, which sets the size of the new valve. Bottom: the camera angle chosen for the procedure, and a map of the calcium in the valve shown in blue. Images courtesy of Dr Amanda Sherwen.
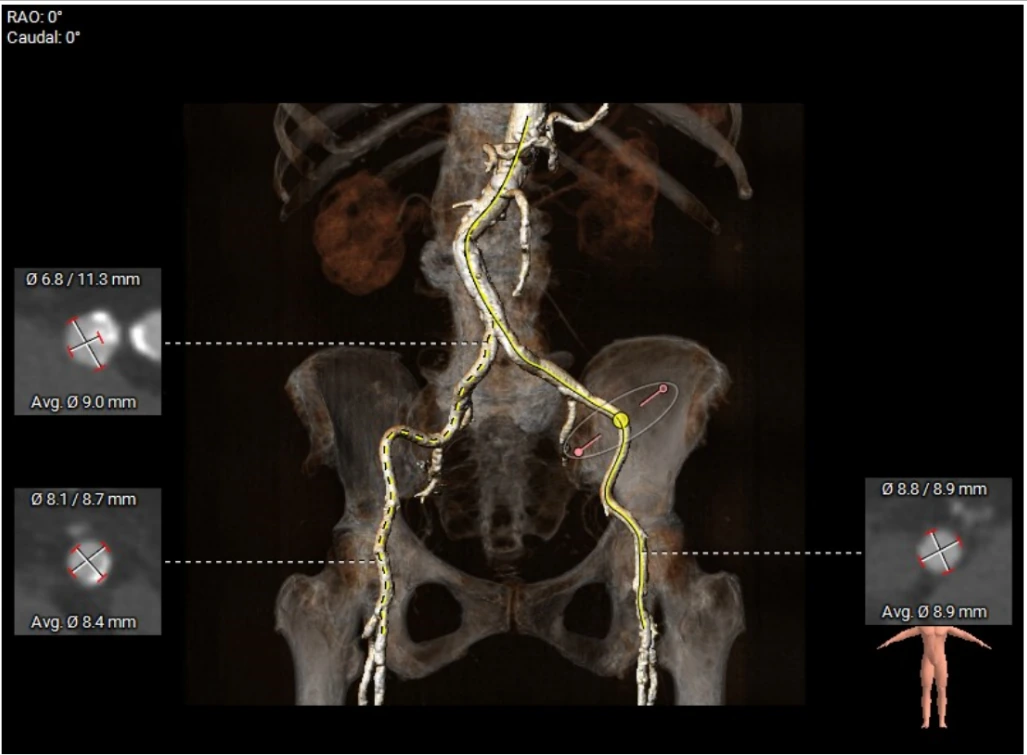
Three-dimensional CT reconstruction of the aorta and the arteries of the pelvis and legs, with the width of the artery measured at three points along the route.
Figure 2. The same CT scan follows the arteries from the groin up to the heart, measuring their width along the way (shown here at three points). This is what decides whether the valve can be delivered through the leg, and which side offers the better route. Images courtesy of Dr Amanda Sherwen.

The Procedure Itself

Most TAVI procedures take one to two hours.

Most are done through the femoral artery, the large artery at the top of the leg, using a small puncture rather than a cut. If those arteries are too narrow or diseased, the valve can be delivered through an artery below the collarbone or in the neck, or directly through the chest wall, but only a minority of people need these routes.

In the early years, TAVI was done under general anaesthetic. Today it is often done under local anaesthetic with sedation, so the person is drowsy but breathing on their own. This speeds up recovery and lowers the risk of confusion that a general anaesthetic can cause in older people.

With the catheter in place, the new valve is expanded inside the old one. Some designs are opened with a balloon, while others open on their own as they are released from the delivery system. This part takes only moments. The new valve is checked straight away with ultrasound and pressure readings before the equipment is removed and the femoral artery is closed.

Three X-ray images in sequence during a TAVI. First the new valve crimped on the catheter and positioned across the diseased valve, then the balloon inflated with the metal frame opening out, then the valve anchored in position with the balloon removed.
Figure 3. The moment of deployment, seen on live X-ray, in sequence. First, the new valve, crimped down on the catheter, is positioned across the diseased valve. Next, the balloon is inflated and the metal frame opens out. Finally, the balloon is removed and the new valve is anchored and working. The whole sequence takes well under a minute. Images courtesy of Dr Amanda Sherwen.

What to expect on the day

Time in the lab

Usually one to two hours.

Anaesthetic

Most commonly sedation with local anaesthetic, so awake but drowsy.

Access point

A puncture at the top of the leg in most cases, not a surgical cut.

Up and about

Sitting up within hours, walking the same day or the next morning.

Hospital stay

Two to three days is typical.

Monitoring after

Heart rhythm watched closely for the first day or two, and an echocardiogram before going home.

A procedure that once required opening the chest and stopping the heart is now routinely performed through a puncture in the groin, on a patient who is awake.

Recovery

Most people are sitting up within a few hours and walking the same day or the next morning. A hospital stay of two to three days is typical, and some centres send selected patients home sooner.

The improvement can be immediate and dramatic. Breathlessness that has been building for months often eases within days, because the blockage the heart was straining against has been removed.

For the first week or two, the main restrictions are about letting the groin heal rather than protecting the heart, so heavy lifting and strenuous exercise are usually limited. After that, activity generally builds back quickly. Many people are offered cardiac rehabilitation, a supervised programme of exercise and education, to help them return to normal life.

The Risks Worth Understanding

TAVI is a well-established procedure with a strong safety record, and serious complications are uncommon. A few are worth knowing about in advance, because understanding them makes the conversation about whether to go ahead a more useful one.

Needing a pacemaker

The most common complication. The new valve sits right against the heart’s wiring, and pressure on it can permanently slow the electrical signal. A pacemaker corrects this.

Stroke

Small fragments from the hardened valve can break off and travel to the brain. In current practice this happens to about two in every 100 people in the first month.

Problems at the groin

Bleeding or damage where the artery was entered. This is less common than in the early years, because the tubes used are now much narrower.

8 to 10%
of people need a permanent pacemaker after TAVI. The rate varies with the type of valve and with any conduction system problems present beforehand.
US national TVT registry
4 to 6%
need one after surgical valve replacement. This is the main trade-off between the two approaches.
PARTNER 3 and Evolut Low Risk trials

Sources: US national TVT registry7 and the low-risk trials.1,2

One further issue comes from the old valve staying in place. Because the new frame sits inside a rigid ring of calcium, small gaps can remain around its edge and let blood leak around the outside of the valve. Newer valves with sealing skirts have greatly reduced this. Small leaks usually cause no problems, but larger ones matter, so the team checks for them before the procedure ends.

Medicines Afterwards

Thinking on this has changed a lot, and in a direction that surprises people who assume more protection is always better.

Two kinds of blood thinner come up here, and they are easy to confuse. Antiplatelets, such as low-dose aspirin, make the tiny cells that start a clot less sticky. Anticoagulants, such as warfarin or one of the newer DOACs, act on the clotting proteins in the blood and are the stronger of the two.

For people with no other reason to take a blood thinner, a single antiplatelet tablet, taken long term, is now the standard after TAVI. A large trial compared aspirin alone with aspirin plus a second antiplatelet. The two-drug group had considerably more bleeding, with no fewer strokes or heart attacks to make up for it.8

Routine anticoagulation is not used either. A trial that gave a DOAC to people with no other reason to take one was stopped early, after more deaths, more clotting events and more bleeding in that group. Guidelines now advise against it.9

People who need an anticoagulant for another reason, most commonly atrial fibrillation, keep taking it. For most of them, adding an antiplatelet on top does more harm than good, mainly through extra bleeding.10 Across the field, the trend has been towards fewer blood thinners, not more.

Which of these medicines is right for a particular person, and for how long, is a decision for their own doctor, because it depends on their other health conditions as well as the valve.

How Long the Valve Lasts

This is TAVI’s main limitation, and it is the reason age still shapes the decision.

Transcatheter valves are made of tissue, and tissue valves wear out over time. Trials have now followed people for up to 10 years, and over that period the valves perform much like surgical tissue valves.11 What does not exist yet is the 15 and 20 year evidence available for surgery, because TAVI has not been widely used for long enough.

For someone in their eighties, this is mostly a theoretical concern. For someone in their sixties, it is central, because it raises the question of what happens when the valve wears out. A second valve can often be placed inside the first, although whether that is possible depends on the size and design of the original. Planning that sequence from the start, rather than treating the first procedure as the end of the story, is now a routine part of the discussion.

Follow-up is simple. Regular ultrasound scans check how the valve is working, and any wear is usually picked up well before it causes symptoms. Good dental care matters more than ever, as it does with any artificial valve, because infection in the bloodstream can settle on the new valve.

Questions People Often Bring to the Heart Team

Being offered a choice between two good treatments can feel harder than being told there is only one. These are among the questions people most often raise when they sit down with their cardiologist or surgeon, and they tend to make the discussion a more productive one.

  • Given my age and my anatomy, what would you expect this valve to need in 10 or 15 years?
  • Is my valve tricuspid or bicuspid, and does that change what you would recommend?
  • What did the CT show about the arteries in my legs?
  • What is my own chance of needing a pacemaker, rather than the average?
  • If I choose to wait, what would you be watching for, and how often?

Heart Matters Resource

When in Doubt, Get Checked Out

Breathlessness on exertion, chest tightness, or feeling faint with activity are the symptoms that most often point to a narrowed aortic valve, and they are the ones that usually prompt medical assessment.

Read: When in Doubt, Get Checked Out →

Conclusion

TAVI has changed what is possible for people with aortic stenosis, and the change has been greatest for those who once had no treatment option at all. A procedure lasting an hour or two, done through the groin while the person is awake, now achieves what once required opening the chest.

TAVI has not made surgery obsolete. Anatomy, age, other heart problems and how long the valve needs to last still point some people towards an operation. What has changed is that, for many people, there is now a real choice between two good options, worked through by a heart team together with the patient. If that is the position you find yourself in, the questions above are a reasonable place to start, and your own cardiologist is the person best placed to answer them.

References and sources
  1. Mack MJ, Leon MB, Thourani VH, et al. Transcatheter aortic-valve replacement with a balloon-expandable valve in low-risk patients (PARTNER 3). N Engl J Med. 2019;380(18):1695-1705.
  2. Popma JJ, Deeb GM, Yakubov SJ, et al. Transcatheter aortic-valve replacement with a self-expanding valve in low-risk patients (Evolut Low Risk). N Engl J Med. 2019;380(18):1706-1715.
  3. Praz F, Borger MA, Lanz J, et al. 2025 ESC/EACTS Guidelines for the management of valvular heart disease. Eur Heart J. 2025. doi:10.1093/eurheartj/ehaf194
  4. Otto CM, Nishimura RA, Bonow RO, et al. 2020 ACC/AHA Guideline for the management of patients with valvular heart disease. Circulation. 2021;143(5):e72-e227.
  5. Généreux P, Schwartz A, Oldemeyer JB, et al. Transcatheter aortic-valve replacement for asymptomatic severe aortic stenosis (EARLY TAVR). N Engl J Med. 2025;392(3):217-227.
  6. Delgado V, Ajmone Marsan N, de Waha S, et al. 2023 ESC Guidelines for the management of endocarditis. Eur Heart J. 2023;44(39):3948-4042.
  7. Carroll JD, Mack MJ, Vemulapalli S, et al. STS-ACC TVT Registry of transcatheter aortic valve replacement. J Am Coll Cardiol. 2020;76(21):2492-2516.
  8. Brouwer J, Nijenhuis VJ, Delewi R, et al. Aspirin with or without clopidogrel after transcatheter aortic-valve implantation (POPular TAVI, cohort A). N Engl J Med. 2020;383(15):1447-1457.
  9. Dangas GD, Tijssen JGP, Wöhrle J, et al. A controlled trial of rivaroxaban after transcatheter aortic-valve replacement (GALILEO). N Engl J Med. 2020;382(2):120-129.
  10. Nijenhuis VJ, Brouwer J, Delewi R, et al. Anticoagulation with or without clopidogrel after transcatheter aortic-valve implantation (POPular TAVI, cohort B). N Engl J Med. 2020;382(18):1696-1707.
  11. Thyregod HGH, Jørgensen TH, Ihlemann N, et al. Transcatheter or surgical aortic valve implantation: 10-year outcomes of the NOTION trial. Eur Heart J. 2024;45(13):1116-1124.

Related Reading

To Fast or Not to Fast Before a Blood Test?

blood test
Key Points

  • Most heart-related blood tests do not require fasting. Fasting matters most for the fasting glucose and glucose tolerance tests, and is often recommended for cholesterol tests, particularly when triglycerides are measured.
  • Fasting is often recommended before a cholesterol panel, because meals raise triglycerides and fasting keeps results consistent between tests. A normal meal changes LDL and HDL cholesterol only slightly, so a non-fasting sample is acceptable for many routine checks.
  • The HbA1c test, which reflects average blood glucose over the previous two to three months, does not require fasting.
  • When fasting is needed, it usually means no food or drinks other than water for 8 to 12 hours. Exact instructions vary between laboratories.
  • Fasting can cause low blood sugar in people taking insulin or some diabetes tablets, which is why they are usually given specific instructions before a fasting test.

Few instructions cause as much confusion as “fast before your blood test.” Does black coffee count? What about morning tablets? And why does one cholesterol test come with fasting instructions while the next does not?

The short answer is that fasting matters a great deal for a few tests, matters in particular situations for cholesterol, and makes very little difference for most others. Knowing which is which can spare an uncomfortable morning and, for some people, avoid a genuine risk.

Why Food Affects Some Blood Tests

After a meal, sugars and fats from food pass into the bloodstream. For a few hours, the levels of some substances in the blood rise, while others barely change.

Glucose (blood sugar) and triglycerides are the two most affected. A test designed to measure a “resting” level of either can be misleading if taken soon after eating. Most other routine blood tests are affected so little by a normal meal that fasting makes no practical difference.

Which Heart-Related Tests Need Fasting?

The table below shows how fasting requirements typically apply to common blood tests in heart care. Individual laboratories may set their own requirements, and the instructions given with a test request take priority.

Test Fasting Usually Needed? Why
Fasting glucose Yes Food raises blood glucose for several hours
Glucose tolerance test Yes Measures the response to a standard glucose drink from a fasting start
HbA1c No Reflects average glucose over months, not today’s meals
Cholesterol panel, including triglycerides Often recommended Meals raise triglycerides, and fasting keeps results comparable from one test to the next
Iron studies Sometimes Some laboratories prefer a morning sample, as iron levels vary
Troponin and BNP No Often urgent, and not meaningfully affected by food
INR, kidney function, hs-CRP Usually not Routine checks are generally done without fasting

Tests used to assess chest pain or heart strain, such as troponin and BNP, are taken whenever they are needed, often in an emergency department. Fasting plays no part in them.

Routine monitoring tests, such as the INR used for people taking warfarin and the hs-CRP test, are generally done without fasting. For iron studies, used to check for iron deficiency, some laboratories prefer a morning sample because iron levels in the blood vary through the day.

Glucose Tests and Fasting

Blood glucose tests are where fasting matters most. They are used to check for diabetes and prediabetes, both important risk factors for heart disease.

Fasting glucose

A fasting glucose test measures blood sugar after a period without food. The American Diabetes Association defines fasting as no calorie intake for at least 8 hours. An overnight fast with a morning test is the usual arrangement.

Eating before this test can push the result into a range that looks like diabetes when it is not. That is why a fasting glucose result taken after breakfast cannot be interpreted in the usual way.

Glucose tolerance test

The oral glucose tolerance test shows how well the body clears sugar from the blood. After an overnight fast, a blood sample is taken, a standard drink containing 75 g of glucose is given, and a second sample is taken two hours later. The test takes a couple of hours in total and is commonly used in pregnancy.

HbA1c

The HbA1c test measures how much glucose has attached to red blood cells over the previous two to three months. Because it reflects a long-term average, a meal beforehand has no meaningful effect, and no fasting is needed.

HbA1c is reported in two ways around the world: as a percentage, or in millimoles per mole (mmol/mol). A result of 6.5% is the same as 48 mmol/mol.

Glucose results in both units

Glucose is reported in mmol/L in many countries and in mg/dL in others, including the United States. A result in mmol/L multiplied by 18 gives the value in mg/dL. The table shows the levels the American Diabetes Association uses to define diabetes.

Test Fasting? Diabetes Range (mmol/L) Diabetes Range (mg/dL)
Fasting glucose Yes 7.0 or higher 126 or higher
Glucose tolerance test (2 hours) Yes 11.1 or higher 200 or higher
Random glucose, with symptoms No 11.1 or higher 200 or higher

The range for prediabetes differs between organisations. The American Diabetes Association uses a fasting glucose of 5.6 to 6.9 mmol/L (100 to 125 mg/dL), while the World Health Organization uses 6.1 to 6.9 mmol/L (110 to 125 mg/dL). Unless a result is clearly abnormal, a diagnosis of diabetes is usually confirmed with a second test, and interpreting results is a matter for the requesting doctor.

Cholesterol Tests: When Fasting Helps

Cholesterol tests were traditionally done after fasting. A joint consensus statement from the European Atherosclerosis Society and the European Federation of Clinical Chemistry and Laboratory Medicine reviewed large studies comparing fasting and non-fasting results.

After normal meals, triglycerides rose by up to about 0.3 mmol/L (26 mg/dL), while total and LDL cholesterol fell by about 0.2 mmol/L (8 mg/dL). HDL cholesterol and lipoprotein(a) were not affected. Non-fasting results predicted heart disease risk just as well as fasting ones, so the statement recommends non-fasting samples for routine testing.

Why triglycerides are different

Triglycerides are the part of the cholesterol panel most affected by food. The average rise after a meal is small, but it can be much larger after a fatty meal, and in people with diabetes, excess abdominal weight, or already raised triglycerides.

This matters for LDL cholesterol too. In most laboratories, LDL is calculated from the other values, including triglycerides. The higher the triglyceride level, the less accurate that calculation becomes.

For these reasons, American guidelines state that a fasting sample is most helpful in several situations:

  • When triglycerides have been high before, particularly above 4.5 mmol/L (400 mg/dL).
  • When high triglycerides are being diagnosed or monitored.
  • When there is a family history of early heart disease or an inherited cholesterol disorder.
  • When checking how much risk remains for a person already on cholesterol-lowering treatment.

European guidance suggests a fasting repeat when a non-fasting triglyceride level is above 5 mmol/L (440 mg/dL). In everyday practice, many doctors request a fasting sample for cholesterol tests, particularly when triglycerides are part of the question. When a test request asks for fasting, that instruction is the one that applies.

I usually recommend fasting before a cholesterol test. I often request a full panel, including glucose and triglycerides, and fasting keeps results consistent, which makes monitoring over time more reliable.

Prof. Peter Barlis, Interventional Cardiologist

What Counts as Fasting?

Definitions vary. The American Diabetes Association uses at least 8 hours without calories, while European laboratory guidance recommends 12 hours. Water is permitted in both, and many laboratories encourage it, as good hydration can make blood easier to draw.

European laboratory guidance also advises against alcohol for 24 hours beforehand, and against coffee, tea, and smoking on the morning of the test. Chewing gum can affect some results too. Because practice differs between countries and laboratories, the instructions supplied with the test are the most reliable guide.

Medicines and Fasting

Advice about medicines on the morning of a fasting test varies. Most regular heart medicines are commonly taken as normal with water, but some laboratories and doctors ask for particular medicines to be delayed until after the sample. The requesting doctor or laboratory gives instructions for each person.

People with diabetes need particular care. Insulin and some diabetes tablets can cause low blood sugar when a meal is skipped, which can lead to shakiness, sweating, confusion, or fainting. For this reason, people taking these medicines are usually given specific instructions about timing their medicine and the test, and tests are often booked early in the morning.

Conclusion

Fasting matters for a small number of blood tests, chiefly the fasting glucose and glucose tolerance tests. For cholesterol tests, fasting is often recommended because it gives a clearer and more consistent triglyceride result, although a non-fasting sample is acceptable for many routine checks. For most other heart-related tests, including HbA1c, fasting makes little or no difference.

When fasting is required, the instructions that come with the test request are the best guide, and questions about medicines are worth raising with the requesting doctor or laboratory beforehand. A few minutes of clarification can prevent a wasted trip or an unreliable result.

Related Reading

Understanding Your Cholesterol Test: What Each Number Means

cholesterol test
Key Points

  • A standard cholesterol test, often called a lipid profile, measures several different fats in the blood. LDL cholesterol is the number most closely linked to heart attack and stroke risk.
  • There is no single “normal” LDL level that suits everyone. The goal depends on each person’s overall cardiovascular risk, and a result flagged as normal on a lab report may still be above the goal for someone with heart disease.
  • Results are reported in one of two units depending on the country and laboratory: millimoles per litre (mmol/L) or milligrams per decilitre (mg/dL). The same result looks very different in each.
  • Lipoprotein(a) is the exception. Its two units, mg/dL and nmol/L, cannot be converted reliably, so the result is best read in the unit the laboratory used.
  • For most routine tests, fasting beforehand is not required.

A cholesterol result often arrives as a column of numbers, a few abbreviations, and perhaps an asterisk. What it rarely includes is an explanation. One figure may be flagged high, another low, and it is not always clear which matter most.

This guide explains what each part of a standard cholesterol test measures, how the two international units work, and why the right number for one person can be quite different from the right number for another.

Why Cholesterol Matters

Cholesterol is a waxy fat the body needs to build cells and make hormones. It travels in the blood inside particles called lipoproteins. Some of these particles can lodge in artery walls, where they build up over many years into the fatty plaque of atherosclerosis.

That plaque narrows arteries and can rupture, triggering a heart attack or stroke. The more of these particles in the blood, and the longer they are there, the greater the build-up. This is why cholesterol testing sits at the centre of heart disease prevention.

What a Cholesterol Test Measures

A standard lipid profile usually reports four or five values. Some laboratories add others, such as lipoprotein(a) or apolipoprotein B, when requested.

The numbers on a cholesterol report
LDL cholesterol
The main driver of plaque build-up. The number most treatment goals are based on.

HDL cholesterol
Carries cholesterol away from the arteries. Low levels are linked to higher risk.

Triglycerides
A different type of blood fat, influenced by diet, alcohol, weight, and diabetes.

Total cholesterol
All cholesterol combined. Useful for calculations, less useful on its own.

Non-HDL cholesterol
Total minus HDL. Captures all the particles that can form plaque.

Lipoprotein(a)
An inherited particle, usually measured once in a lifetime rather than routinely.

LDL cholesterol

LDL (low-density lipoprotein) cholesterol is the most important number on the report. Large genetic studies and clinical trials consistently show that lower LDL levels mean less plaque and fewer heart attacks and strokes. Most treatment decisions are built around it.

In many laboratories LDL is calculated from the other values rather than measured directly. The calculation is less accurate when triglycerides are very high or LDL is very low, which is why some laboratories measure it directly in those situations.

HDL cholesterol

HDL (high-density lipoprotein) cholesterol helps carry cholesterol away from artery walls. Low HDL levels are linked to higher cardiovascular risk. However, medicines that raise HDL have not, on their own, been shown to reduce heart attacks in trials, and HDL is not a treatment goal in major guidelines.

Triglycerides

Triglycerides are the body’s main store of fat. Levels are influenced by diet, alcohol, body weight, diabetes, and some medicines. Raised triglycerides add to cardiovascular risk, and very high levels can also inflame the pancreas.

Non-HDL cholesterol

Non-HDL cholesterol is total cholesterol minus HDL. It captures every type of particle that can contribute to plaque, not only LDL. Both European and American guidelines use it as a secondary goal, particularly for people with raised triglycerides or diabetes.

Two Units, One Result

Cholesterol results are reported in one of two units, depending on the country and the laboratory. Much of the world, including the UK, Canada, Australia, and New Zealand, uses millimoles per litre (mmol/L). The United States and a number of other countries use milligrams per decilitre (mg/dL).

The same blood sample gives very different-looking numbers in each unit. An LDL of 2.6 mmol/L is the same as 100 mg/dL. Knowing which unit a report uses is the first step in making sense of it, and the unit is usually printed beside each value.

For cholesterol values (total, LDL, HDL, and non-HDL), a result in mmol/L multiplied by about 38.7 gives the value in mg/dL. Triglycerides use a different factor, about 88.6, because they are a different molecule. Throughout this article, mmol/L is given first, with mg/dL in brackets.

Lipoprotein(a) is the exception

Lipoprotein(a), often written Lp(a), is reported either in mg/dL or in nanomoles per litre (nmol/L). Unlike cholesterol, there is no reliable way to convert between these units, because Lp(a) particles vary in size from person to person.

The guidelines themselves show the difficulty. European guidelines treat an Lp(a) above 50 mg/dL (105 nmol/L) as a risk-enhancing factor, while American guidelines treat 50 mg/dL (125 nmol/L) as the equivalent threshold. An Lp(a) result is therefore best read in the unit the laboratory reported, without converting it.

Why There Is No Single “Normal” Number

Laboratory reports usually print a reference range beside each result. This range describes typical values in the general population. It does not describe the right level for any particular person.

Guidelines set LDL goals according to overall cardiovascular risk. That risk takes into account age, blood pressure, smoking, diabetes, kidney function, family history, and whether heart or artery disease is already present. The higher the risk, the lower the LDL goal.

This is why an LDL of 2.5 mmol/L (97 mg/dL) might be flagged as normal on a report, yet sit well above the goal for someone who has had a heart attack. The table below shows the goals used in European guidelines. American guidelines use closely matching goals for most risk groups.

Risk Level LDL Goal (mmol/L) LDL Goal (mg/dL)
Very high Below 1.4 Below 55
High Below 1.8 Below 70
Moderate Below 2.6 Below 100
Low Below 3.0 Below 116

Most people who have had a heart attack, a stent, or a stroke fall into the very high risk group. European guidelines also recommend that people in the high and very high risk groups reduce their LDL by at least half from their starting level. Which risk group applies to an individual, and what their goal should be, is a judgement for their own doctor.

Preparing for the Test

For most routine cholesterol tests, fasting is not required. A meal before the test has only a small effect on most values, although triglycerides rise a little after eating. A fasting sample is sometimes requested when triglycerides are high or when an earlier result needs checking.

Cholesterol levels also vary naturally from one test to the next. An illness in the weeks before the test, a significant change in diet, or a change in medicines can all shift results. For this reason, doctors usually look at the trend across several tests rather than reacting to a single figure.

What Happens After the Result

When LDL is above a person’s goal, the first step is usually a look at overall risk and lifestyle. Diet plays a real but often modest role. Eating patterns rich in unsaturated fats and fibre help, and some foods affect blood cholesterol less than commonly assumed, as the evidence on eggs and cholesterol shows.

Where medicines are needed, statins are the foundation of treatment. Ezetimibe is commonly added when a statin alone does not reach the goal, and PCSK9 inhibitors are an option for people at the highest risk. A repeat test after starting or changing treatment shows how well it is working.

A cholesterol result means little on its own. It becomes meaningful when read alongside a person’s overall risk.

Conclusion

A cholesterol test is one of the most useful blood tests in heart health, but the numbers only make sense in context. LDL cholesterol matters most, the unit on the report changes how every figure looks, and the right goal depends on each person’s overall risk rather than a single normal range.

For anyone unsure what their own results mean, the report is worth discussing with their doctor or cardiologist, ideally alongside their other risk factors. That conversation turns a column of numbers into a plan.

Related Reading

T Wave Inversion on Your ECG: What It Actually Means

T wave inversion
Key Points

  • An ECG records the heart from twelve different viewpoints. After each beat the heart resets, and that recovery shows on the tracing as a rounded wave called the T wave.
  • In most viewpoints that wave points upwards. When it points downwards instead, the report describes it as T wave inversion.
  • In several viewpoints a downward T wave is entirely normal and expected, so the phrase on its own says very little.
  • What determines whether it matters is which viewpoints are involved, whether it is new compared with a previous tracing, and whether there are any symptoms.
  • A previous ECG, if one exists, is often the single most useful piece of information, because a longstanding pattern and a new one carry very different weight.

Of all the phrases that turn up on an ECG report, T wave inversion is among the most common and the least self-explanatory. It sounds like something has been reversed, or has gone wrong in a way that ought to be obvious.

What it describes is narrower than that. A small wave on the tracing points downwards instead of upwards. In several of the heart’s twelve viewpoints that is completely normal. In others it can be important. The phrase alone does not tell you which situation you are in.

What the T Wave Is

Each heartbeat has two halves. The heart muscle activates and contracts, then it has to reset electrically before it can do it again.

On an ECG tracing, the tall spike is the contraction. The rounded wave that follows it is the reset. That second wave is the T wave.

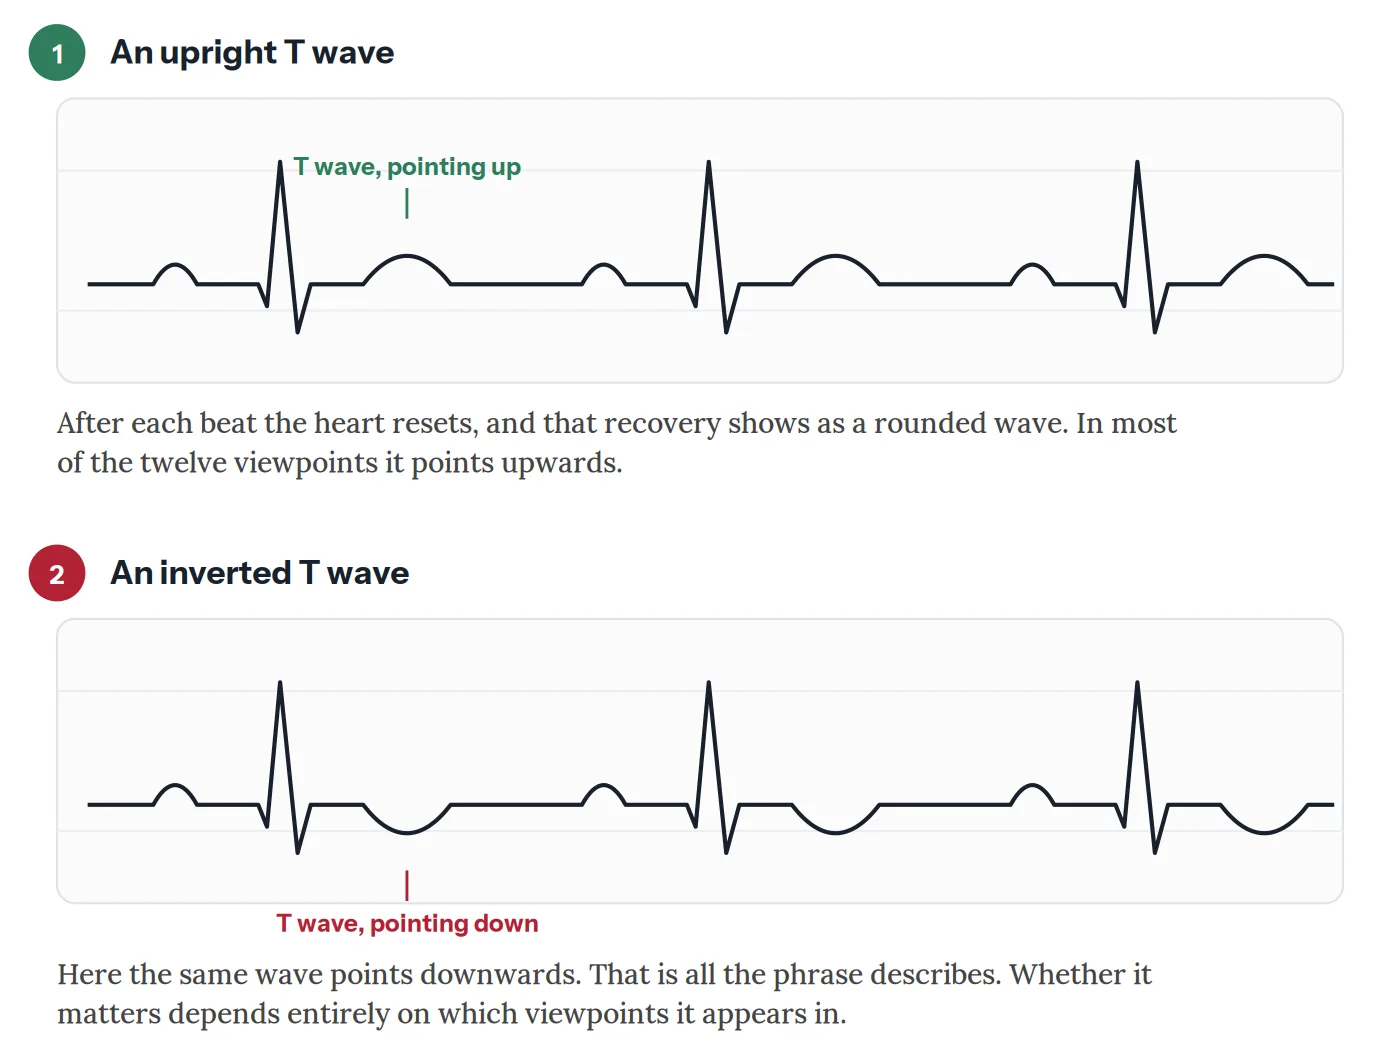
Two ECG tracings compared. In the first the T wave after each beat points upwards, which is the usual pattern in most leads. In the second the T wave points downwards, which is what a report means by T wave inversion
The difference is simply which way the recovery wave points. Whether that matters depends on which of the heart’s twelve viewpoints it appears in, Heart Matters

Because the twelve viewpoints look at the heart from different angles, the same electrical recovery appears differently in each. In most of them the T wave points upwards. In a few it normally points down, and always has.

Where a Downward T Wave Is Simply Normal

This is the part that resolves most people’s concern, and it is worth stating plainly.

One viewpoint, the one labelled aVR, has a downward T wave in essentially everybody. It looks at the heart from the opposite direction to the others, so an upward wave there would be the abnormal finding.

Two others, V1 and lead III, very commonly show a downward T wave in healthy people. So does lead V2 in some. An automated report will still flag these, because software counts rather than interprets.

There is also a pattern sometimes called the persistent juvenile pattern. Children normally have downward T waves across several of the chest viewpoints, and in most people these turn upward through adolescence. In some adults, more often women and more often people of African or Caribbean ancestry, the childhood pattern simply persists. It is a normal variant, not a disease.

In some viewpoints a downward T wave is the expected finding. The software flags it anyway, because it counts rather than interprets.

What Determines Whether It Matters

Three questions decide almost everything, and a cardiologist works through them in this order.

Reassuring
Usually needs nothing beyond an explanation
  • The inversion sits only in aVR, V1, or lead III, where it is normal.
  • An older tracing shows the same pattern, unchanged over years.
  • There are no symptoms, and the rest of the ECG is normal.
  • The person is young, fit, and the pattern fits a recognised normal variant.
Worth explaining
Usually has a cause that is already known
  • The inversion accompanies a bundle branch block, where changed conduction alters the recovery wave as a matter of course.
  • It accompanies a thickened heart muscle, where the pattern is sometimes described as strain.
  • Certain medicines, including digoxin, change the shape of the recovery wave predictably.
  • Low potassium or magnesium can flatten or invert it, and correcting the level corrects the tracing.
Investigated promptly
The pattern, the symptoms, or the change over time raises concern
  • The inversion is new compared with a previous tracing.
  • It appears across several neighbouring viewpoints rather than one.
  • It is deep and symmetrical rather than shallow, particularly across the front of the heart.
  • There are symptoms, especially chest discomfort, breathlessness, or fainting.

The Pattern Cardiologists Look For First

There is one specific arrangement worth knowing about, because it is the reason this finding is never dismissed out of hand.

Deep, symmetrical T wave inversion across the viewpoints that look at the front of the heart, appearing in someone who has recently had chest pain that has since settled, can indicate a critical narrowing in the artery supplying that territory. The person often feels fine at the moment the tracing is taken, which is exactly what makes it dangerous.

It is uncommon. Most T wave inversion is nothing like this. But it is the reason a cardiologist will ask carefully about recent chest pain even when someone currently feels well, and why this particular pattern prompts prompt assessment of the coronary arteries rather than watchful waiting.

Other Causes Worth Knowing

Beyond the coronary arteries, several conditions change the recovery wave.

A previous heart attack leaves permanent changes in the viewpoints that looked at the damaged area, often alongside Q waves.

Thickened heart muscle, whether from long-standing high blood pressure or from hypertrophic cardiomyopathy, alters recovery across several viewpoints. In the inherited condition the changes can be striking, and they are one of the findings that prompts further imaging in a young person.

Inflammation of the heart muscle or its surrounding sac produces widespread changes rather than ones confined to a single artery’s territory.

A clot in the lungs can invert the T waves across the right-sided viewpoints, usually alongside breathlessness and a fast heart rate.

Conditions affecting the brain, including bleeding around it, can produce dramatic deep T wave inversion. These are sometimes called cerebral T waves, and the heart itself is normal.

Athletic training changes the ECG in ways that overlap with disease, and distinguishing the two is a recognised specialty in its own right. Ancestry matters here: T wave inversion across the front chest viewpoints is a well-described normal finding in athletes of African or Caribbean ancestry, and considerably more concerning in others.

What Usually Happens Next

The single most useful step is finding an old ECG. A pattern that has been present for a decade means something entirely different from one that appeared last month, and comparison answers the question faster than any new test.

If there is no previous tracing, or the pattern is new, the usual next steps depend on the picture. A troponin blood test checks whether heart muscle has been damaged. An echocardiogram looks at the muscle thickness and how well each area is moving, which can show a problem in the same territory the ECG pointed at.

Where the coronary arteries are the concern, a stress test or a CT coronary angiogram follows. Where the finding is unexplained in a young person, cardiac MRI is often used, because it shows the muscle in more detail than ultrasound can.

And in a great many cases none of this is needed, because the inversion sits in a viewpoint where it belongs and the conversation ends there.

Conclusion

T wave inversion describes the direction of a small wave on a tracing. That is genuinely all the phrase means, and in several viewpoints the downward direction is the normal one.

What turns it into something worth investigating is context: which viewpoints, whether it is new, and whether anything else is going on. Those are questions a person cannot answer from the report alone, and they are the right things to ask.

If you have been given this finding, two pieces of information will shape the conversation more than anything else. Whether an older ECG exists for comparison, and whether you have had any symptoms, particularly chest discomfort, in the weeks beforehand. Both are worth mentioning without being asked.

Related Reading

Left Ventricular Hypertrophy (LVH) on Your ECG

LVH on Your ECG: What Left Ventricular Hypertrophy Means
Key Points

  • “Left ventricular hypertrophy” on an ECG report means the tracing showed larger than usual electrical voltages, which can happen when the heart’s main pumping chamber has thickened. It is a suggestion, not a diagnosis.
  • The ECG measures electrical voltage rather than muscle thickness. It picks up a great deal well, but wall thickness is inferred rather than measured, so a normal ECG does not rule thickening out.
  • Body build affects the reading. Where there is less tissue between the heart and the electrodes, the voltages run higher with no thickening at all.
  • An echocardiogram settles the question, because it measures the muscle directly rather than inferring it from voltage.
  • Where genuine thickening is confirmed, the cause matters more than the finding. High blood pressure is by far the most common, and the thickening can partly reverse when the pressure is treated.

Among the phrases that automated ECG software generates, “left ventricular hypertrophy” is one of the more alarming to read. It sounds like a diagnosis of something structural and permanent. Hypertrophy means enlargement. Left ventricular means the main pumping chamber. Put together, it reads as though a machine has just told you your heart is abnormally big.

What the machine has actually done is add up some voltages and compare the total against a threshold. Whether that reflects anything real about your heart is a separate question, and one the ECG is not well equipped to answer.

What the Left Ventricle Does and Why It Thickens

The left ventricle is the chamber that pushes blood out to the entire body. It is the thickest-walled part of the heart because it does the most work.

Like any muscle, it responds to sustained extra load by getting thicker. If it has to push against higher pressure with every single beat, year after year, the wall builds up in response. That is left ventricular hypertrophy.

It is not a disease in itself. It is an adaptation, and the important question is always what it is adapting to.

What the ECG Can and Cannot Tell You

The ECG is a genuinely valuable test, and it is ordered as often as it is for good reason. It detects rhythm disturbances, conduction problems, and the changes of a heart attack quickly, cheaply and reliably. For those questions it is hard to better.

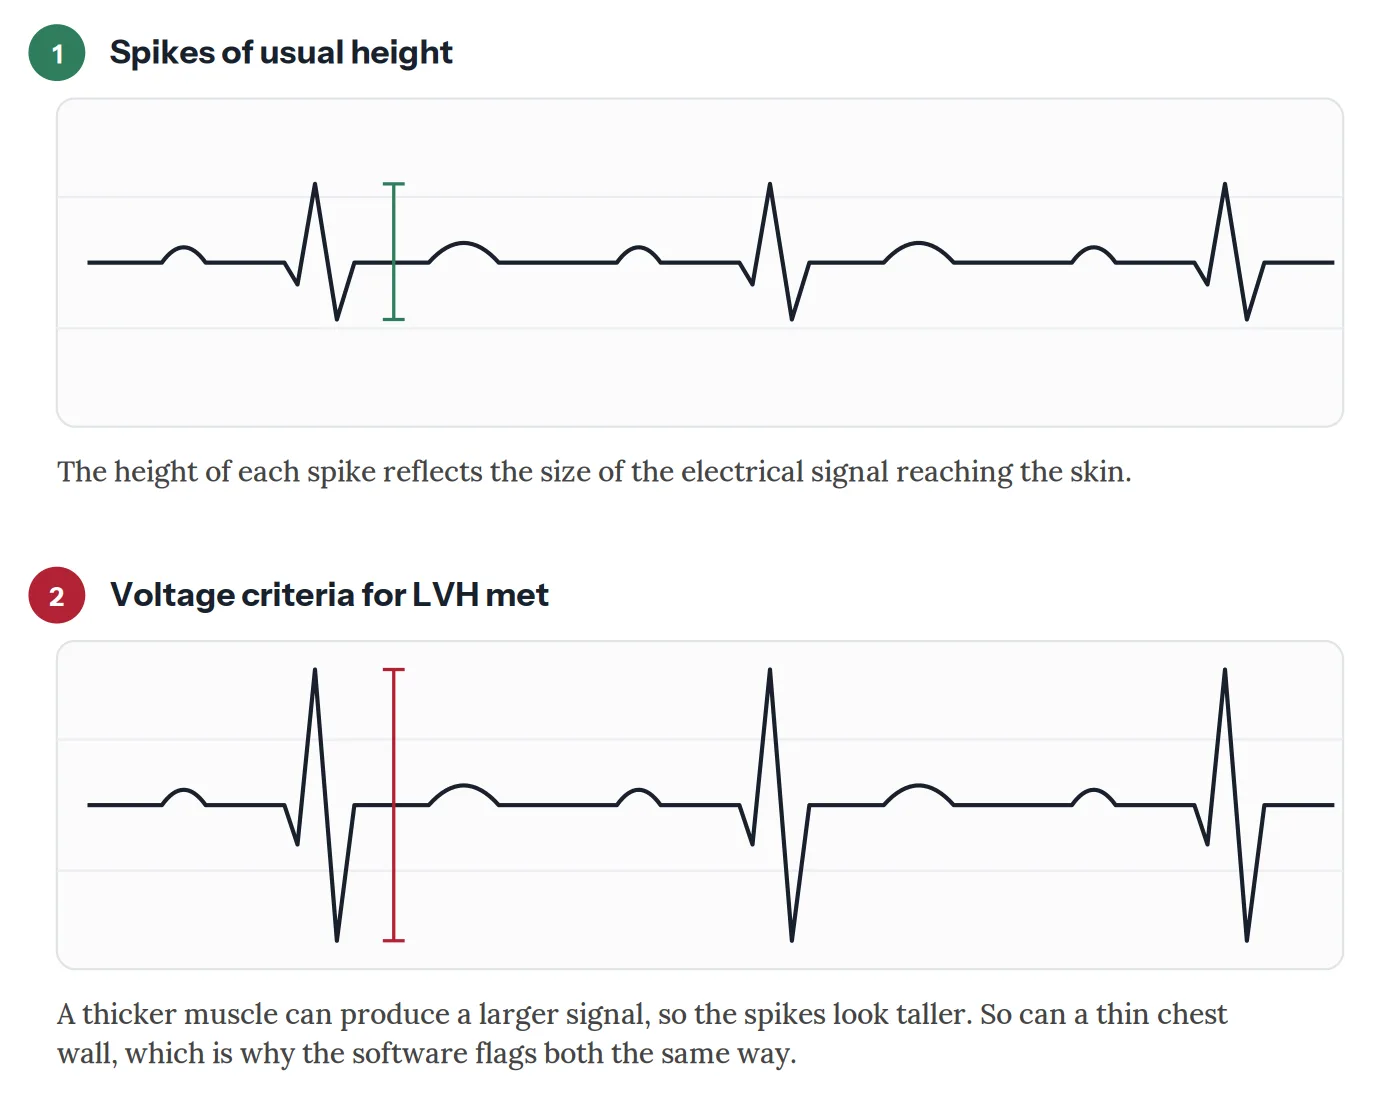
Wall thickness is simply not one of the things it measures directly. It measures electrical voltage at the skin. The reasoning behind the criteria is that a thicker muscle generates a larger electrical signal, so an unusually large signal might indicate a thicker wall.

That reasoning is sound, but voltage is an indirect measure. Depending on which criteria are used and which population is studied, the ECG identifies somewhere between roughly a fifth and a half of people who genuinely have a thickened left ventricle on imaging. It is a screening signal rather than a measurement.

The reason is that voltage at the skin depends on a great deal besides the heart. Chest wall thickness, body size, lung volume, the position of the heart in the chest, and even the exact placement of the electrodes all influence the reading.

A thicker muscle and a thinner chest wall both raise the voltage, which is why the ECG raises the question rather than answering it.

This is why the finding turns up so often in people whose hearts are entirely normal. Where there is less tissue between the heart and the electrodes, the signal arrives stronger and the voltages read higher. Regular endurance training adds to this, partly for the same reason and partly because it produces some genuine and entirely healthy adaptation of the muscle.

The reverse happens too. Someone carrying extra weight, or with lung disease, may have a genuinely thickened ventricle and a completely unremarkable ECG, because the signal is dampened before it reaches the skin. This is why a normal tracing does not settle the question either.

Two ECG tracings compared. In the first the spikes are of usual height. In the second they are markedly taller, which is what an automated report means by voltage criteria for left ventricular hypertrophy
A thicker muscle can produce a larger signal, so the spikes look taller. A thin chest wall can do the same, which is why the finding prompts a closer look rather than settling the question, Heart Matters

What the Report Might Say

The wording varies between machines, and the differences carry meaning.

“Voltage criteria for LVH” is the mildest version. It means only that the numbers exceeded a threshold. In someone with no symptoms and nothing else on the tracing, this on its own very often means nothing.

“LVH with repolarisation abnormality”, sometimes written as a strain pattern, is a more meaningful finding. Here the tracing shows not just large voltages but changes in how the heart muscle recovers between beats. That combination is more likely to reflect genuine thickening and is more strongly linked to cardiovascular risk over time.

“Left atrial enlargement” appearing alongside it adds weight too, because the upper chamber often enlarges in response to a stiff, thickened ventricle below it.

What Causes Genuine Thickening

High blood pressure is by far the most common cause and the reason the finding matters. Every beat against elevated pressure asks more of the muscle, and the wall thickens accordingly. This is often the first hint that blood pressure has been higher than realised for longer than realised.

Aortic stenosis, where the valve at the exit of the left ventricle narrows, creates the same problem more acutely. The chamber has to force blood through a restricted opening, and thickens in response. Aortic stenosis is usually audible as a murmur, so it rarely comes as a surprise on an ECG alone.

Athletic training produces genuine adaptation in endurance and strength athletes, and it is generally benign and reversible with detraining. Distinguishing it from the conditions below is one of the more nuanced judgements in cardiology.

Hypertrophic cardiomyopathy is an inherited condition in which the muscle thickens without any load driving it. It is much less common than the causes above, but it matters because it can affect young people and runs in families. HCM is one reason an unexplained finding in a young person is worth following up rather than dismissing.

Infiltrative conditions such as cardiac amyloidosis can thicken the wall with deposited protein rather than muscle. A distinctive combination sometimes appears here: a wall that looks thick on imaging alongside unexpectedly small voltages on the ECG.

What Happens Next

The finding is usually followed by an echocardiogram, an ultrasound that measures the wall thickness directly and calculates the muscle mass. It answers in twenty minutes what the ECG could only infer, and it also shows whether the chamber is pumping and filling normally.

Watch: what an echocardiogram involves, what it measures, and why it answers questions the ECG can only raise, Heart Matters Educational Series

Blood pressure assessment usually follows too, and often means readings taken at home or over 24 hours rather than a single clinic measurement, since a one-off reading is a poor guide to the pressure the heart has actually been working against.

Where thickening is confirmed and the cause is not obvious, further tests may follow depending on the pattern seen, which might include cardiac MRI, blood tests, or a family history and genetic assessment if an inherited condition is suspected.

Why It Is Worth Knowing About

Confirmed left ventricular hypertrophy is not something to panic about, but it is not nothing either. It is associated over the long term with a higher likelihood of atrial fibrillation, of heart failure, and of stroke, which is why cardiologists take it seriously as a marker even when the person feels entirely well.

The encouraging part is that it is not necessarily permanent. Where high blood pressure is the cause, sustained treatment can produce measurable regression of the thickening over months to years. The muscle that built up in response to pressure can partly unbuild when the pressure comes down. Studies have found that people whose ECG signs of hypertrophy regress with treatment go on to have fewer cardiovascular events than those whose do not.

That makes this one of the more actionable findings on an ECG report. It points at something that can be changed.

Conclusion

“Left ventricular hypertrophy” on an automated ECG report is a prompt to look further, not a verdict. In someone with no symptoms and an otherwise normal tracing it very often reflects nothing more than how the signal reaches the skin. In someone with high blood pressure it may be the first visible sign of what that pressure has been doing quietly for years.

Either way, the next step is the test that measures the muscle directly. An echocardiogram does that, and it is straightforward. What matters most is the conversation about what might be driving it, because for the most common cause, treatment does not just stop the thickening progressing. It can reverse some of it.

Related Reading

ApoB Explained: What It Measures and Why LDL Still Matters

apoB
Key Points

  • ApoB is a single protein that sits on the surface of every cholesterol particle capable of causing plaque, so an apoB result is effectively a headcount of all the particles that can harm your arteries.
  • A standard LDL cholesterol result measures the cholesterol carried inside your particles, not how many particles there are. Most of the time the two agree, but in some people they do not.
  • When LDL cholesterol looks reassuring but apoB is high, this mismatch (called discordance) can reveal hidden risk that a routine cholesterol panel misses.
  • Strong evidence supports apoB as an accurate marker of cardiovascular risk, particularly in people with high triglycerides, type 2 diabetes, or metabolic syndrome.
  • ApoB does not replace your LDL, triglycerides, or lipoprotein(a) results. Each tells you something the others cannot, and the best assessment uses them together.
  • No single number captures your risk. Heart disease is multifactorial, so blood pressure, diabetes, smoking, weight, and family history all matter alongside your lipids. Investigations such as a calcium score add another layer, and whether to add apoB is a conversation worth having with your cardiologist.

There is a lively and sometimes heated debate online about cholesterol. One vocal group argues that the LDL cholesterol number most of us have measured for decades is almost beside the point, and that a different number, apolipoprotein B, or apoB, is the one that truly predicts heart disease. If you have come across this argument and felt unsure who to believe, you are not alone.

The truth, as is so often the case in medicine, sits between the two extremes. ApoB is a genuinely valuable measurement, and the science behind it is sound. It is also not a magic number that makes everything else obsolete. This article explains what apoB actually is, why it can outperform a standard cholesterol result, and how to think about whether it belongs in your own blood tests.

What Is ApoB, Exactly?

To understand apoB, it helps to picture how cholesterol travels through your blood. Cholesterol is a fatty substance, and fat does not dissolve in water. So your body packages cholesterol inside tiny spherical particles that can move through the bloodstream. The particles that drive atherosclerosis, the gradual furring of the arteries, include LDL (low density lipoprotein) and a few close relatives.

Here is the key fact. Every one of these harmful particles carries exactly one molecule of a protein called apolipoprotein B on its surface. One particle, one apoB. This includes LDL, VLDL, IDL, and even lipoprotein(a). So when a laboratory measures your apoB level, it is effectively counting the total number of particles in your blood that are capable of lodging in your artery wall and forming plaque.

Why Counting Particles Can Beat Measuring Cholesterol

A standard lipid panel reports your LDL cholesterol, which sounds like it should tell you everything. But LDL cholesterol measures the amount of cholesterol carried inside your LDL particles. It does not measure how many particles you have.

This distinction matters because particles vary in size. Some people carry a smaller number of large, cholesterol-rich particles. Others carry a large number of small, cholesterol-poor particles. Two people can have an identical LDL cholesterol result while one has far more circulating particles than the other. Since it is the particles themselves that burrow into the artery wall, the person with more particles carries more risk, even though their cholesterol number looks the same.

A useful way to picture it: imagine traffic on a motorway. LDL cholesterol tells you the total weight of cargo being carried. ApoB tells you how many vehicles are on the road. If your arteries are the road, it is the number of vehicles, not the total cargo, that determines how often something collides with the wall.

One protein per particle

Every harmful cholesterol particle carries a single apoB protein, so your apoB level counts every particle that can cause plaque.

Cargo versus headcount

LDL cholesterol measures the cargo carried inside particles. ApoB counts the particles themselves, which is what damages the artery wall.

Why the gap matters

When particle count is high but cholesterol per particle is low, your LDL result can look fine while your true risk is not.

The family of particles apoB counts

ApoB does not just count LDL. It tags several related particles, each of which can contribute to plaque. This is part of why a single apoB result can be so informative: it captures the whole atherogenic family in one number.

LDL

Low density lipoprotein. The most familiar and most numerous of the harmful particles, and the main driver of plaque in most people.

VLDL and IDL

Larger, triglyceride-rich particles and their remnants. They become more important when triglycerides are high.

Lipoprotein(a)

An LDL-like particle with an extra protein attached. Largely inherited, and counted within apoB but not separately identified by it.

Each of these carries one apoB protein, so they are all captured in your total. What apoB cannot do is tell you the breakdown. It will not reveal, for instance, whether a high count is driven by ordinary LDL or by an inherited excess of Lp(a). That is one reason the individual tests retain their value, a point we return to below.

When LDL Cholesterol and ApoB Disagree

Most of the time, your LDL cholesterol and your apoB tell the same story. When both are high, or both are low, doctors call this concordance, and a standard cholesterol panel serves you perfectly well.

The interesting and clinically important situations are the mismatches, known as discordance. This is when your LDL cholesterol looks acceptable but your apoB is high, signalling many small particles quietly carrying on their work. In this scenario, a reassuring cholesterol result can give false comfort. A large 2024 review of 15 studies involving nearly 600,000 people found that apoB was a more accurate marker of risk than LDL cholesterol in every discordance study examined.

Who is most likely to be discordant

You are more likely to have a meaningful gap between your LDL cholesterol and your apoB if you have any of the following: high triglycerides, type 2 diabetes, metabolic syndrome, central weight gain around the abdomen, or a pattern of small dense LDL particles. People in these groups can have a deceptively normal LDL cholesterol while their particle count, and their risk, runs higher. This is precisely the group in which apoB adds the most.

What the Evidence Actually Shows

The case for apoB is strong, and it is worth being clear about what the research does and does not say.

On the supportive side, apoB has performed consistently well as a predictor of heart attack and stroke, often edging out both LDL cholesterol and non-HDL cholesterol, particularly in people whose results are discordant. Because it counts particles directly, it is less affected by the variations in particle size that can distort a standard cholesterol reading. For people with diabetes or high triglycerides, this advantage is most pronounced.

On the cautious side, this does not mean LDL cholesterol is worthless. Far from it. Lowering LDL cholesterol remains the single most trial-tested intervention in all of preventive cardiology. Decades of randomised trials, including the trials that established statins and newer agents such as PCSK9 inhibitors, were built on LDL cholesterol as the target, and the benefit of lowering it is beyond dispute. The online voices declaring LDL cholesterol irrelevant overstate the case considerably.

Why LDL, Triglycerides, and Lp(a) Still Matter

The enthusiasm for apoB has, in some corners of the internet, tipped into dismissing the numbers we have relied on for years. That is a mistake. Each of the established measurements tells you something apoB alone does not, and a good lipid assessment uses them together.

LDL cholesterol

LDL cholesterol is not a flawed or outdated number. It is the most thoroughly validated treatment target in cardiology, and every major guideline still places it at the centre of care. The reason is simple: when we lower LDL cholesterol in clinical trials, heart attacks and strokes fall in proportion, reliably and repeatedly. ApoB refines how we interpret LDL cholesterol in certain people. It does not unseat it. If you are tracking one number over time to see whether your treatment is working, LDL cholesterol remains an entirely sensible choice.

Triglycerides

Triglycerides are a separate and valuable piece of the puzzle. A raised triglyceride level is one of the clearest signals that your LDL cholesterol and apoB may be discordant, because high triglycerides tend to accompany the small, dense, numerous particles that apoB picks up. Triglycerides also respond strongly to lifestyle, which makes them a useful and motivating number to watch. Diet matters here, and the evidence supporting the Mediterranean diet and omega-3 fats is particularly relevant for people with elevated triglycerides.

Lipoprotein(a)

Lipoprotein(a), or Lp(a), deserves its own place on the test request entirely. It is largely inherited, it changes very little over a lifetime, and a single measurement tells you whether you carry this extra, independent layer of risk. While apoB does count Lp(a) particles among its total, it cannot tell you how much of your risk comes specifically from Lp(a), which is why a dedicated Lp(a) test remains worthwhile in its own right. For many people this is a once-in-a-lifetime measurement that meaningfully changes how aggressively their other risk factors should be managed.

What Does a Statin Do to Your ApoB?

This is a question worth answering directly, because it is one of the most useful things to understand about apoB in practice. Statins lower apoB substantially, typically by somewhere in the range of a quarter to nearly half, broadly in step with how much they lower LDL cholesterol. Adding ezetimibe or a PCSK9 inhibitor brings it down further still. So if you are already on treatment, your apoB is very likely already falling alongside your other numbers.

There is one important exception, and it is the reason apoB does not make the individual tests redundant. Statins do very little to lipoprotein(a). Someone can take a statin, watch their LDL cholesterol and apoB fall nicely, and still carry a high inherited Lp(a) that the treatment has barely touched. This is exactly why measuring Lp(a) at least once, separately, remains worthwhile even for people whose apoB looks well controlled.

ApoB Is One Piece of a Multifactorial Picture

Perhaps the most important point in this whole discussion is the one the online debate tends to forget. Cardiovascular disease is multifactorial. No single number, however good, captures your risk on its own, and apoB is no exception.

Your overall risk is shaped by a web of factors that interact with one another. These include your blood pressure, whether you have type 2 diabetes or features of metabolic syndrome, whether you smoke, your weight and waist measurement, your family history, your level of inflammation, and your age. A person with a perfect apoB but uncontrolled blood pressure and a smoking habit is not low risk. Conversely, a moderately raised apoB carries very different weight in an otherwise healthy 45-year-old than in someone with diabetes and a strong family history.

This is why fixating on any one marker, apoB included, can be misleading. The most useful approach is the one your cardiologist actually uses: weighing your lipids alongside every other modifiable factor. Two of the most powerful of those, smoking and high blood pressure, are entirely separate from your cholesterol particles and yet enormously important. You can read a fuller account in our overview of cardiovascular risk factors.

The Role of Investigations

Blood markers tell you about risk. Imaging can tell you what is actually happening in your arteries, and the two together are far more informative than either alone.

The coronary calcium score is the investigation patients most often ask about, and it can be confusing, so it is worth being clear. A calcium score does not measure your cholesterol or your particle count. It measures calcified plaque that has already formed in your coronary arteries, giving a direct picture of the disease itself rather than the risk factors driving it. A high score can prompt more intensive treatment even when your blood results look reasonable. Our article on what a high calcium score really means explains how to interpret the number.

One genuine source of confusion deserves a mention. Because statins can convert soft plaque into denser, calcified plaque, people on a statin can sometimes see their calcium score rise even as their risk falls. This apparent paradox is explained in our piece on statins and your calcium score. For people who need a more detailed look at the arteries themselves, a CT coronary angiogram can show both calcified and soft plaque. Inflammation markers such as hs-CRP can add yet another dimension. Which of these, if any, is right for you depends entirely on your circumstances and is a decision for you and your cardiologist.

Where the Guidelines Stand

The official guidance reflects this balanced reality. Different expert bodies place apoB at slightly different points on the spectrum, but none has discarded LDL cholesterol.

Guideline body Position on apoB
European (ESC/EAS) Accepts apoB as an alternative to LDL cholesterol for risk assessment. The 2025 update still confirms LDL cholesterol as the primary target.
Canadian (CCS) The most apoB-forward. Allows apoB to be used as the primary therapeutic target, especially when triglycerides are raised.
United States (ACC/AHA) Lists a high apoB as a risk-enhancing factor that supports more intensive treatment, but does not yet set a routine apoB target.
National Lipid Association Proposes graded apoB targets that become stricter as cardiovascular risk rises.

The main reason apoB has not yet replaced LDL cholesterol everywhere is not weak evidence. It is the absence of a single agreed target across all guidelines, combined with a degree of caution about changing long-established practice. Availability and cost also vary from one health system to another.

Should You Add ApoB to Your Next Blood Test?

In Australia, apoB can be measured by most pathology laboratories, usually reported in grams per litre. It is not always part of a standard lipid panel and may not be routinely rebated, so it is worth asking whether it applies to your situation and whether there is an out of pocket cost.

There is a strong argument for measuring apoB at least once if you fall into a higher-risk group, particularly if you have raised triglycerides, type 2 diabetes, metabolic syndrome, or a family history of early heart disease. It is also useful when your LDL cholesterol seems well controlled but you or your cardiologist remain concerned about residual risk. For someone already tracking LDL, HDL, and lipoprotein(a), as many thoughtful patients now do, apoB is a natural and informative addition rather than a replacement for any of them.

What apoB cannot do is stand alone. It works best alongside your other blood results, any imaging you have had, and the broader picture of your risk factors. The number is only as useful as the conversation it prompts with the person managing your care.

Heart Matters Resource

When in Doubt, Get Checked Out

If you are unsure whether your cholesterol results tell the full story, a focused review of your numbers with your GP or cardiologist is one of the most worthwhile conversations you can have.

Read: When in Doubt, Get Checked Out →

Conclusion

ApoB is one of the most useful advances in everyday cardiovascular risk assessment, because it counts the particles that actually cause plaque rather than estimating the cholesterol they carry. For people whose standard cholesterol result may be quietly misleading, it can uncover risk that would otherwise go unnoticed.

The balanced takeaway is this. LDL cholesterol, triglycerides, and lipoprotein(a) each remain valuable, and apoB sharpens the picture rather than replacing any of them. None of these numbers stands alone, because heart disease is multifactorial: your blood pressure, diabetes, smoking status, weight, and family history all matter alongside your lipids. The most useful conversation you can have is not about a single number, but about the whole picture, with the cardiologist who knows your circumstances.

Related Reading